Related Experiment Video
Updated: Sep 17, 2025


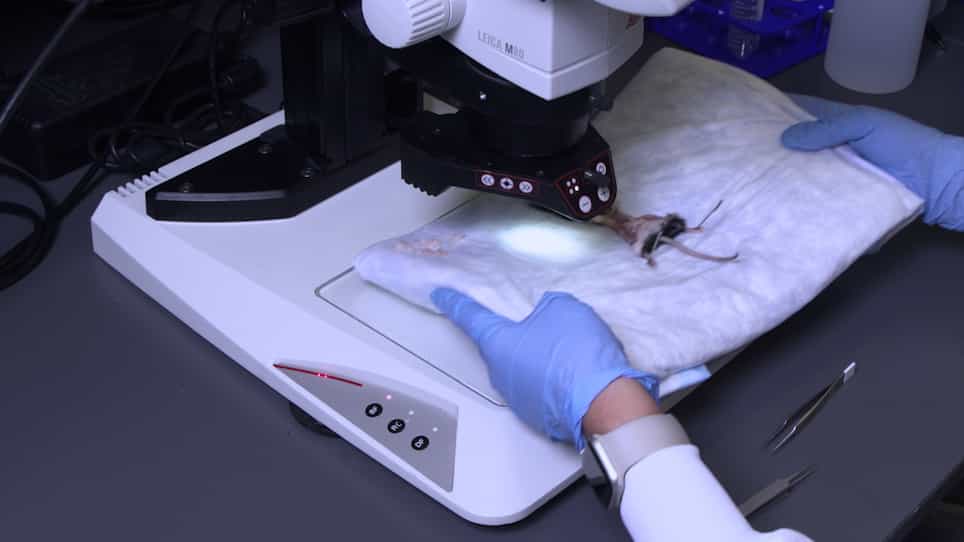
Nerve-sparing Mid-urethral Obstruction NeMO in Female Small Rodents
Published on: April 25, 2017
Etiopathogenesis of "Bladder Outlet Obstruction" in the Female - Inability of Pelvic Muscles to Sufficiently Open
Peter Emanuel Petros1, Bernhard Liedl2, Maren Juliane Wenk3
1Retired Pelvic Surgeon, Elizabeth Bay, New South Wales, Australia, pp@kvinno.com.

Background:
Historically, opening the bladder neck and urethra for evacuation has been solely by detrusor contraction with "urethral relaxation."
Summary:
We present a change in thinking based on experimental research and clinical practice, human and animal: the urethra is opened externally immediately prior to detrusor contraction by posterior pelvic floor muscles contracting against competent uterosacral ligaments (USLs). A binary feedback control system (EITHER open OR closed) with neurological and peripheral musculo-ligamentous components is presented. Three oppositely acting muscle vectors contract against suspensory ligaments to close urethra distally and at bladder neck; relaxation of the forward closure vector allows the two posterior muscles to contract against USLs to open the posterior urethral wall prior to micturition. Whatever the anatomical cause of bladder emptying difficulties, neurological, muscle damage, ligament damage, urethral obstruction, inability of the pelvic muscles to externally open the urethra means the detrusor must contract against an unopened urethra which presents a high resistance to flow. This resistance is perceived by the patients as "bladder outlet obstruction." Collagen damage during birthing, or breakdown after the menopause, makes ligament damage the most vulnerable part of the female micturition system. Treatment depends on reinforcing USLs as the contractile point for the posterior opening muscles: in premenopausal women by squatting-based exercises; in older women by mechanical support of USLs by pessary, or surgical USL repair.
Key Message:
A change in thinking: posterior pelvic muscles contract against a firm USL to open posterior urethral wall prior to micturition (video
Related Concept Videos
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:20
Disorders of the Urinary System
Urinary tract infections (UTIs) are one of the most common urinary system disorders. They are caused by bacteria that enter the urethra and can spread to the bladder resulting in cystitis. Pyelonephritis is the result of a UTI that has ascended to the level of the...
 01:23
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:26
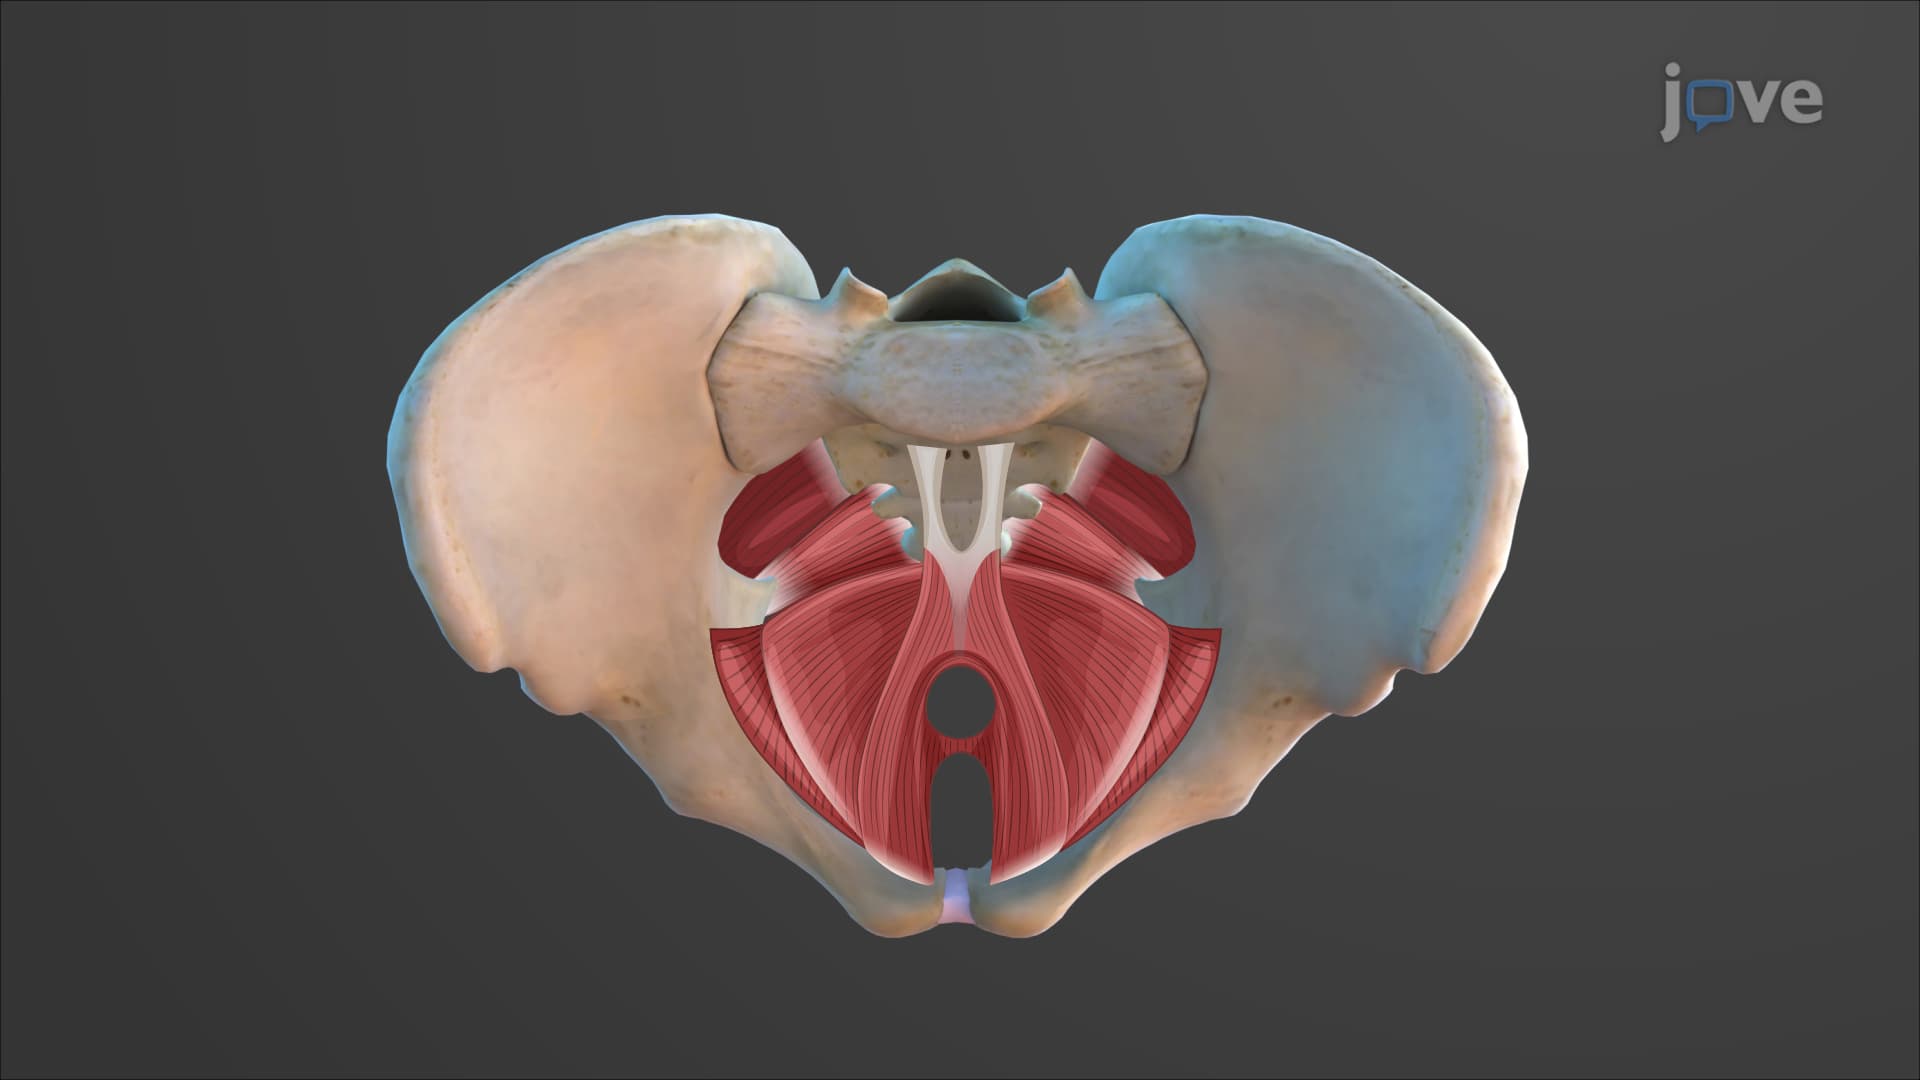
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:26
The Micturition Reflex
The process begins with bladder filling, where the bladder wall stretches as urine accumulates. This stretching activates the urine storage reflex, mediated by the sacral spinal segments and the pontine storage center. Efferent sympathetic impulses stimulate the detrusor muscle to relax and the internal urethral sphincter to contract, facilitating...
 01:16
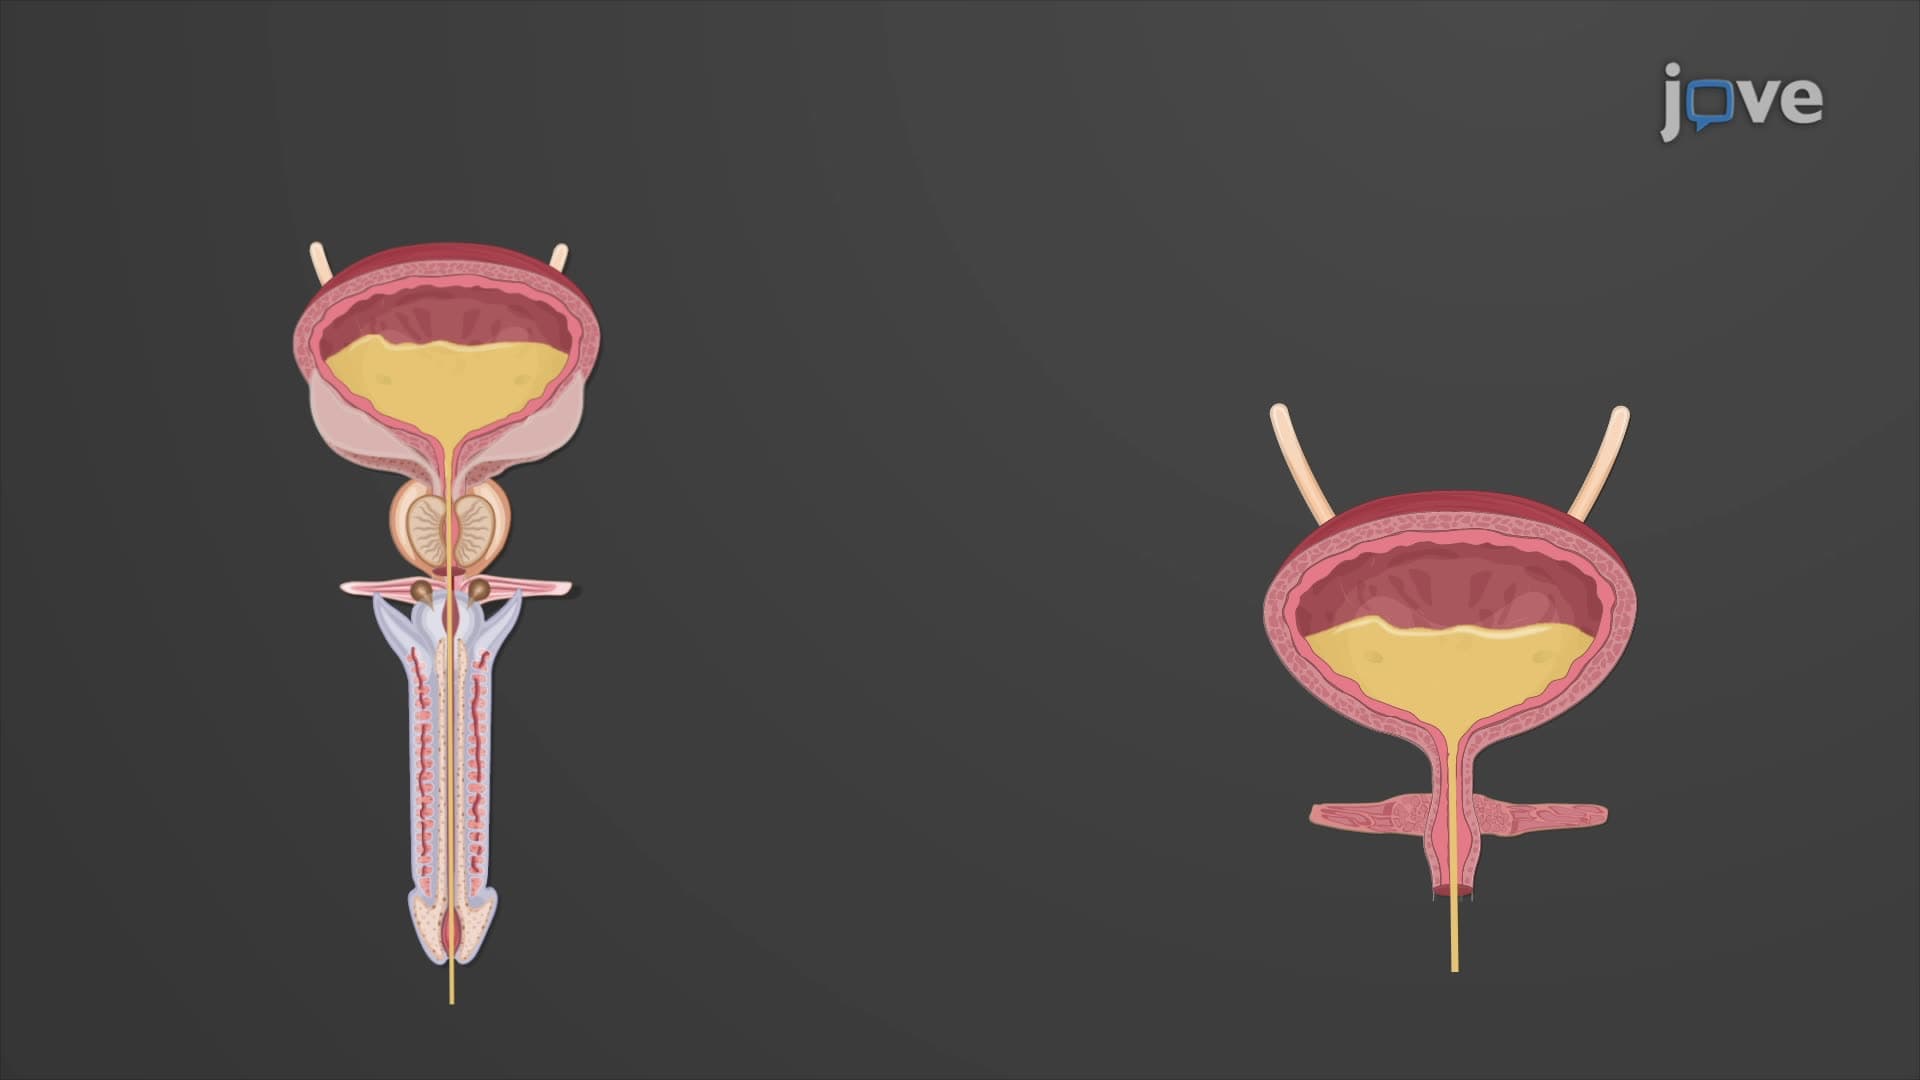
Urethra
The anatomy of the urethra differs between males and females. In females, the urethra is short, measuring about 3–4 cm in length, and opens anterior to the vaginal opening. In males, the urethra is longer and passes through the penis, serving dual purposes: expelling urine and ejaculating semen. The male...