Related Experiment Video
Updated: Sep 17, 2025
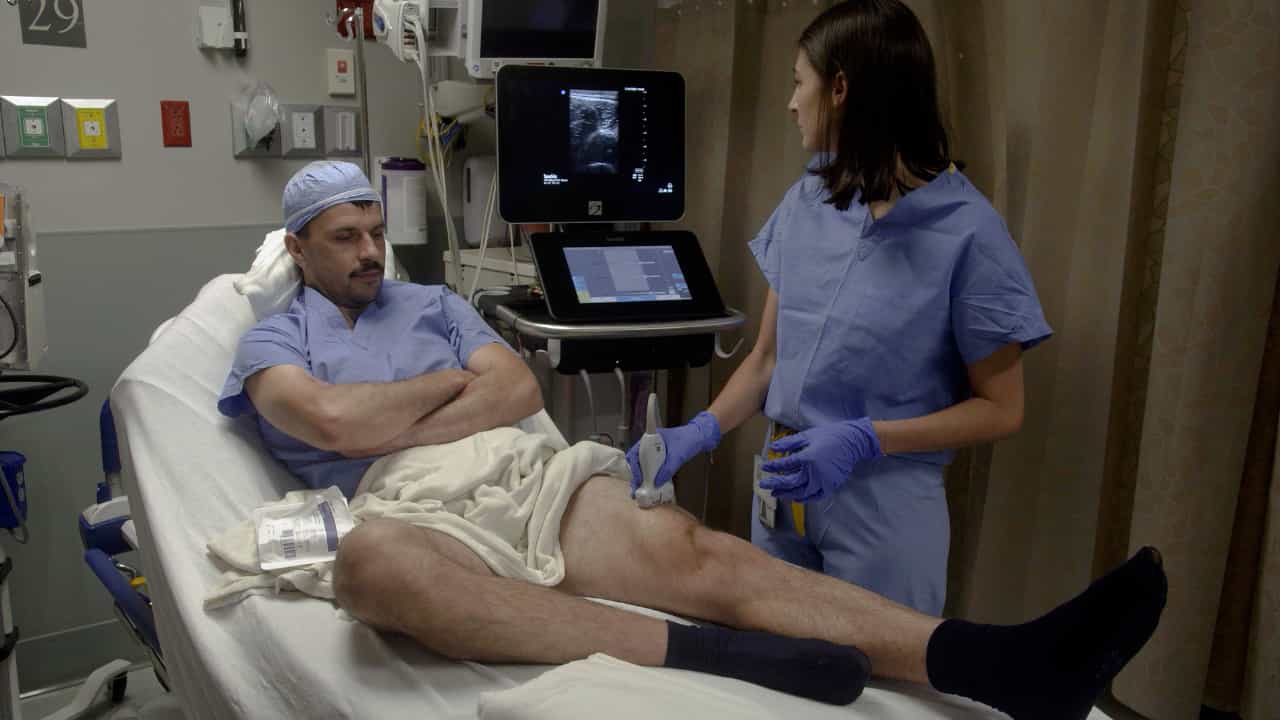
Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
Utility of Frailty Index in Predicting Discharge Disposition and Prolonged Length of Stay Following Enhanced Recovery
Tariq Z Issa1, Christopher A Reynolds2, Jennings H Dooley3
1Department of Orthopaedic Surgery, Icahn School of Medicine at Mount Sinai, New York, NY, USA.

Background:
Predictive tools such as the risk assessment and prediction tool (RAPT) and the 5-item modified Frailty Index (mFI-5) have been created to assist in discharge planning after total joint arthroplasty (TJA) including hip and knee arthroplasty, but there is no uniform determination of frailty risks. The primary objective was to compare the modified Frailty Index and RAPT in assessing outcomes following TJA, and we hypothesized similar performance between both measures.
Methods:
We conducted a retrospective study of patients aged 50 years and more undergoing primary elective TJA at a single academic tertiary center through the same Enhanced Recovery After Surgery protocol. Patients were stratified using mFI-5 and RAPT scores tabulated during preoperative clinic visits. Multivariable analyses were conducted to assess independent associations of mFI-5 and RAPT with complications, prolonged length of stay, readmissions, and nonhome discharge. Youden's index was used to construct receiver operating characteristic curves to assess the predictive ability of mFI-5, Charlson Comorbidity Index, and RAPT in classifying outcomes.
Results:
A total 858 TJA patients were included. Overall, 547 (63.8%) were not frail, 273 (31.8%) were prefrail, and 38 (4.4%) were frail. When stratifying by RAPT, 369 (43.0%) had RAPT > 9 (low-risk), 402 (46.9%) had RAPT 6-9 (moderate-risk), and 87 (10.1%) had RAPT < 6 (high-risk). Prefrailty (odds ratio [OR]: 2.31, P = .006) and frailty (OR: 8.82, P < .001) were associated with higher nonhome discharge. Both RAPT 6-9 (OR: 4.87, P = .001) and RAPT < 6 (OR: 27.2, P < .001) were associated with nonhome discharge. Neither was independently associated with complications or readmissions. These indices were poor independent predictors of complications, readmissions, and prolonged length of stay (all, area under the curve [AUC] < 0.7). While RAPT demonstrated the greatest discriminative ability in identifying nonhome discharge (AUC: 0.772), mFI-5 (AUC: 0.720) was also an acceptable predictors of nonhome discharge.
Conclusions:
The mFI-5 performs similarly to RAPT in predicting 30-day TJA outcomes. Using the mFI-5 may aid preoperative risk stratification to optimally identify candidates for home discharge.
More Related Videos
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
 06:52
Assessment of Dependence in Activities of Daily Living Among Older Patients in an Acute Care Unit
Published on: September 30, 2020