Related Experiment Video
Updated: Sep 17, 2025

Author Spotlight: Unraveling the Impact of Mechanical Ventilation on Diaphragm Function and Patient Outcomes
Published on: November 3, 2023
Utility of diaphragm dome height as a marker of operational lung volume changes, disease burden and exacerbations in
Sarah A Beydoun1, Olivia C Iorio1,2, Daniel Genkin3
1Respiratory Epidemiology and Clinical Research Unit, Centre for Outcomes Research and Evaluation, Research Institute of the McGill University Health Centre, Montreal, QC, Canada.

Background:
Dynamic hyperinflation is central to dyspnoea, exercise limitation and exacerbations in COPD. While studied previously in moderate-to-severe COPD, the relevance of diaphragm dome height (DDH) on clinically important outcomes has been under-investigated in mild-to-moderate COPD.
Methods:
Canadian Cohort Obstructive Lung Disease (CanCOLD) participants with spirometry-confirmed COPD, symptom-limited incremental cardiopulmonary exercise testing and computed tomography image data were included. Base-to-apex left DDH (LDDH) and right DDH (RDDH) were automatically segmented, with increased height implying less flattening and thus less hyperinflation. Dynamic hyperinflation was defined as ≥150 mL reduction in inspiratory capacity (IC) from rest to peak exercise. Cross-sectional linear regression models were fitted between LDDH and RDDH (predictor variables) with peak IC (ICpeak), peak workload (W peak), forced expiratory volume in 1 s (FEV1) and COPD Assessment Test (CAT) score (outcome variables), and in longitudinal (Anderson-Gill) models with "symptom-based" and "event-based" exacerbations. Results are reported as parameter estimates or hazard ratios (HRs) with 95% confidence intervals per interquartile range dome height increment.
Results:
Amongst 304 participants (mean±sd age 64.7±10.3 years, 41.8% female, 44.4% with mild COPD), each LDDH and RDDH increment, respectively, was associated with ICpeak (0.21 (95% CI 0.13-0.29) L and 0.13 (95% CI 0.07-0.19) L), W peak (9.54 (95% CI 5.03-14.04) W and 6.04 (95% CI 2.45-9.62) W), FEV1 (0.17 (95% CI 0.10-0.25) L and 0.08 (95% CI 0.02-0.14) L) and CAT score (-1.36 (95% CI -2.39- -0.33) and -0.82 (95% CI -1.63-0.00)). LDDH alone was associated with both symptom-based (HR 0.82 (95% CI 0.74-0.91)) and event-based (HR 0.83 (95% CI 0.73-0.95)) exacerbations. Of 167 out of 304 participants with confirmed dynamic hyperinflation (ΔIC -0.47±0.25 L), LDDH alone was associated with all outcomes (ICpeak, W peak, FEV1, CAT and symptom-based/event-based exacerbations).
Conclusions:
LDDH appears to be a clinically important marker for operational lung volume changes, lung function, exercise performance, disease burden and exacerbations in mild-to-moderate COPD.


Related Concept Videos
 01:15
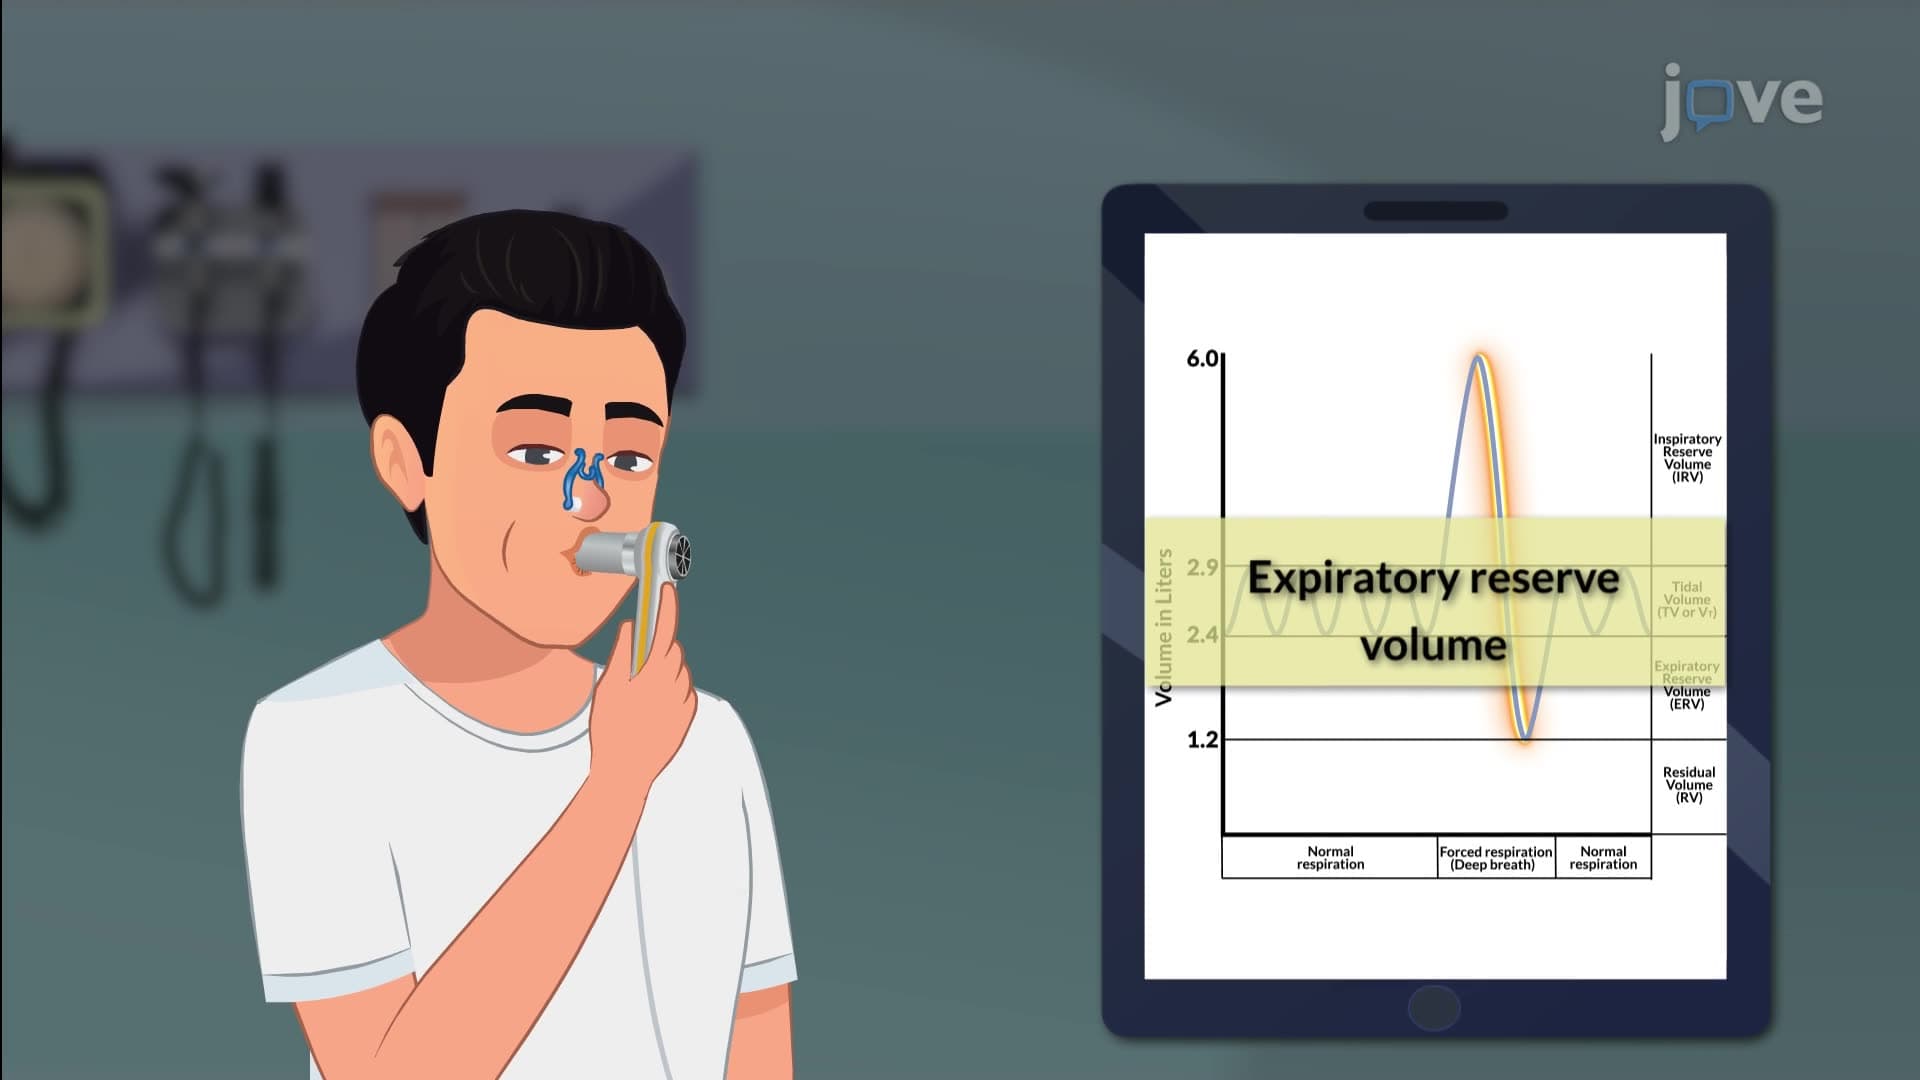
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:47
Lung Capacity
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...