Related Experiment Video
Updated: Sep 17, 2025

New Thrombectomy Technique for Total Portal Vein Thrombosis in Liver Transplantation
Published on: June 27, 2025
Comparing outcomes of deceased-donor and living-donor liver transplants in patients with PVT
Zhihao Li1, Owen Jones, Luckshi Rajendran
1HBP & Multi-Organ Transplant Program, University Health Network, Toronto, Canada.

Abstract:
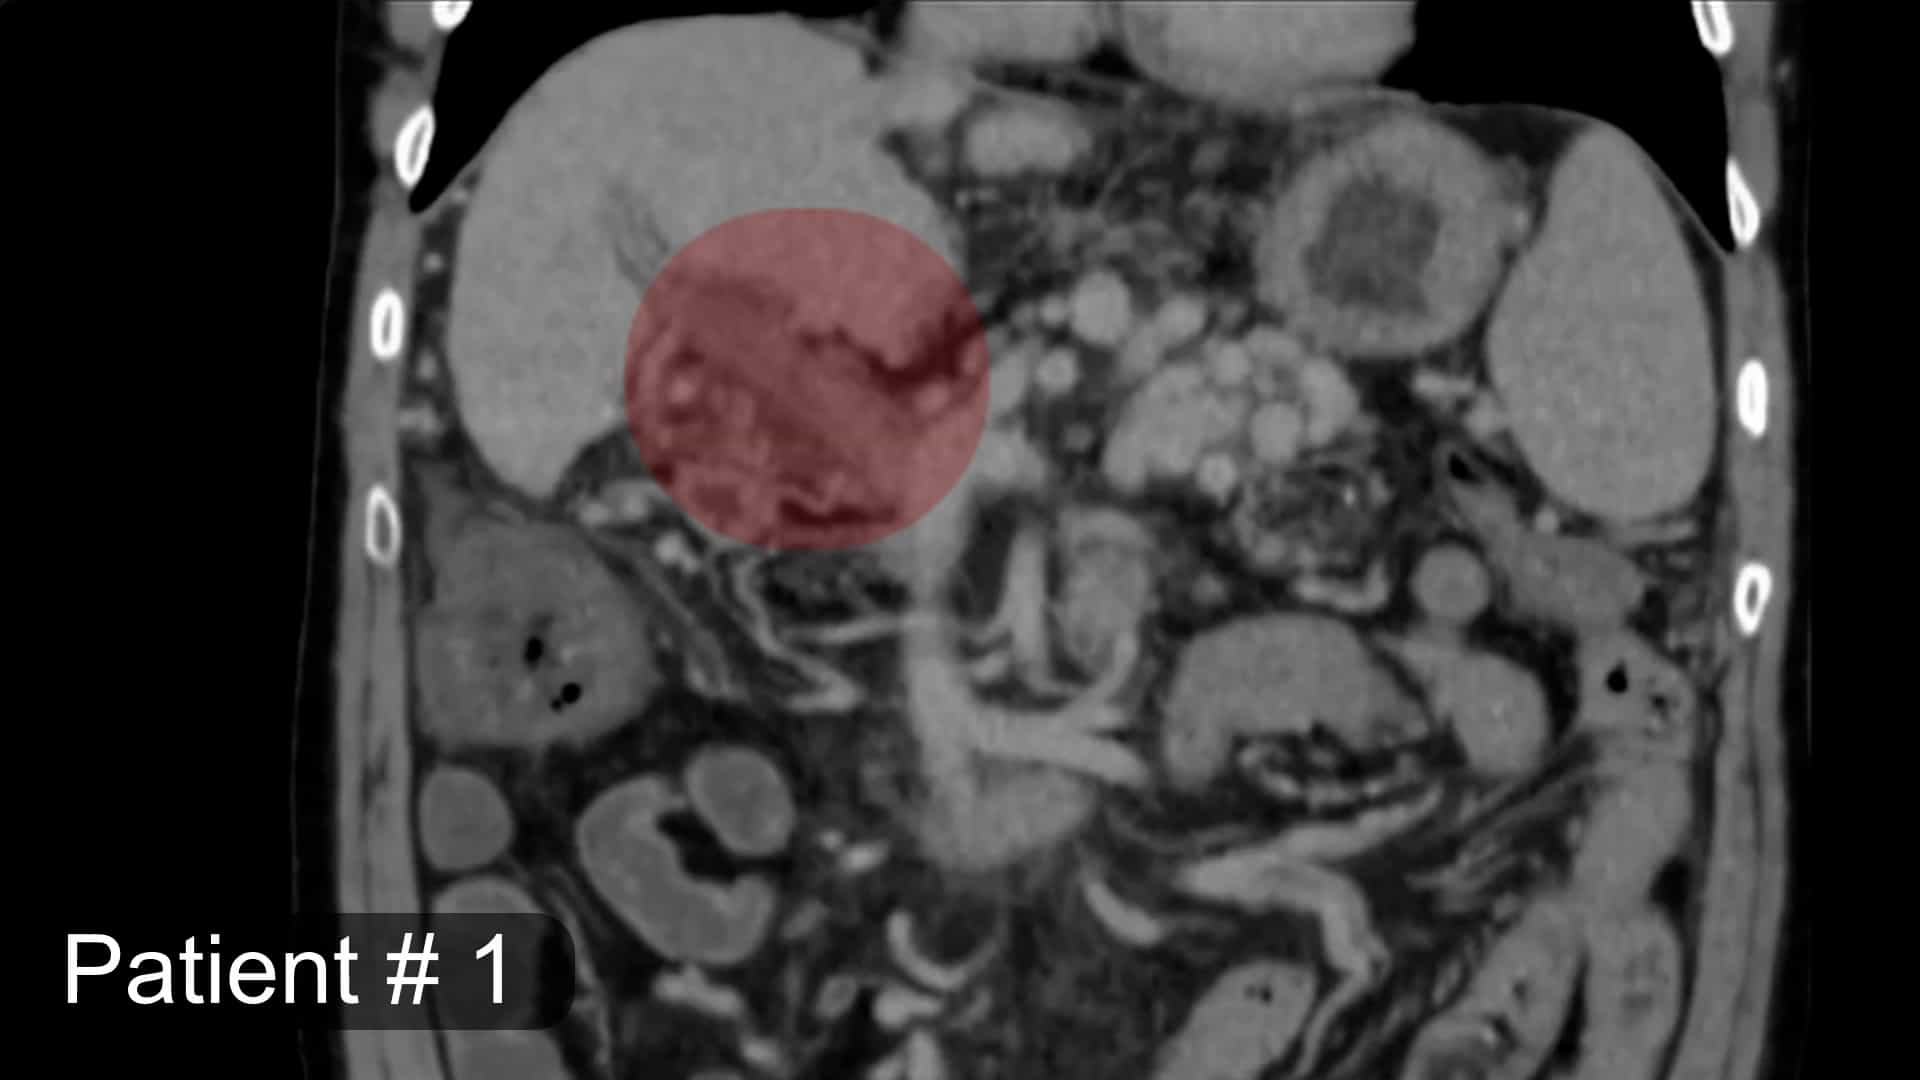
Portal vein thrombosis (PVT) complicates liver transplantation (LT) by hindering portal flow restoration. Some centers still consider PVT a contraindication for living-donor LT (LDLT) due to technical challenges compared to deceased-donor LT (DDLT). We retrospectively analyzed adults undergoing LT with main PVT between 2006 and 2023, excluding tumor thrombi and re-LT. Using 1:1 propensity score matching, we balanced age, MELD score, Yerdel classification, cavernous transformation, and physiological reconstruction methods. The primary endpoint was the 90-day complication rate; secondary endpoints included patient and graft survival. Of 122 patients, 96 were matched (48 LDLT, 48 DDLT). The median age was 57 years (IQR: 50-63), with a median MELD of 18 (IQR: 12-25). Common underlying liver diseases were hepatitis C (26%) and alcoholic liver disease (20%). In all, 85% had PVT Yerdel grade I/II, 11% grade III, and 3% grade IV, with cavernous transformation present in 17%. Physiological end-to-end portal vein reconstruction was performed in 90% of cases, while 10% received reconstruction with jump grafts. No significant differences were observed between LDLT and DDLT in warm ischemia time (57 vs. 58 min, p =0.3), 90-day major (37.5% vs. 39.6%, p =0.99) or minor complications (47.9% vs. 52.1%, p =0.84), portal vein re-thrombosis (12.5% vs. 10.6%, p =0.99), posttransplant dialysis (4% vs. 8%, p =0.65), or ascites (25% vs. 30%, p =0.77). At 1/3/5 years, patient and graft survival rates were similar between LDLT and DDLT recipients (log-rank p =0.8 and p =0.9, respectively). Cox regression showed posttransplant anticoagulation (with low-molecular-weight heparin, factor Xa inhibitors, and vitamin K antagonist) as protective for graft survival (HR 0.3, p =0.005). LDLT can achieve outcomes comparable to DDLT in patients with PVT. PVT should not be considered a contraindication for LDLT in selected patients at experienced centers.