Related Experiment Video
Updated: Sep 17, 2025
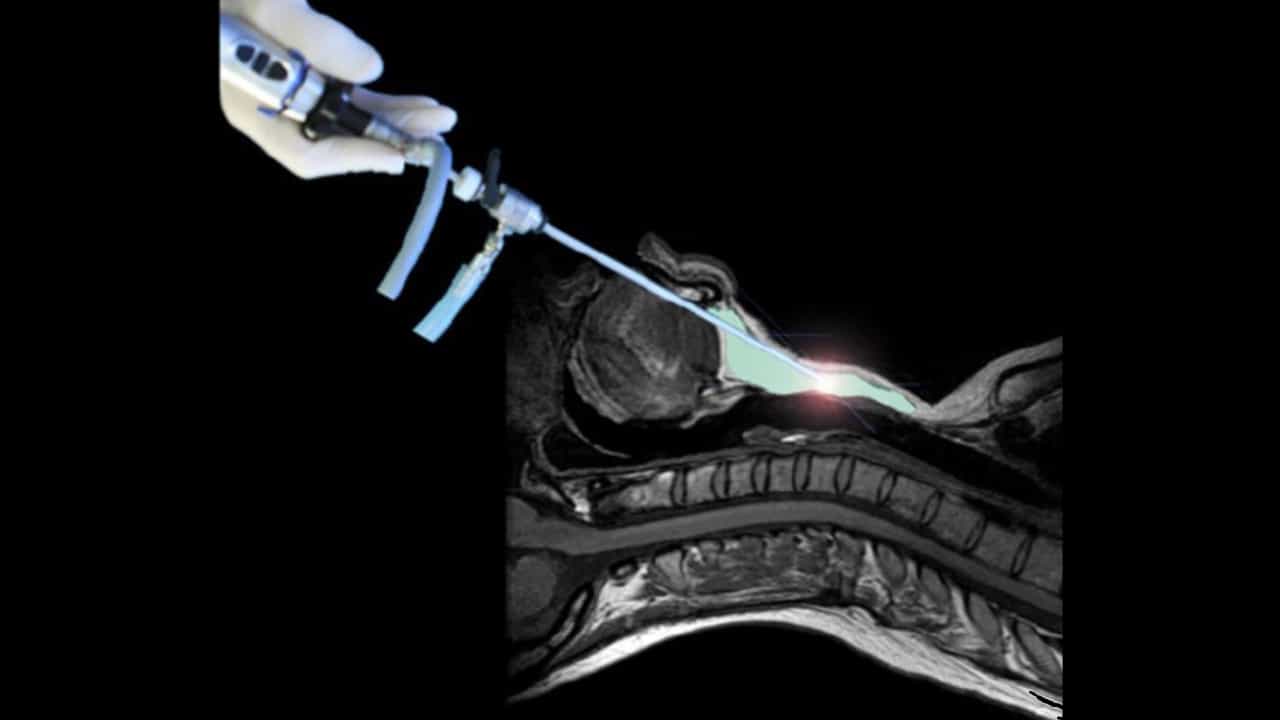

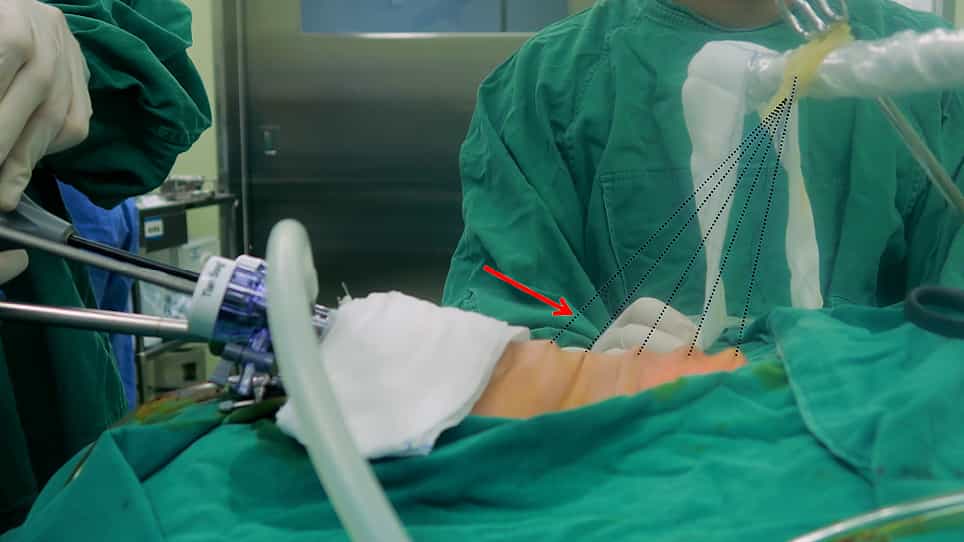
Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023
Lateralised T3/T4N0 oral squamous cell carcinoma. Is contralateral elective neck dissection or neck radiotherapy
Luke F Western1, Giovanni Diana2, Prav Praveen3
1East Kent Hospitals University NHS Foundation Trust, Ashford, United Kingdom; King's College London, London, United Kingdom.

Abstract:
Oral squamous cell carcinoma (OSCC) is a prevalent malignancy with a propensity for lymphatic spread, particularly to the neck. There are current inconsistencies in the treatment paradigm for cT3/4 OSCC with negative nodal status. The American Society of Clinical Oncology (ASCO) recent guidelines advocate for contralateral neck treatment with neck dissection or radiotherapy, but this approach remains debated and has not been adopted within UK clinical guidance. This study aims to evaluate the recurrence rates and survival outcomes of patients with well lateralised pT3/4N0 OSCC managed with or without contralateral neck interventions. A retrospective cohort study was conducted across five UK Oral and Maxillofacial Surgery (OMFS) units. We included patients with biopsy-proven pT3/T4 OSCC treated between 2012 and 2017. The study compared outcomes between two groups: the standard care group (SC) and the extended neck management group (ENM), which additionally received contralateral neck dissection (CLND) or neck radiotherapy (NRT). The primary outcome measure was the recurrence rate (RR), with secondary outcome measures including overall survival (OS), disease-free survival (DFS) and recurrence-free survival (RFS). Of 583 patients, 210 met the inclusion criteria. The mean follow up was 44 months. The SC group, compared with ENM demonstrated similar overall recurrence rate (24.8% vs 24.6%), higher regional recurrence (7.4% vs. 1.6%) and lower distant recurrence rates (4% vs 6.6%) respectively, however, none of these results reached significance. No significant differences in OS, DFS, or RFS were demonstrated (p > 0.05) between groups, and this was maintained with confounding variables controlled for. Findings suggest that well lateralised T3/4N0 OSCC patients managed more conservatively, without contralateral neck intervention, may have comparable outcomes to those receiving additional neck management. Further research into this area of research paucity may assist in further refinement of management guidelines for this subset of OSCC patients.