Related Experiment Video
Updated: Sep 16, 2025
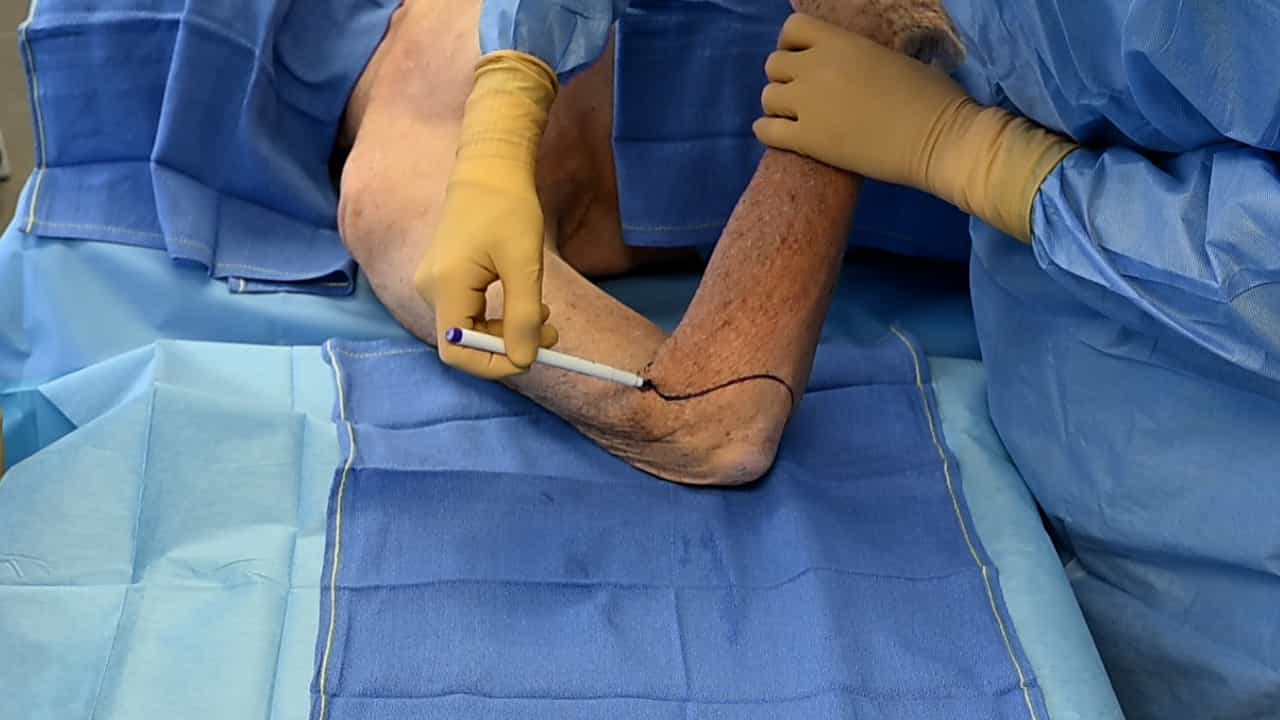

Vascularized Composite Hand Allograft Procurement and Preparation for Distal and Proximal Forearm Allotransplantation: A Stepwise Approach
Published on: May 23, 2025
Forearm Synostosis Using A Vascularized Pedicled Ulnar Periosteal Graft for Supination Deformity in Brachial Plexus
Francisco Soldado1, Paula Díaz-Gallardo2, Juliana Rojas-Neira3
1Pediatric Hand Surgery and Microsurgery Unit, "Instituto de Investigación Sanitaria HM Hospitales", Barcelona, Spain.

Background:
Forearm supination posture is a common secondary deformity in brachial plexus birth injury (BPBI), leading to functional impairment of the upper limb, as pronation is required for most activities of daily living. The purpose of this report is to analyze a series of children with forearm supination deformity secondary to severe BPBI and complete pronation palsy, who were treated with forearm fusion in slight pronation through the creation of a radioulnar synostosis using a novel distal pedicled vascularized ulnar periosteal flap (VUPF).
Methods:
Retrospective analysis. Inclusion criteria included complete pronation paralysis with active wrist extension present and a minimum of 6 months follow-up. Demographic information, preoperative passive pronation, postoperative forearm rotational position, radiographic union, and parental satisfaction using a 4-point Likert-type ordinal scale (1-very unsatisfied, 2-unsatisfied, 3-satisfied, and 4-extremely satisfied) were analyzed. A retrograde distally pedicled vascularized ulnar periosteal flap covering approximately one third of the ulnar length and based on the posterior interosseous vessels-was transferred to the dorsal aspect of the radius and fixed for 4 weeks using Kirschner wires.
Results:
Twenty children with a mean age of 53.6 months (range 20 to 115 months) and a mean passive forearm pronation of 9° (range 60° to 60°) with a mean follow-up of 13.7 months (range 8 to 18 months) were included in this report. All except one had complete residual BPBI. A partially ossified radioulnar synostosis was radiographically observed at 4 weeks in all cases. Mean immediate postoperative and final follow-up rotational values were similar, measuring 15° of pronation (range 0° to 30°). All parents reported extreme satisfaction with both functional and cosmetic outcomes.
Conclusions:
Forearm fusion in slight pronation by creating a radioulnar synostosis using a distal pedicled vascularized ulnar periosteal flap is an effective and fast technique to correct supination deformity and might be considered among other reported strategies.
More Related Videos
 09:14
Surface Electromyographic Biofeedback as a Rehabilitation Tool for Patients with Global Brachial Plexus Injury Receiving Bionic Reconstruction
Published on: September 28, 2019
 08:11
Vascularized Composite Upper Limb Allograft Harvesting for Proximal Arm Allotransplantation
Published on: June 13, 2025
Related Concept Videos
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:15
Bones of the Upper Limb: Ulna
 01:09
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a...
 01:12
Arteries of the Upper Limbs
 01:16
Muscles that Move the Forearm
Forearm Flexors
The biceps brachii, brachialis, and brachioradialis are forearm flexors. The biceps brachii is made up of two heads. Its long head originates at the supraglenoid tubercle of the scapula, whereas that of the short head is...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...