Related Experiment Video
Updated: Jul 18, 2026
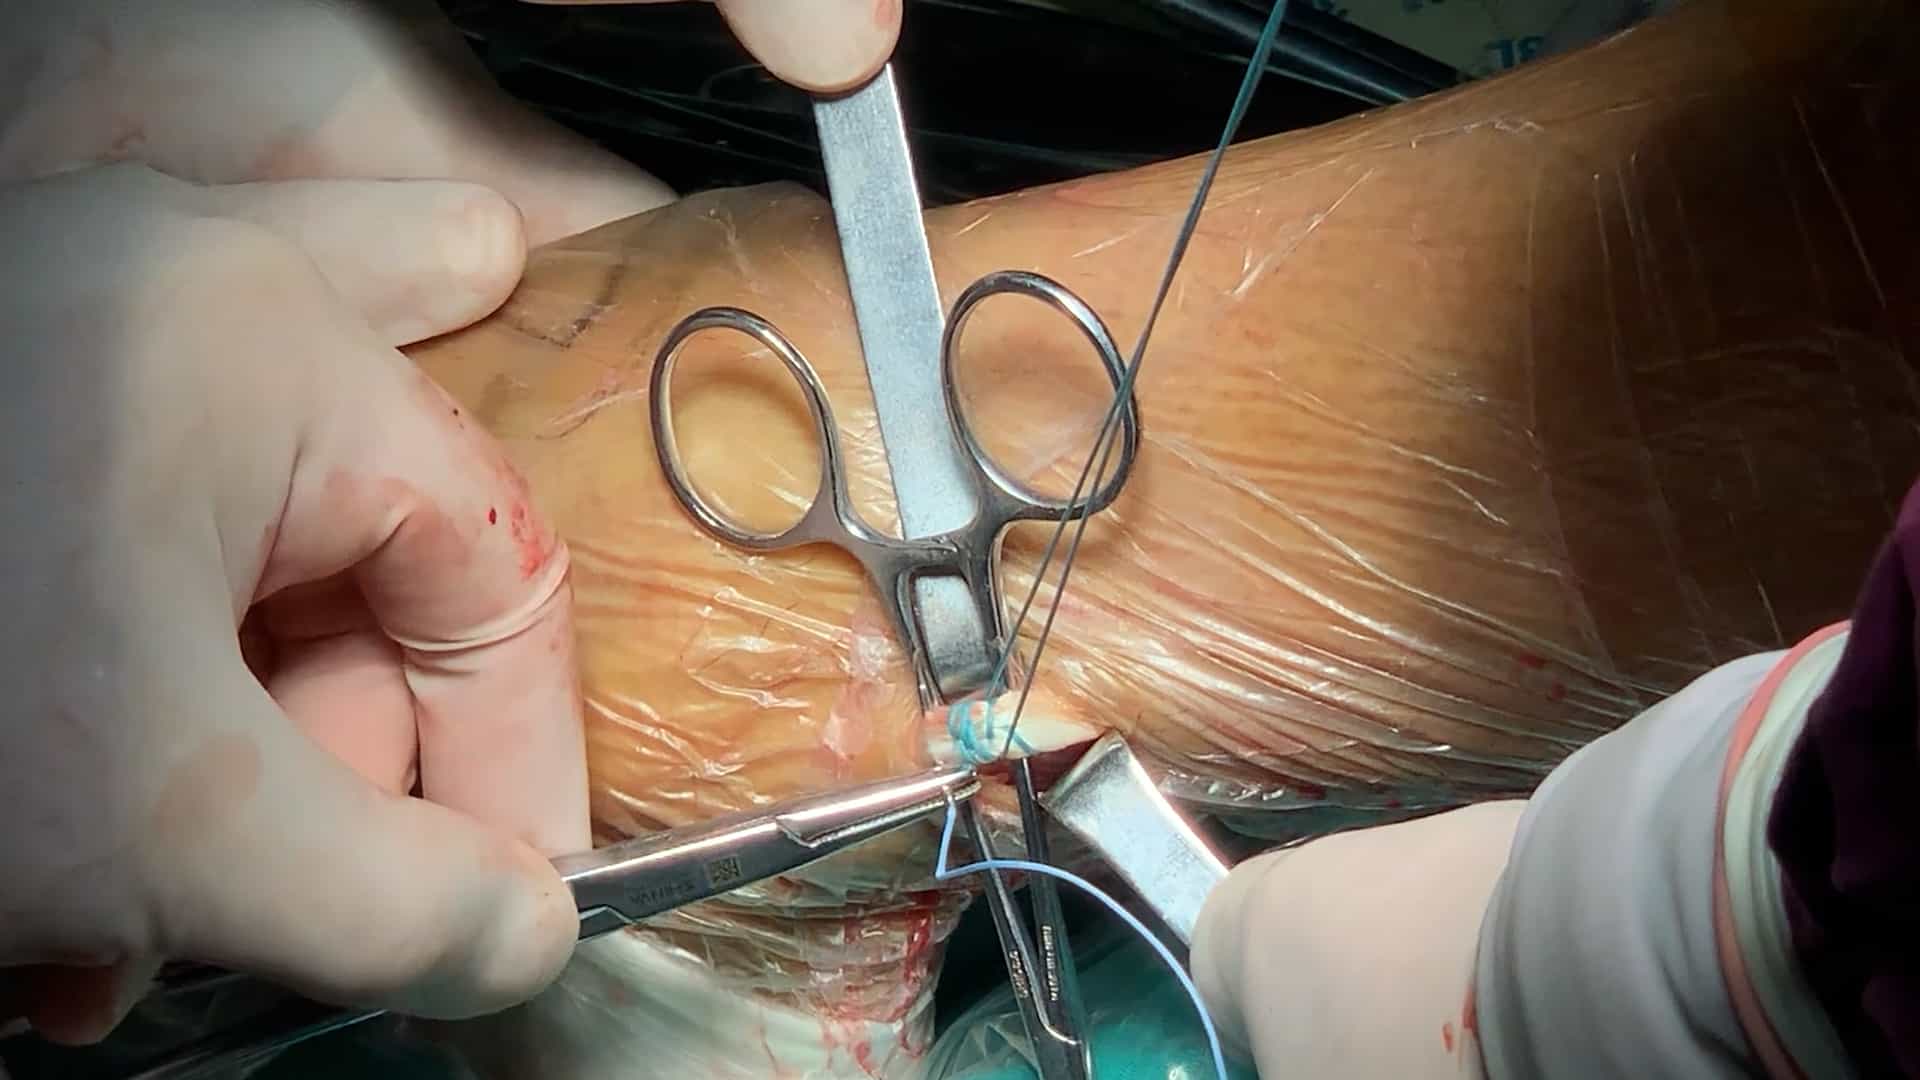

Harvesting of Peroneus Longus Tendon Autograft
Published on: September 2, 2025
Superior Fulcrum Reconstruction for Massive Irreparable Rotator Cuff Tears Using the Peroneus Longus Tendon in 2
Kehao Wang1, Run Fang1, Guang Chen1
1Department of Orthopedics, The Third Affiliated Hospital of Anhui Medical University (The First People's Hospital of Hefei), Hefei, Anhui, China. K.W. and R.F. contributed equally to this article.

Background:
Massive and irreparable rotator cuff tears (MIRCTs) pose unique challenges, and clinicians have explored a variety of surgical approaches to manage them. However, the optimal treatment strategies for MIRCT remain widely debated.
Purpose:
To investigate the biomechanical effects of 2 superior fulcrum reconstruction (SFR) techniques-using either 2 halved autologous peroneus longus tendons (SFR-H) in a sutured bridge configuration or a single entire autologous peroneus longus tendon (SFR-E) in an "X" configuration-on MIRCT in a static biomechanical setup. This study explores the biomechanical implications of these methods, aiming to address MIRCTs affecting the entire supraspinatus tendon and 50% of the infraspinatus tendon.
Study Design:
Controlled laboratory study.
Methods:
Eight cadaveric shoulders were subjected to biomechanical testing under 4 different conditions: Intact, MIRCT, SFR-E, and SFR-H. These tests were conducted at 0°, 30°, and 60° of glenohumeral abduction. The parameters measured included the rotational range of motion, superior translation of the humeral head, and subacromial contact pressure. Statistical analysis was performed using repeated-measures analysis of variance with Tukey post hoc tests, with significance set at P < .05.
Results:
The MIRCT condition led to a significant increase in the superior translation of the humeral head at all tested abduction angles (P < .05 for all). By contrast, SFR-E significantly reduced this translation across all angles (P < .05 for all), while SFR-H effectively reduced it at 0° and 30° (P < .05 for both). After MIRCT, subacromial contact pressure significantly increased at all tested abduction angles compared with the Intact state (P < .05 for all). Following SFR-E, significant pressure reductions were observed at 0° and 30° abduction angles (P < .05 for both). Similarly, SFR-H led to significant pressure reductions at all abduction angles (P < .05 for all).
Conclusion:
Compared with MIRCT, both SFR-H and SFR-E techniques significantly reduce superior translation of the humeral head and subacromial contact pressure, without limiting the range of motion of the humerus. In cadaveric biomechanical experiments, the use of peroneus longus tendon for SFR via bone tunnels has been proven to be a reliable method. Additionally, peroneus longus tendon is a viable source for autografting.
Clinical Relevance:
The results of this study are significant for patients suffering from MIRCTs, as they demonstrate that both surgical techniques may be used to treat these tears, potentially improving shoulder function and alleviating associated symptoms. The success of the cadaveric experiments lays the groundwork for further clinical trials.
Related Concept Videos
 01:12
Carbon Skeletons
 01:31
Bone Remodeling and Repair
 01:11
Deformation of Member under Multiple Loadings
In the case of a member with a variable cross-section, the strain is not constant but depends on the position. The deformation of an...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: