Related Experiment Video
Updated: Sep 16, 2025

Transtubular Endoscopic Posterolateral Decompression for L5-S1 Lumbar Lateral Disc Herniation
Published on: October 14, 2022
Full-endoscopic extraforaminal lumbar discectomy: Use of 3-D image-guidance can mitigate risks and overcome steep
Anwesha Dubey1, Abhijith R Bathini1, Katherine Anastasi1
1Department of Neurological Surgery, Mayo Clinic, Phoenix, AZ, USA.

Abstract:
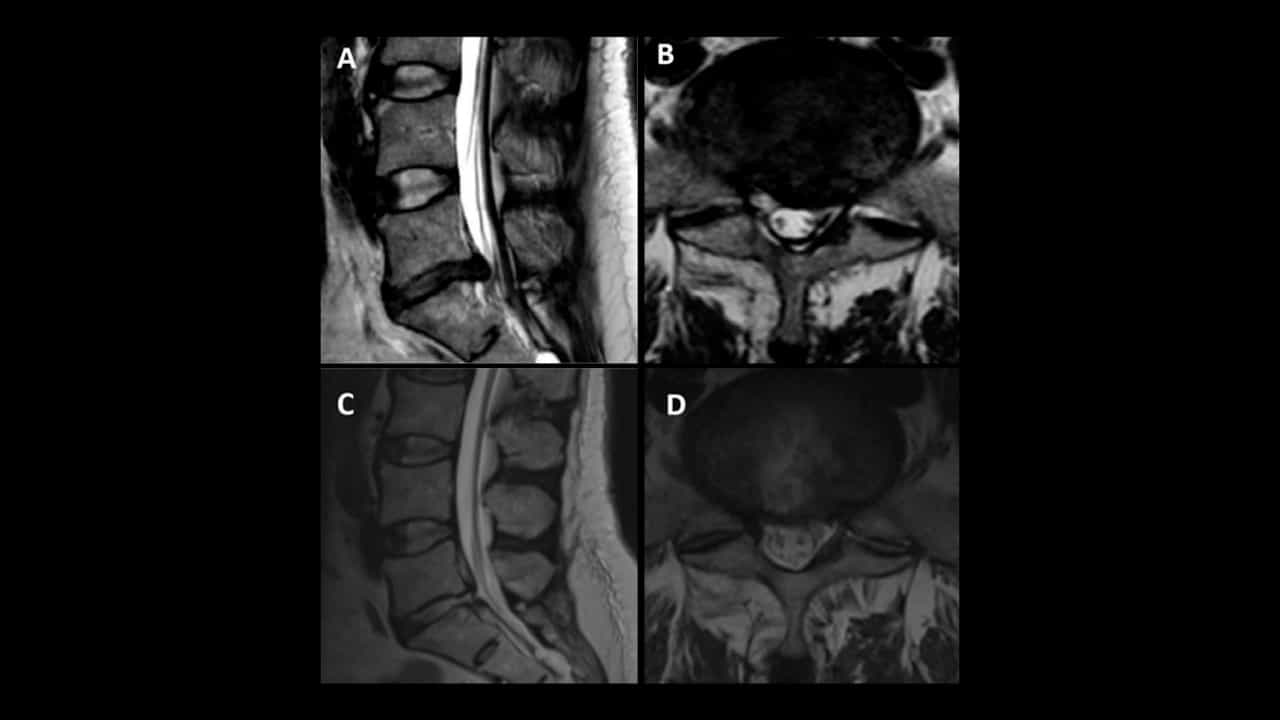
This opertive video describes a full endoscopic extraforaminal lumbar discectomy performed using 3D image guidance in a 60-year-old female who presented with three months of debilitating right leg pain following a pickleball injury. The patient exhibited classic signs of L4 radiculopathy, including knee extension and ankle dorsiflexion weakness, a diminished patellar reflex, and a positive straight leg raise test. MRI revealed a large right extraforaminal disc extrusion at L4-5 compressing the L4 nerve root. After failure of conservative management with NSAIDs, physical therapy, and epidural injections, surgical intervention was indicated due to progressive neurological decline. A uniportal endoscopic extraforaminal approach was selected to target the extraforaminal pathology while preserving bony structures and minimizing soft tissue trauma. Surgical planning using neuronavigation, key procedural steps and technical tenets are emphasized throughout the video. Preoperative imaging, including standing X-rays and axial T2-weighted MRI, guided trajectory planning and localization of the displaced nerve root. Intraoperative 3D neuronavigation and fluoroscopy were utilized for precise docking at the superior articulating process of L5. A foraminoplasty expanded Kambin's triangle, enabling safe access for the working channel and direct visualization of the compressed nerve root. Diskectomy was performed under continuous endoscopic visualization. Great care was taken to avoid dorsal root ganglion injury and manage any vascular structures. Extraforaminal fragments were mobilized and removed using up-angled forceps with minimal nerve manipulation. Overall, this approach minimized muscle retraction, reduced blood loss, and preserved posterior spinal elements, avoiding the instability risk associated with facetectomy-based techniques. Postoperatively, the patient was discharged the same day with immediate symptom relief. By the four-week follow-up, motor strength had improved, and by three months, she reported complete resolution of symptoms and returned to full activity. This case highlights the utility of 3D image-guided endoscopic techniques in managing complex extraforaminal lumbar disc herniations. It offers a safe and effective minimally invasive alternative to traditional microscopic decompression, rendering this technique particularly appealing for avoiding fusion and preserving spinal stability. As the popularity of high-impact recreational sports like pickleball increases, clinicians should remain vigilant for lumbar disc injuries and consider advanced minimally invasive options for surgical management.