Related Experiment Video
Updated: Sep 16, 2025
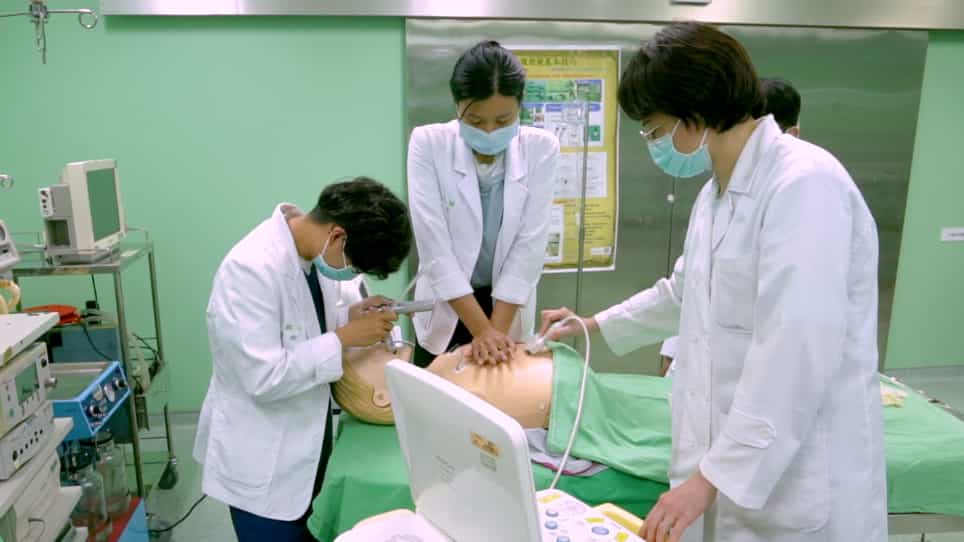

Ultrasonographic Assessment During Cardiopulmonary Resuscitation
Published on: October 24, 2020
Prehospital CPR for Traumatic Arrest: Can Prehospital Variables Help Identify Futile Transport?
Lorena Garcia1, Hye Kwang E Kim1, Amy H Kaji2
1Department of Surgery, Harbor-UCLA, Torrance, CA, USA.

Abstract:
Resuscitative efforts (RE) for patients suffering cardiac arrest following trauma require significant prehospital (PH) and hospital resources. Patients who are transported and undergo immediate termination of resuscitative efforts (ITRE) and declared dead on arrival (DOA) may represent a population for whom improved triage can conserve hospital resources. Methods: We sought to identify PH variables associated with DOA/ITRE. 405 trauma patients who had PHCPR from 2014 to 2023 at a Level 1 trauma center were included. Clinical variables analyzed included demographics, mechanism of injury (MOI), PHRE, and hospital RE. The primary outcome of interest was DOA/ITRE. Results: Most patients were male (80.5%), with median age 35, (IQR [25-50]), suffered a penetrating MOI (56.5%), and were severely injured (ISS 34, IQR [25-75]). 102 (25.2%) patients had DOA/ITRE; they tended to be older (41.5 [29-53] vs. 32 [24-47], P = 0.01), were more likely to have a blunt MOIs (52/176 patients (29.6%) vs 50/229 patients (21.8%), P = 0.007), and less likely to have PH interventions (30.3% vs. 69.7%, P = 0.004). When stratified by MOI, patients with penetrating injuries spent a significantly shorter amount of time in the ED (6.3 vs 12.4 min, P <0.001), while in those with blunt injuries did not (10.6 vs 12.5 min, P = 0.3). Discussion: More than 25% of transported patients following traumatic arrest undergo DOA/ITRE. These patients were more likely to have a blunt MOI, older age, and fewer PH interventions. Improved triage of patients in the field may help conserve PH and hospital resources for patients more likely to benefit from transport.

Related Concept Videos
 01:21
Cardiopulmonary Resuscitation I: Adult
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:23
Acute Respiratory Failure-IV
 01:23
Cardiopulmonary Resuscitation III: AED Use
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Acute Coronary Syndrome III: Diagnostic Studies