Related Experiment Video
Updated: May 7, 2026


Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Clinical outcomes following implementation of an operative vaginal birth safety bundle: a prospective observational
Sasha M Skinner1, Peter Neil2, Nadine Murray2
1Department of Obstetrics and Gynaecology, Women's and Newborns, Monash Health, Clayton, Victoria, Australia; Department of Obstetrics and Gynaecology, Monash University, Clayton, Victoria, Australia.

Background:
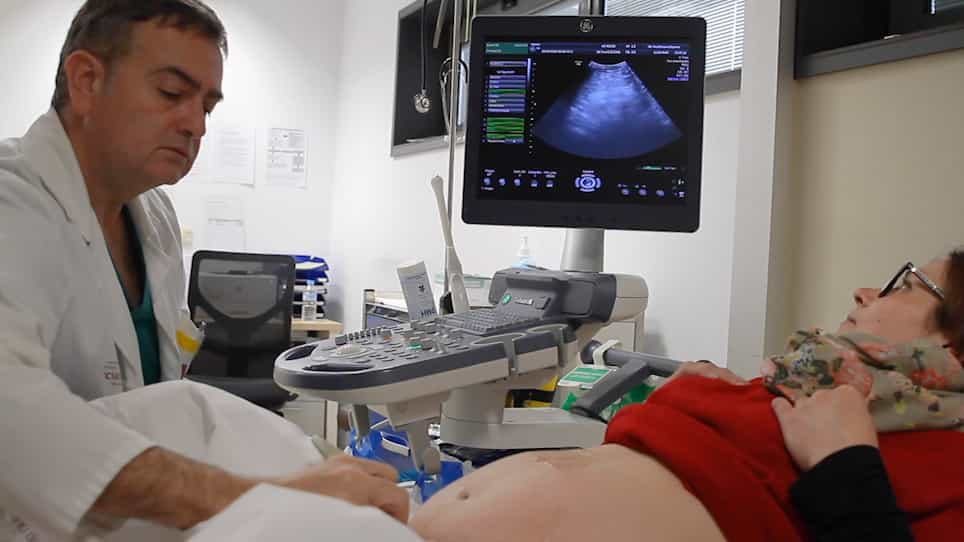
Poor outcomes from operative vaginal birth are associated with failure to recognize malposition, lack of interdisciplinary communication, and deviation from accepted guidelines. We implemented a safety bundle including routine intrapartum ultrasound, a structured time-out and procedural checklist, birth experience survey, and a postnatal debrief pathway.
Objective:
To compare clinical outcomes from operative vaginal birth before and after the implementation of a safety bundle at Monash Health, Melbourne, Australia.
Study Design:
We compared clinical outcomes prebundle vs postbundle implementation for all women having an operative vaginal birth or fully dilated cesarean of a term singleton cephalic nonanomalous fetus at Monash Health. Data were prospectively collected following bundle implementation from August 2022 to August 2024 and compared to a historical control cohort from November 2019 to November 2021, before the initial pilot of the bundle. We performed an interrupted time-series analysis to assess change in outcome trends over time. The primary outcome was a composite of neonatal morbidity, including Apgar score <7 at 5 minutes, cord lactate >8 mmol/L, severe birth trauma, intubation or cardiac compressions, therapeutic cooling, and neonatal intensive care unit admission.
Results:
We included 2427 and 2914 births meeting the inclusion criteria in the postbundle and prebundle periods, respectively. Following bundle implementation, mothers were older (30.5±4.8 vs 30.1±4.9, P=.006), at a slightly later gestational age (39.5 [38.7, 40.3] vs 39.4 [38.5, 40.2], P=.003), it was more common for specialist obstetricians to attend the birth (56.1% vs 47.7%, P<.001), for ultrasound to be performed (55.8% vs 5.0%, P<.001), and for vaginal station to be low (54.1% vs 49.4%, P=.001), while it was less common to have occiput anterior position (71.2% vs 74.4%, P=.03) or missing documentation of clinical assessment (0.8% vs 3.4%, P<.001). There were no significant differences in rates of forceps, vacuum, or fully dilated cesarean overall; however, following implementation, there were more cesareans without attempted operative vaginal birth (9.5% vs 7.8%, P=.03), fewer births with ≥4 tractions or ≥2 cup detachments (5.8% vs 8.5%, P<.001), and less unsuccessful operative vaginal births (6.3% vs 8.3%, P=.005). There were no significant differences in the predefined neonatal composite morbidity (14.2% vs 13.9%, P=.80); however, there were significantly fewer neonates delivered in an unexpected position (0.7% vs 2.8%, P<.001), lower rates of severe neonatal birth trauma (1.3% vs 2.5%, P<.001), and lower rates of neonatal intensive care unit admissions (1.8% vs 2.7%, P=.02). There were higher rates of postpartum hemorrhage >1000 mL (17.6% vs 15.2%, P=0.02), but no differences in blood transfusions (3.7% vs 3.8%, P=0.96) or obstetrical anal sphincter injury (4.8% vs 5.4%, P=0.38). Interrupted time-series analysis demonstrated significant step reductions in fully dilated cesarean (-5.9%; 95% confidence interval, -11.77 to 0.11; P=.05), unsuccessful operative vaginal birth attempt (-5.1%; 95% confidence interval, -8.74 to 1.37; P=.008), and cesarean for unsuccessful operative vaginal birth (-2.4%; 95% confidence interval, -4.48 to 0.31; P=0.03), with no significant difference in neonatal or maternal morbidity.
Conclusion:
Implementation of a safety bundle for operative vaginal birth reduced the rates of unsuccessful operative vaginal birth and may reduce rates of neonatal birth trauma and neonatal intensive care unit admissions.