Related Experiment Video
Updated: Sep 16, 2025
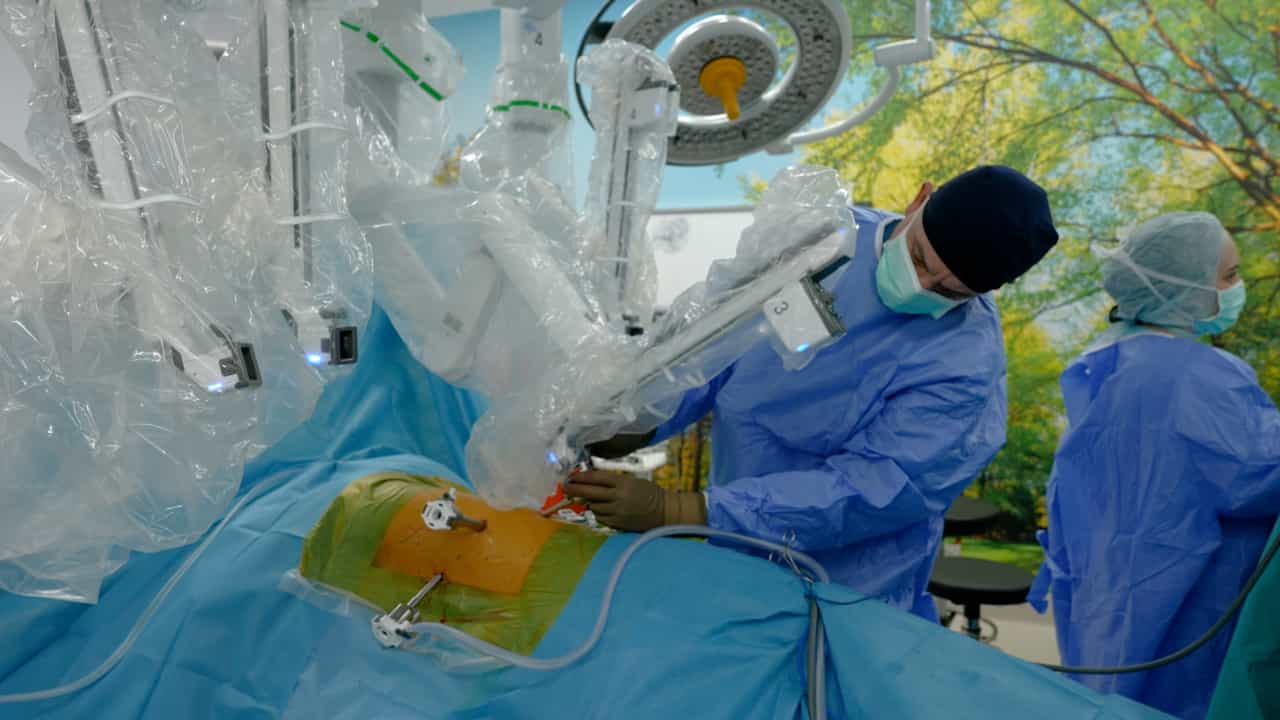
Laparoscopic Left Hemihepatectomy Combined with Caudate Lobe Resection
Published on: April 11, 2025
Lobectomy is the preferred choice rather than sublobar resection for centrally located clinical stage 1 non-small
Satoshi Takamori1,2, Marina Nakatsuka2, Hikaru Watanabe1
1Department of Surgery II, Faculty of Medicine, Yamagata University, Yamagata 990-9585, Japan.

Objectives:
Tumour location can affect clinicians' decisions regarding the surgical procedure, especially when choosing between lobectomy and segmentectomy. The biological behaviour of clinical stage I non-small cell lung cancer (NSCLC) may differ based on tumour location. We aimed to explore the biological behaviour of centrally located (CL) clinical stage I NSCLC and to identify which surgical procedure is more appropriate for such tumours.
Methods:
This retrospective study included 719 patients who underwent curative operations for stage I NSCLC between April 2004 and December 2023. The biological behaviour of the tumours was analysed based on tumour location. Overall and recurrence-free survivals in patients who underwent lobectomy or more extensive procedures, including hilar and mediastinal lymph node dissection, were assessed based on tumour location.
Results:
A total of 124 (17.2%) and 595 (82.8%) patients were included in the CL and peripherally located groups, respectively. The CL group had a significantly higher standardized uptake value maximum on positron emission tomography/computed tomography, a higher-grade adenocarcinoma subtype, and a higher frequency of lymph node metastasis than the peripherally located group. In multivariable analysis, CL and radiologically pure solid tumours (consolidation/tumour ratio = 1) were significant factors for occult lymph node metastasis. No significant difference was observed in survival based on tumour location.
Conclusions:
Centrally located clinical stage I NSCLCs tend to be hypermetabolic and have a potential risk of lymph node metastasis. Lobectomy could be a better treatment option for CL clinical stage I NSCLC.