Related Experiment Video
Updated: Sep 16, 2025


Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
Seeing the Stricture Clearly: Independent Determinants of Sonourethrography Precision in Urethral Stricture Disease
Kevin Miszewski1, Jakub Krukowski1, Laura Miszewska2
1Department of Urology, Medical University of Gdańsk, 17 Smoluchowskiego St., 80-214 Gdańsk, Poland.

Abstract:
Background: Urethral stricture disease involves fibrotic scarring that narrows the urethral lumen and can occur at any site. Sonourethrography (SUG) is increasingly used because it depicts both luminal anatomy and periurethral fibrosis, yet little is known about patient or lesion features that influence its diagnostic performance. Methods: We conducted a prospective single-center study of 170 men who underwent SUG before anterior urethroplasty between May 2016 and May 2021. Anthropometric data, comorbidities, and detailed ultrasonographic measurements were recorded and compared with intra-operative findings, which served as the reference standard. Accuracy was analyzed with Wald chi-square testing and Spearman correlation. Results: SUG length estimates matched intra-operative measurements in 139/170 strictures (81.8%). Length accuracy was higher in patients ≥ 60 years (89.2% vs. 77.0%, p = 0.03) and in those with type 2 diabetes (92.3% vs. 80.9%, p = 0.02) in conditions associated with pronounced spongiofibrosis that enhances echo contrast. Among stricture-specific factors, proximal location (63.6% vs. 84.5%, p = 0.01) and complete luminal occlusion (68.8% vs. 84.8%, p = 0.02) reduced precision, largely because deeper anatomy and absent saline flow hinder acoustic delineation. The Chiou ultrasonographic grade was the strongest determinant of performance; higher grades yielded clearer margins and better length estimation (p < 0.001). Conclusions: SUG is a reliable bedside technique for assessing anterior urethral strictures, but its accuracy varies with age, diabetes status, stricture site, degree of occlusion, and fibrosis grade. Recognizing these determinants allows clinicians to judge when SUG alone is sufficient and when complementary imaging or heightened caution is warranted. The findings support tailored imaging protocols and underscore the need for multi-center studies that include operators with diverse experience to confirm generalisability.


Related Concept Videos
 01:19
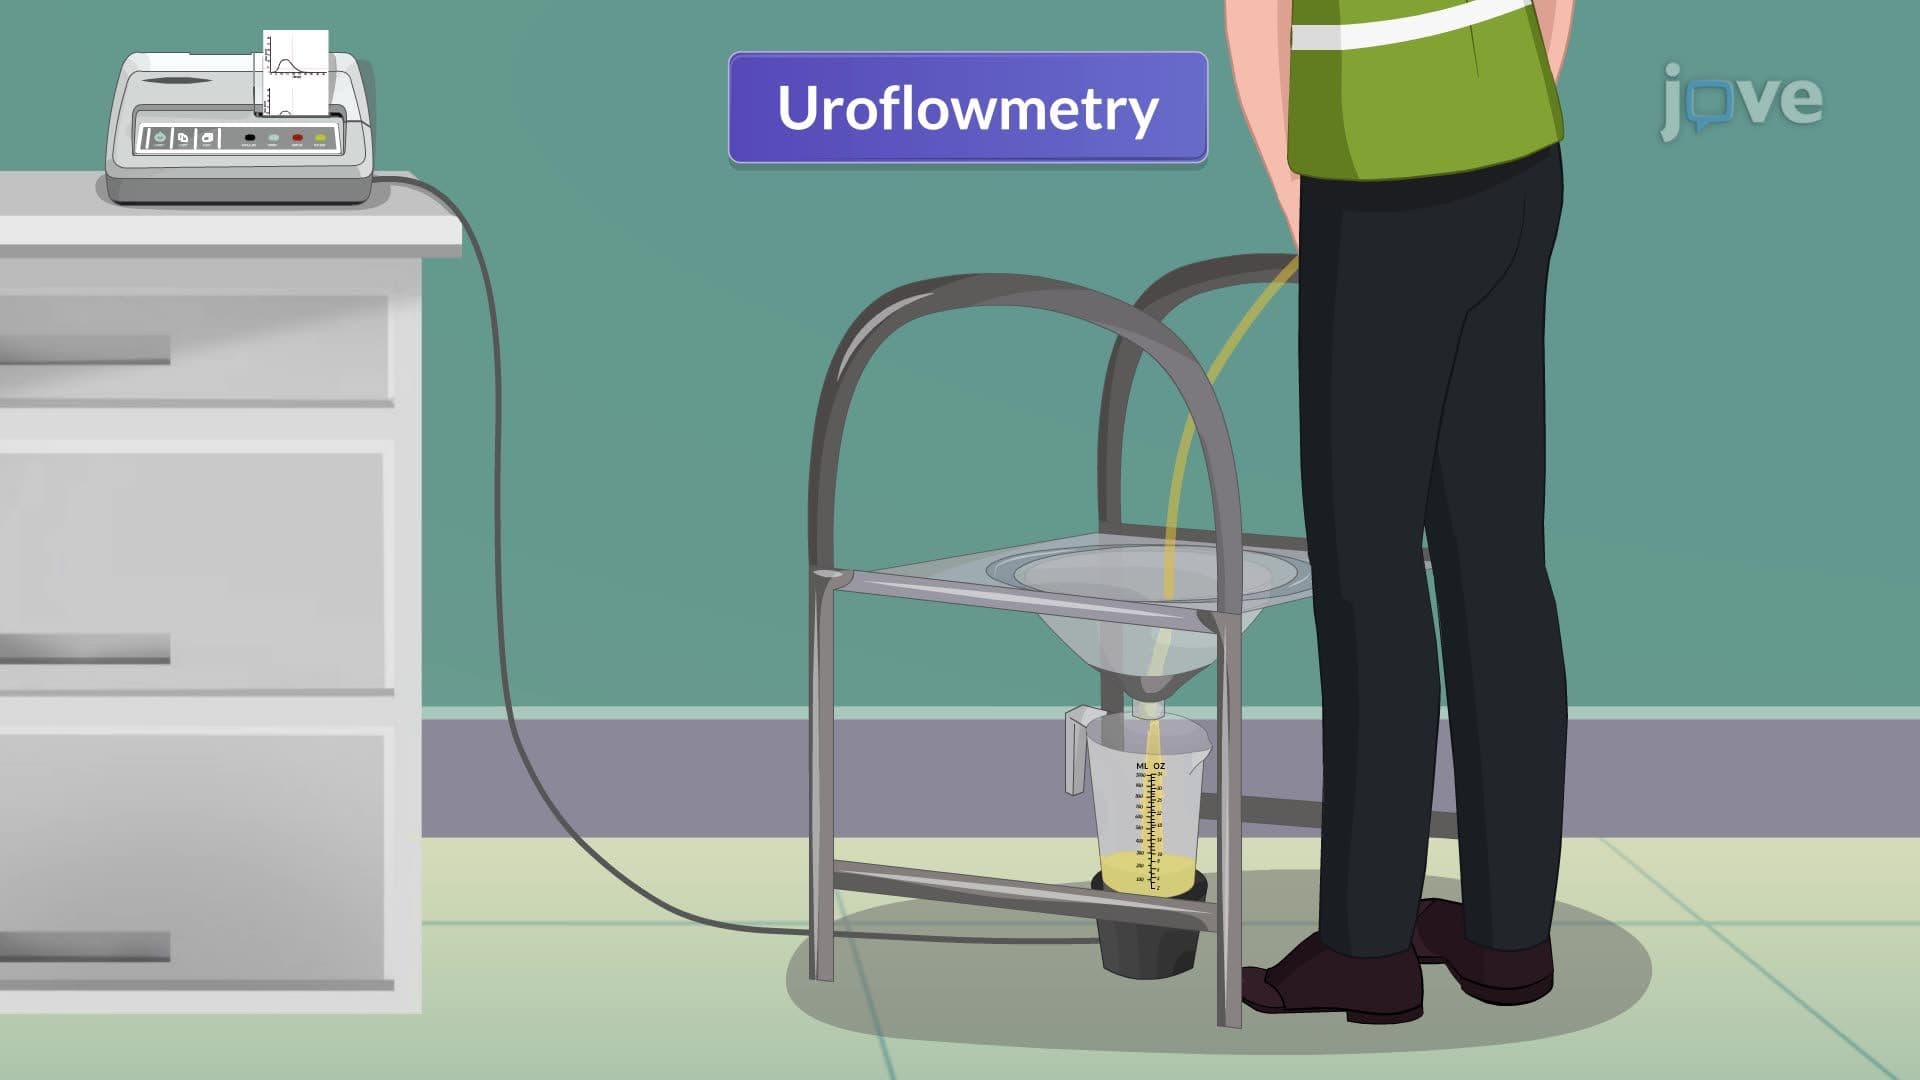
Urodynamic Studies: Uroflowmetry
 01:28
Urologic Endoscopic Procedure: Cystoscopic Examination
 01:22
Imaging Studies VI: Voiding Cystourethrography and Cystography
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:24
Imaging Studies II: Ultrasonography
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations