Related Experiment Video
Updated: Jul 28, 2026

Optimized System for Cerebral Perfusion Monitoring in the Rat Stroke Model of Intraluminal Middle Cerebral Artery Occlusion
Published on: February 17, 2013
Head Positioning for Stroke Blood Flow Augmentation Assisting Reperfusion Therapies Study
Rudy Goh1, Edmund Cheong2, Lizzie Dodd2
1Department of Neurology, Royal Adelaide Hospital, Adelaide, South Australia, Australia, rudy.goh@sa.gov.au.

Abstract:
Introduction: It is uncertain whether lowered head position meaningfully improves cerebral perfusion in ischaemic stroke. We performed a prospective, single-arm, single-centre, self-controlled, non-randomised, pre-post-intervention study, testing whether 20-degree head-down (Trendelenburg) positioning in patients with acute stroke improves perfusion of ischaemic brain tissue, as measured by automated quantitative computed tomography perfusion (CTP).
Methods:
We enrolled patients aged ≥60, 0-24 h after acute stroke onset, with ≥30 mL anterior circulation CTP lesion volume (delay time [DT] >3 s, MIStar software). CTP was acutely repeated after 5 min of on-table 20-degree Trendelenburg positioning (achieved by a custom-designed foam wedge). Clinical severity (National Institutes of Health Stroke Scale [NIHSS]) and blood pressure were recorded in routine (30° up) and Trendelenburg position. Trendelenburg positioning was maintained for 24 h if lesion volume significantly decreased (≥5 mL) and stroke reperfusion was suboptimal or undetermined.
Results:
We enrolled 25 patients {14 (56%) male, age 76 (interquartile range [IQR] 70-85), baseline modified Rankin scale score 0 [IQR 0-0], median pre-CT NIHSS 20 [IQR 13-25]}. All patients had anterior circulation large vessel occlusion (LVO), 15/25 (60%) M1 middle cerebral artery (MCA) occlusion, 6 (24%) proximal M2 MCA, and 4 (16%) ICA. Stroke aetiology was predominantly cardioembolic (15/25 [60%]). Median DT >3 lesion volume was reduced by 18 mL [2-48] following Trendelenburg compared with conventional horizontal CT positioning (114 mL [94-204] vs. 149 mL [76-153]; p = 0.0027). Systolic blood pressure was unaltered (mean 148 mm Hg [±standard deviation 29] vs. 143 [±27]; p = 0.129). Head position did not alter clinical severity (post-CT NIHSS 13 [IQR 9-28] in both positions). A significant lesion volume reduction with Trendelenburg positioning was seen in 15/25 patients (60%); 7 received continued Trendelenburg positioning (6 due to incomplete reperfusion following thrombectomy). Head-down positioning caused no serious adverse events and was mostly well tolerated (6/7 [86%]).
Conclusion:
Head-down (Trendelenburg) positioning appears to modestly improve penumbral perfusion in acute LVO ischaemic stroke and is generally well tolerated. Clinical benefits of this approach may be best tested in patients for whom reperfusion is delayed or not achieved.
.More Related Videos

Related Concept Videos
 01:29
Blood Flow
 01:17
Autoregulation of Blood Flow
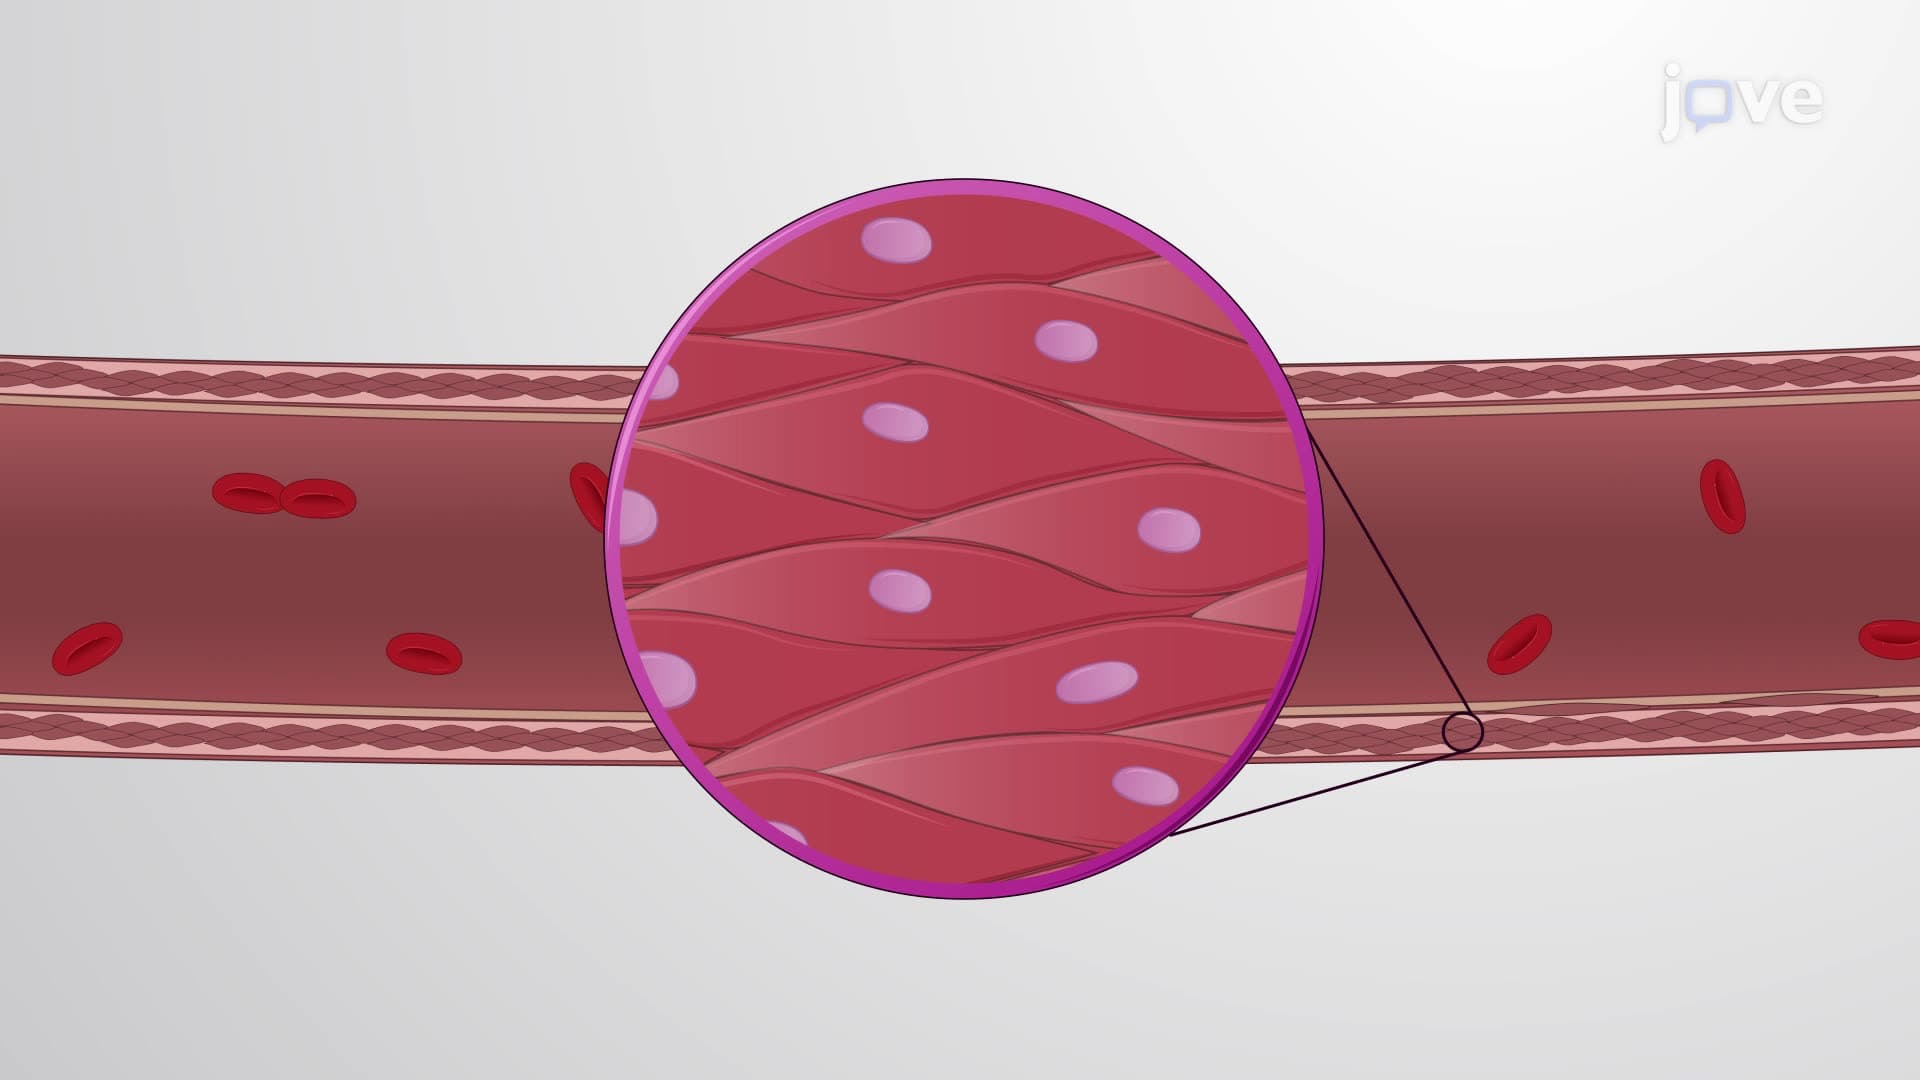
Chemical Signaling in Autoregulation
Chemical signaling operates at the precapillary sphincter level, inciting either contraction or relaxation.
 01:27
Applications of Integration to Find Blood Flow