Related Experiment Video
Updated: Sep 15, 2025
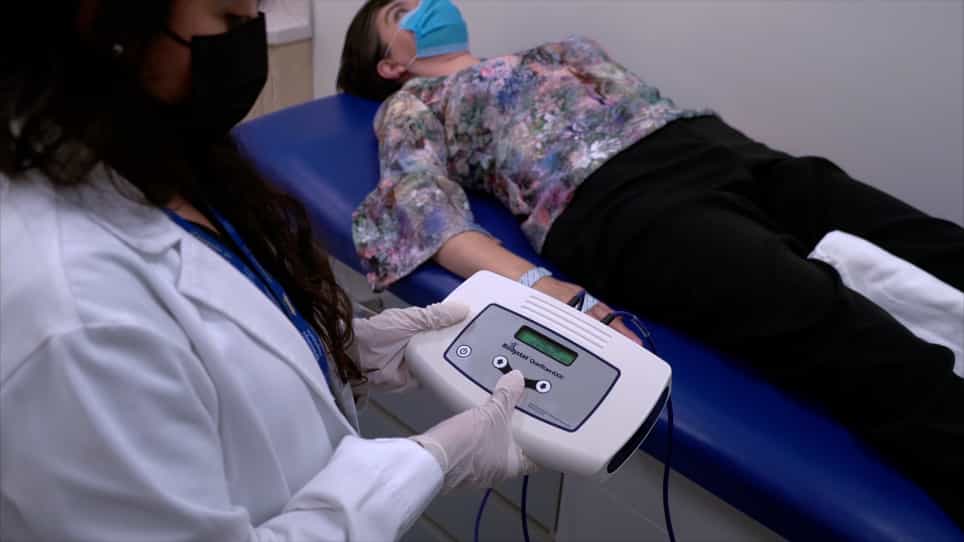

Evaluation of Fluid Overload by Bioelectrical Impedance Vectorial Analysis
Published on: August 17, 2022
The determinants of fluid accumulation in critically ill children: a prospective single-center cohort study
Shannon Mohoric1, Rashid Alobaidi1, Tegan McGraw2
1Department of Pediatrics, Division of Pediatric Critical Care Medicine, University of Alberta and Stollery Children's Hospital, 4-546 Edmonton Clinic Health Academy; 11405 112 Street, Edmonton, AB, T6G 1C9, Canada.

Insights
In critically ill children, higher fluid intake, especially maintenance fluids, is the main cause of fluid accumulation (FA). This FA is linked to longer intensive care stays.
Area of Science:
- Pediatric critical care medicine
- Intensive care unit (ICU) management
- Fluid balance and resuscitation
Background:
- Fluid accumulation (FA) is a significant concern in intensive care, correlating with increased morbidity and mortality.
- Understanding the sources of FA in pediatric intensive care is crucial for optimizing patient outcomes.
Purpose of the Study:
- To identify and quantify the primary contributors to fluid intake in critically ill children.
- To investigate the association between fluid intake, fluid accumulation, and clinical outcomes in this population.
Main Methods:
- A prospective cohort study was conducted in a tertiary pediatric intensive care unit.
- Fluid intake and output were meticulously monitored, with a focus on maintenance, nutrition, medications, and resuscitative fluids.
- Statistical analyses explored associations between fluid intake, FA exceeding 5% of body weight, and days free from mechanical ventilation and intensive care.
Main Results:
- Maintenance fluids constituted the largest proportion (37.4%) of total fluid intake, followed by nutrition (23.2%).
- Higher total fluid intake and output were observed in children with peak FA >5% compared to those with FA ≤5%.
- Total fluid intake was independently associated with FA >5% (OR 1.09) and peak FA% was linked to fewer intensive-care-free days (Effect Size -0.30).
Conclusions:
- Increased fluid intake, particularly maintenance fluids, is the primary driver of FA in critically ill children, rather than decreased output.
- Optimizing maintenance fluid calculations warrants further investigation to mitigate FA and improve patient recovery.
Background:
Fluid accumulation (FA) is associated with morbidity and mortality in intensive care. We aimed to determine sources of FA in critically ill children admitted to pediatric intensive care.
Methods:
Prospective cohort study of children in a university affiliated tertiary pediatric intensive care unit. Primary outcome was to describe contributors to fluid intake. Secondary outcomes were independent associations between fluid intake and FA > 5%, ventilator-free days, and intensive-care-free days.
Results:
Of patients admitted to intensive care, 99/120 (83%) met eligibility criteria. Median total fluid intake was median [interquartile range (IQR)] 46.9 [30.3, 72.1] ml/kg/day, and median [IQR] fluid output was 26.3 [15.1, 49.8] ml/kg/day. The largest contributors to fluid intake were maintenance (37.4%; IQR 20.0, 57.3), nutrition (23.2%; IQR 6.8, 58.1), medications (7.8%; IQR 2.9, 21.8), and resuscitative fluid (4.2%; IQR 0, 18). Children with peak FA > 5% versus FA ≤ 5% had higher total fluid intake (67.8 vs. 30.3 ml/kg/day; odds ratio (OR) 1.09 [95% confidence interval (CI), 1.06, 1.14)] and output [36.9 vs. 19.5 ml/kg/day; OR 1.04 (95% CI, 1.02, 1.06)], and higher volumes of maintenance, nutrition, and medications, but not resuscitative fluid. Total fluid intake was independently associated with FA > 5% (OR 1.09; 95% CI 1.05, 1.14; p < 0.001). At 28 days, peak FA% was independently associated with fewer intensive-care-free days [Effect Size - 0.30 (95% CI - 0.45, - 0.16), p < 0.001)].
Conclusions:
Higher fluid intake, rather than reduced output, was the predominant factor in FA, with maintenance fluid being the largest source of intake. Future research should evaluate the impact of optimized maintenance fluid calculations.
Related Concept Videos
 01:22
Acute Kidney Injury VI: Nursing Management
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's...
 01:18
Fluid Movement Between Compartments
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:29
Disorder of Water Balance
Dehydration
Dehydration occurs when the body loses fluids (particularly water).
Causes:
The major causes of dehydration include excessive sweating, fever, vomiting, diarrhea, and diuresis.
Signs and Symptoms:
Symptoms primarily include intense...