Related Experiment Video
Updated: Sep 15, 2025
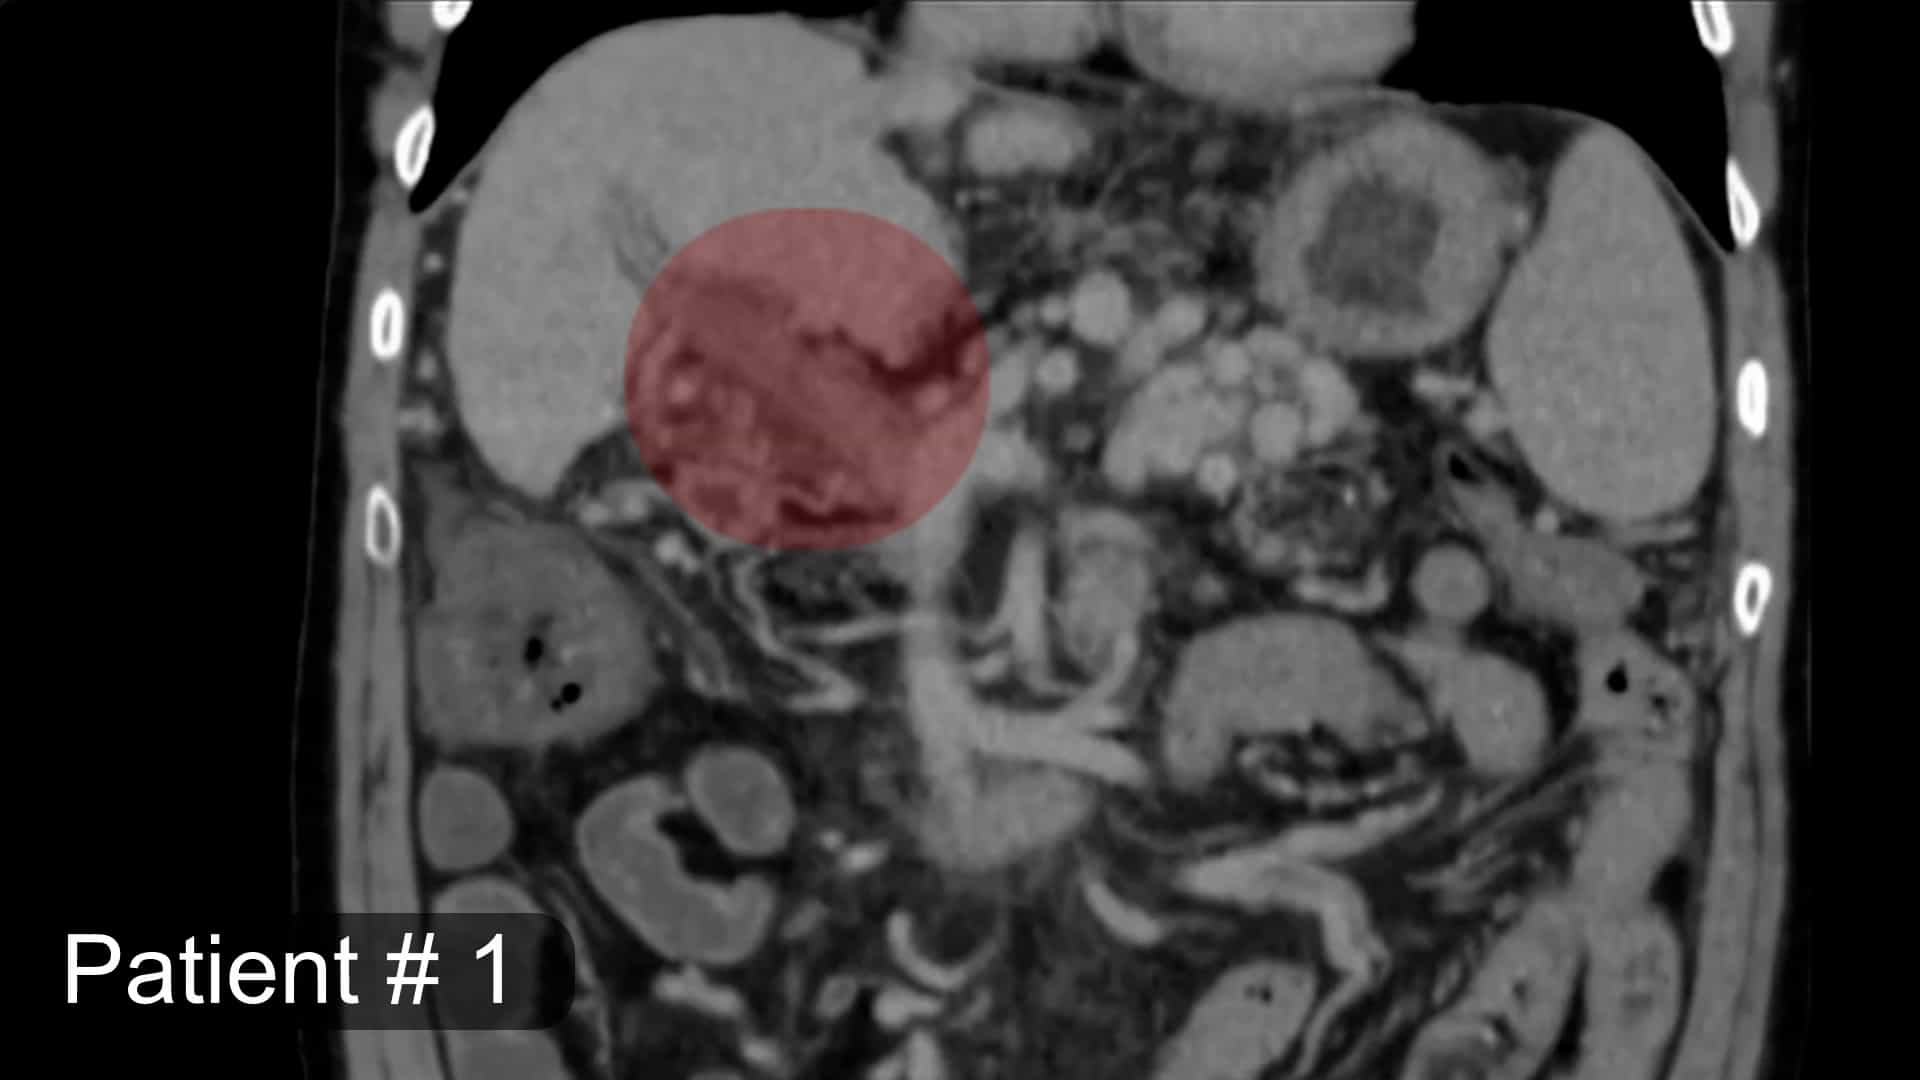

New Thrombectomy Technique for Total Portal Vein Thrombosis in Liver Transplantation
Published on: June 27, 2025
Risk of portal hypertensive complications preventable by TIPS in patients with ascites
Lorenz Balcar1,2, Marta Tonon3, Joan Valls4,5,6
1Division of Gastroenterology and Hepatology, Department of Medicine III, Medical University of Vienna, Vienna, Austria.

Background & Aims:
Transjugular intrahepatic portosystemic shunt (TIPS) is an effective treatment of recurrent/refractory ascites in patients with cirrhosis. The aim of this study is to identify patients with ascites as index decompensation who are at risk of developing portal hypertension (PH)-related complications within 12 months that seem preventable by TIPS.
Methods:
We included 451 patients from two tertiary care centres (Vienna and Padua, derivation cohort) with clinically significant ascites (grade 2/3) as a single first decompensating event and without contraindications for TIPS placement. Multivariable logistic regression analysis was used to identify variables independently associated with a composite endpoint of PH-related complications (encephalopathy excluded), liver transplantation, or liver-related death. A classification tree was used to identify patients at highest risk for these PH-related complications. Risk estimates were validated in a temporal validation cohort from Vienna (n = 84).
Results:
In the derivation cohort (mean age 56 ± 11 years; 69% male; 51% alcohol-related cirrhosis; 44% ascites grade 3; median model for end-stage liver disease [MELD] 12 points), 152 (34%) patients developed the composite endpoint within 12 months. A model including ascites grade, sodium, and MELD accurately predicted the occurrence of this composite endpoint (area under the receiver operator characteristics curve: 0.79 [95% CI: 0.75-0.84]). Two high-risk clusters were identified: patients with grade 3 ascites and either (i) sodium ≤135 mmol/L, or (ii) MELD ≥12 points, with a pooled absolute risk of 64.3% (derivation cohort) and 68.9% (validation cohort) to develop the composite endpoint.
Conclusions:
Patients with first decompensation caused by ascites grade 3 and either sodium ≤135 mmol/L or MELD ≥12 are at high risk for PH-related complications that are likely preventable by early TIPS placement. A trial investigating 'early' TIPS in this at-risk population is warranted.
Impact And Implications:
We identified ascites grade, sodium, and model for end-stage liver disease (MELD) as key predictors of portal hypertension-related complications that may be preventable by TIPS in patients with ascites. Specifically, patients with ascites grade 3 and either sodium ≤135 mmol/L or MELD ≥12 are at risk to experience early clinical deterioration and may benefit from TIPS. A trial investigating 'early' TIPS in this at-risk population is warranted.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:24
Esophageal Varices-I: Introduction
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management