Related Experiment Video
Updated: Aug 14, 2026
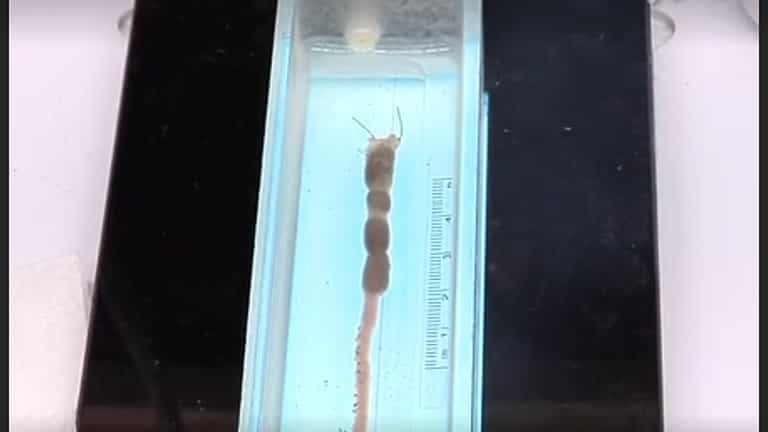
Gastrointestinal Motility Monitor (GIMM)
Published on: December 1, 2010
Excitatory response of guinea-pig myometrium to intravenous noradrenaline declines towards term

Guinea-pigs were anaesthetized at three stages of pregnancy. Intrauterine pressure was recorded for a 1-h control period and during 10-min intravenous infusions of noradrenaline at rates of 1.0 and 10 micrograms/(min X kg). The mean and maximum amplitude of contractions occurring during the infusions was compared with that of contraction cycles registered in the control period. At 18-21 and 35-43 days post coitum, noradrenaline invariably evoked a rapid and sustained rise in intrauterine pressure, the amplitude of the contractions being greater than during spontaneous contraction cycles recorded in the control period. In late pregnancy, 59-68 days p.c., infusion of 1.0 micrograms noradrenaline/(min X kg) failed to elicit a clear response; contractions occurring during infusion of 10 micrograms noradrenaline/(min X kg) had amplitudes similar to those of the control period and were without a sustained contracture. The absence of denervation hypersensitivity, despite the occurrence of sympathetic denervation in the course of pregnancy, may be due to a generalized effect on excitation-contraction coupling, possibly caused by relaxin.
Guinea-pigs were anaesthetized at three stages of pregnancy. Intrauterine pressure was recorded for a 1-h control period and during 10-min intravenous infusions of noradrenaline at rates of 1.0 and 10 micrograms/(min X kg). The mean and maximum amplitude of contractions occurring during the infusions was compared with that of contraction cycles registered in the control period. At 18-21 and 35-43 days post coitum, noradrenaline invariably evoked a rapid and sustained rise in intrauterine pressure, the amplitude of the contractions being greater than during spontaneous contraction cycles recorded in the control period. In late pregnancy, 59-68 days p.c., infusion of 1.0 micrograms noradrenaline/(min X kg) failed to elicit a clear response; contractions occurring during infusion of 10 micrograms noradrenaline/(min X kg) had amplitudes similar to those of the control period and were without a sustained contracture. The absence of denervation hypersensitivity, despite the occurrence of sympathetic denervation in the course of pregnancy, may be due to a generalized effect on excitation-contraction coupling, possibly caused by relaxin.
More Related Videos

Related Concept Videos
 01:23
Drugs Acting on Autonomic Ganglia: Stimulants
Ganglionic stimulants activate NM nicotinic receptors in autonomic ganglia, falling into two categories: nicotine mimetics [e.g., lobeline, dimethylpiperazine, tetramethylammonium] and muscarinic receptor agonists [e.g., muscarine, methacholine]. The first category's action is rapid and blocked by nicotinic receptor antagonists, while the second category's action is delayed and blocked by atropine-like agents. Nicotine, an alkaloid, affects the heart rate by stimulating sympathetic or...
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:28
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:19
Depolarizing Blockers: Pharmocokinetics