Related Experiment Video
Updated: Sep 14, 2025
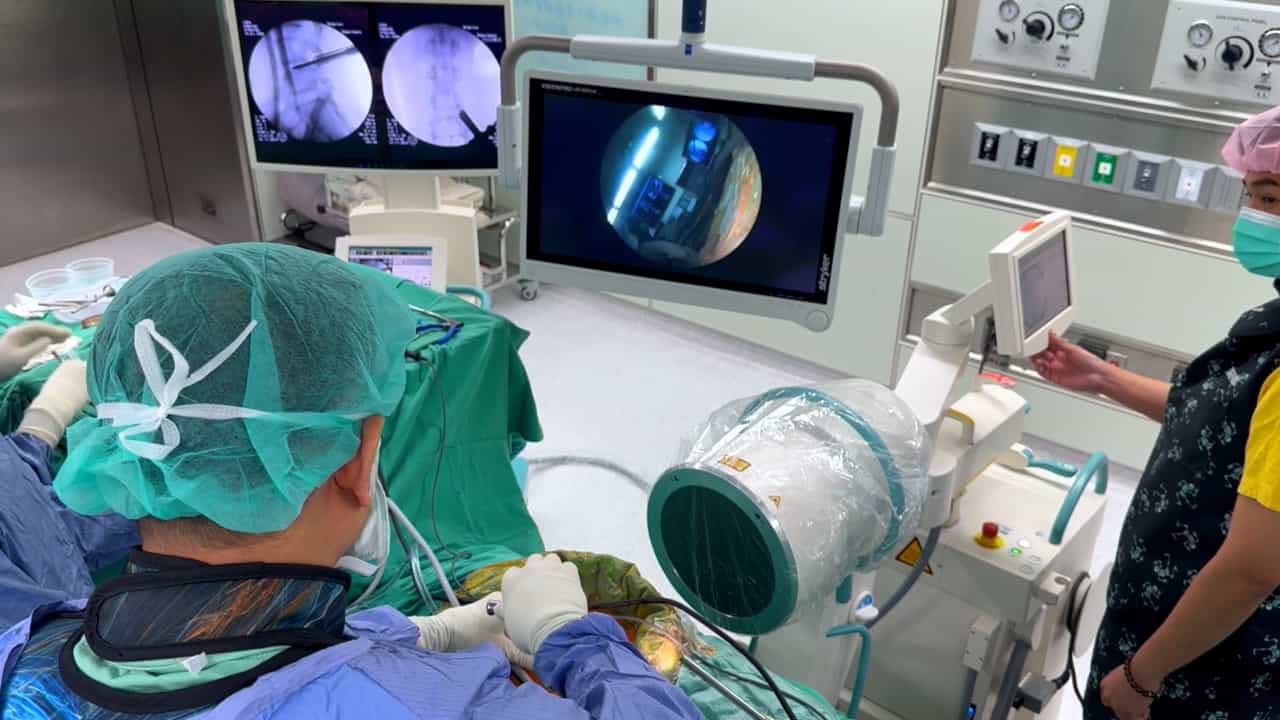

Uniportal Full Endoscopic Posterolateral Transforaminal Lumbar Interbody Fusion
Published on: June 6, 2025
Dynamic versus Fixed Lumbar Spondylolisthesis: Clinical, Radiographic, and Functional Outcomes Following
Barón Zárate-Kalfópulos1, Fernando Pesantez-Mochas1, Patricia Rojo-Castillo2
1Spine Surgery Division, National Institute of Rehabilitation Luis Guillermo Ibarra Ibarra, Mexico City, Mexico.

Background:
Lumbar spondylolisthesis (LS) is defined by vertebral displacement and can be categorized as dynamic or fixed based on intervertebral instability. Dynamic LS, characterized by greater mobility, may impact surgical outcomes. This study aimed to assess clinical and radiographic differences between dynamic and fixed LS in patients undergoing transforaminal lumbar interbody fusion (TLIF) and to determine an optimal cut-off for defining dynamic instability.
Methods:
This retrospective cohort included 76 patients with degenerative low-grade LS treated with TLIF between 2018 and 2020, with a minimum follow-up of 24 months. Dynamic and fixed LS were classified based on a displacement cut-off derived from receiver operating characteristic curve analysis. Clinical outcomes (Oswestry Disability Index, visual analog scale, 36-Item Short Form Health Survey) and radiographic parameters were evaluated preoperatively and at 6, 12, and 24 months postoperatively; the inter-rater variability (for 2 raters) was Cohen's kappa (κ = 0.776).
Results:
Receiver operating characteristic analysis identified 2.45 mm as the optimal displacement threshold to distinguish dynamic from fixed LS, with 95.5% sensitivity and 97.1% specificity. Dynamic LS was present in 63.4% of cases and demonstrated significantly higher preoperative listhesis and greater postoperative reduction loss. Despite these radiographic differences, patient-reported outcomes improved similarly in both groups over time.
Conclusions:
A displacement threshold of 2.45 mm effectively differentiates dynamic from fixed LS and may support surgical decision-making. While dynamic LS presents a higher risk of postoperative reduction loss, TLIF achieves comparable functional outcomes in both LS subtypes. Further prospective studies are needed to validate these findings and optimize surgical strategies.