Related Experiment Video
Updated: Sep 14, 2025
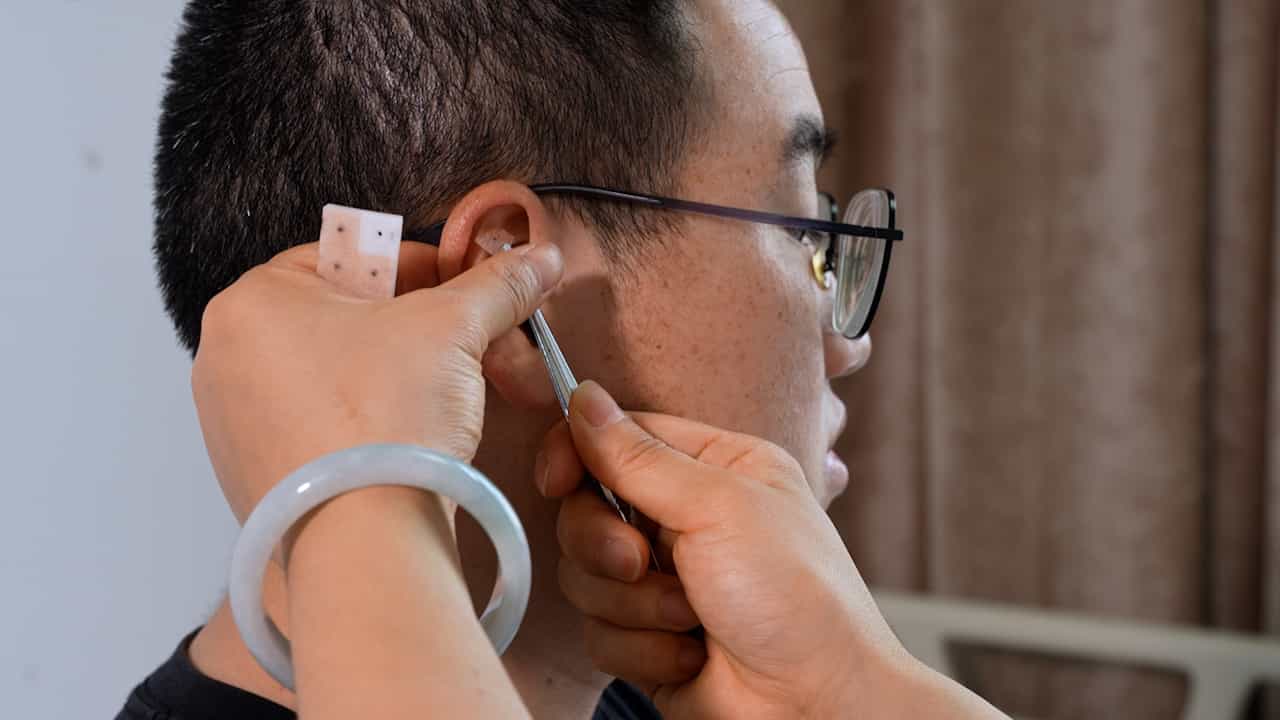
Author Spotlight: Efficacy of Auricular Pressure Bean Therapy in Reducing Wheezing Symptoms
Published on: May 10, 2024
Patient reported outcome measures require scale metrification and quantified precision: evidence from the assessment
Carolyn A Young1,2, Amina Chaouch3, Christopher J Mcdermott4
1Department of Neurology, Walton Centre NHS Foundation Trust, Liverpool, UK.

Abstract:
Introduction: Precision (how closely repeated measures match) and responsiveness (ability to detect change over time) are critical properties of patient reported outcome measures (PROMs). Smallest Detectable Difference (SDD) is a useful statistic regarding precision; Minimal Detectable Change (MDC) and Minimal Important Change (MIC) assess responsiveness. Methods: We examined measurement properties of Numeric Rating Scale for Breathlessness, ALSFRS-R respiratory subscale and Dyspnea-12, contributed by participants in the Trajectories of Outcome in Neurological Conditions-ALS study. Rasch analysis converts ordinal scale data to interval equivalents. Results: Data from 1120 people with ALS showed ALSFRS-R Respiratory is only valid as ordinal data. The NRS Breathlessness requires computation from a wider NRS set for Rasch analysis; its SDD is 3.2, MDC 2.59, MIC 2.39, with score range of 0-10. The Dyspnea-12 has SDD 7.0, MDC 6.14, MIC 4.5, with score range of 0-36. The %MDC, indicating smallest change detectable above measurement error as % of scale range, is superior for the Dyspnea-12 (17.1%) compared to the NRS Breathlessness (25.9%). Another advantage of Dyspnea-12 is transformation of raw ordinal to interval equivalent data using published conversion tables. Both NRS and Dyspnea-12 have disadvantages of MIC < MDC. Conclusions: Accurate measurement underpins optimal clinical decision making and high-quality research. Informed choice of PROMs reduces risk of misinterpreting clinical and research data. Patients want PROMs which they feel give an accurate account of their progression when participating in research and communicating with their clinical team. The Dyspnea-12 is preferrable for clinical and research use based on its psychometric properties.
More Related Videos
 04:24
Acupoint Application as a Traditional Chinese Medicine Treatment for Fatigue Associated with Chronic Obstructive Pulmonary Disease
Published on: September 5, 2025
 12:43
A Protocol for Comprehensive Assessment of Bulbar Dysfunction in Amyotrophic Lateral Sclerosis ALS
Published on: February 21, 2011
Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...