Related Experiment Video
Updated: Oct 3, 2026

Author Spotlight: Recent Advancements in Reoperative Foregut Surgery
Published on: September 22, 2023
Body mass index should be considered as an indicator for laparoscopic surgery or robot-assisted surgery selection in
Minghao Liu1,2, Chen Li2, Jing Yao2
1Medical School of Chinese People's Liberation Army, Beijing, China.

Background:
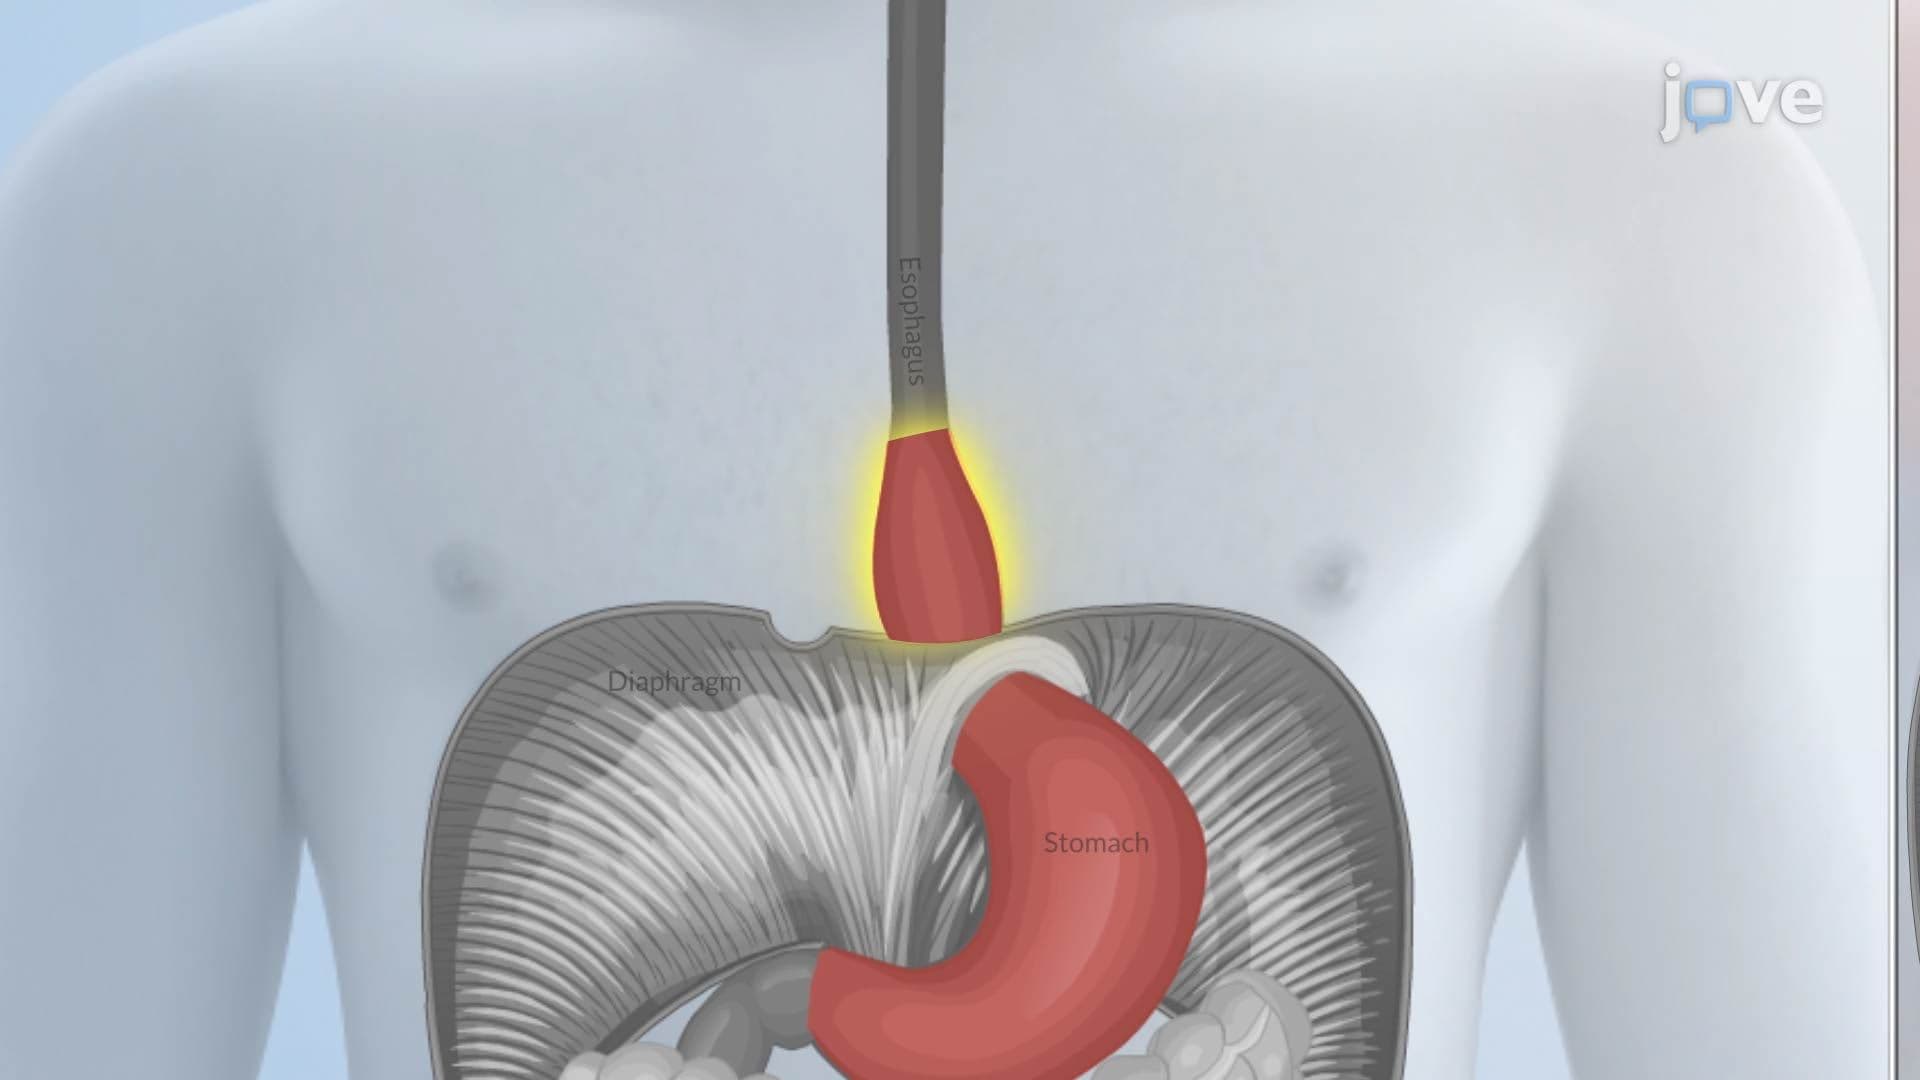
Hiatal hernia (HH), a prevalent clinical condition characterized by the protrusion of abdominal viscera into the thoracic cavity through the esophageal hiatus, remains a subject of ongoing debate regarding optimal surgical management strategies. This study aimed to analyze and compare the efficacy of robot-assisted versus laparoscopic repair of HH in patients with varying body mass index (BMI).
Methods:
We retrospectively analyzed the clinical data of patients with HH treated at the Chinese People's Liberation Army (PLA) General Hospital from December 2013 to December 2023. A total of 142 patients were included and divided into three groups based on their BMI values: normal group (18.5 to <24.0 kg/m2), overweight group (24 to <28.0 kg/m2) and obese group (BMI ≥28.0 kg/m2). Preoperative baseline data, perioperative data and postoperative symptom improvement were analyzed to compare the benefits of the two surgical methods across different BMI groups.
Results:
In the normal group, compared to the laparoscopic group, the robot-assisted group exhibited less intraoperative bleeding, shorter postoperative time to first flatus, longer operation time, and more hospitalization costs (20.0 vs. 35.0 mL; 2.0 vs. 3.0 days; 113.00 vs. 100.00 min; ¥52,529 vs. ¥38,387), the differences were statistically significant (P<0.05). No significant benefits were observed in terms of postoperative hospitalization time or pain score (P>0.05). In the overweight group, robot-assisted surgery was associated with significantly reduced intraoperative bleeding, shorter postoperative time to first flatus, shorter postoperative hospitalization time, lower postoperative pain scores, longer operation time and higher hospitalization costs (25.0 vs. 36.2 mL; 2.0 vs. 3.0 days; 4.0 vs. 5.0 days; 3.0 vs. 4.0 points; 115.00 vs. 104.00 min; ¥62,453 vs. ¥39,647), the difference was statistically significant (P<0.05). Postoperative reflux symptoms improved in both normal and overweight patients compared to their preoperative conditions, but no statistically significant difference was observed in the extent of improvement between the two groups (P>0.05). In the obese group, compared with laparoscopic surgery, robot-assisted surgery manifested significantly reduced intraoperative bleeding (22.0 vs. 37.0 mL), faster postoperative flatus time (2.0 vs. 3.0 days), shorter hospitalization duration (4.0 vs. 5.0 days), lower postoperative pain scores (3.0 vs. 4.0 points), and marked improvement in reflux symptoms, despite higher total hospitalization costs (¥62,916 vs. ¥40,407). Operative time was comparable between the two groups, with no statistically significant difference (120.00 vs. 110.50 min, P>0.05).
Conclusions:
Under the financial burden of the higher costs associated with robot-assisted surgery, choosing robot-assisted surgery can provide more benefits for patients with a higher BMI, therefore, we recommend that BMI should be considered as an indicator when selecting surgical methods for patients.