Related Experiment Video
Updated: Sep 14, 2025
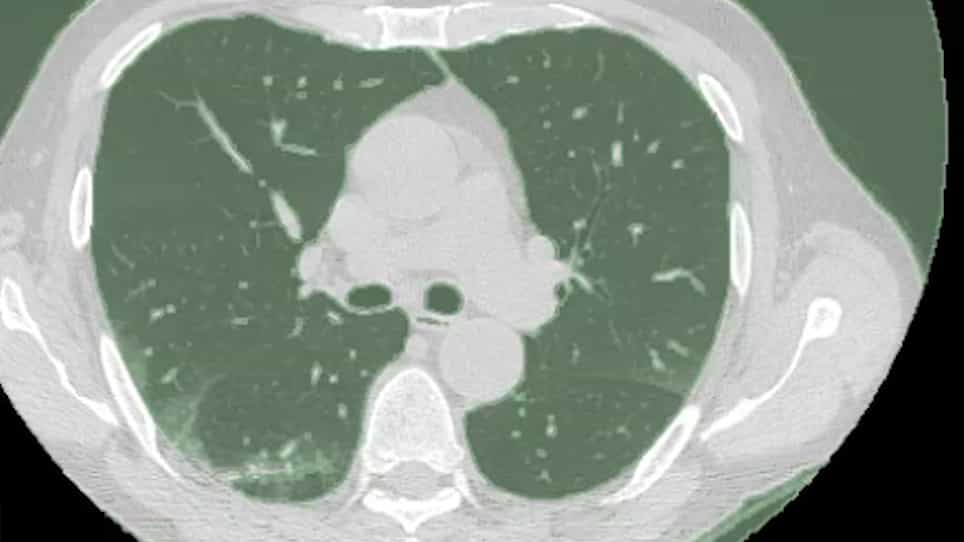

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Abnormal Chest X-Ray Findings of Patients With Confirmed Tuberculosis in Ghana
Augustina Badu-Peprah1,2, Yaa D Appiah3, Jimah Bashiru Babatunde4
1Department of Radiology, Kwame Nkrumah University of Science and Technology, Kumasi, GHA.

Abstract:
Background Tuberculosis (TB) remains a major global health issue despite being treatable and preventable. Early diagnosis and effective treatment are crucial for reducing TB transmission, in line with global control strategies. Chest X-rays, widely accessible and rapid, are key imaging tools for diagnosing TB. This retrospective study sought to assess chest X-ray findings of patients with confirmed tuberculosis in Ghana. Methods This study retrospectively analyzed chest X-ray findings to characterize lung lesions and assess tissue damage in 131 patients with bacteriologically confirmed TB. Lung lesions were categorized based on parenchymal changes, lesion extent, location, and pleural involvement. Results Reticulonodular infiltrates were observed in 66.4% (n=87) of patients, consolidation/ground-glass opacities in 58.8% (n=77), reticular infiltrates in 45.0% (n=59), and cavities in 42.0% (n=55). Pleural effusions were noted in 31.3% (n=41), predominantly unilateral (24.4%, n=32). Parenchymal anomalies primarily affected the apical/upper lung zones, mostly on the left (70.2%, n=92). Both middle-zone (48.1%, n=63) and lower-zone (49.6%, n=65) abnormalities predominantly affected the right lung. The extent of lung involvement varied: 23.6% (n=31) had small (one zone), 11.4% (n=15) medium (two zones), and 58.0% (n=76) large (more than two zones) involvement. Conclusion These findings highlight the significant lung damage caused by TB and underscore the importance of imaging in early detection and management.
More Related Videos

Related Concept Videos
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:27
Pneumothorax-II
Clinical Manifestations: