Related Experiment Video
Updated: Sep 14, 2025

Prone Lateral Minimally Invasive Retropleural Corpectomy Using a Rotatable Radiolucent Jackson Table
Published on: July 3, 2025
Prone Lateral Minimally Invasive Retropleural Corpectomy Using a Rotatable Radiolucent Jackson Table
Hsuan-Lun Yang1, Yung-Hsueh Hu1, Ming-Kai Hsieh1
1Department of Orthopaedic Surgery, Spine Section, Bone and Joint Research Center, Chang Gung Memorial Hospital and Chang Gung University College of Medicine.

Abstract:
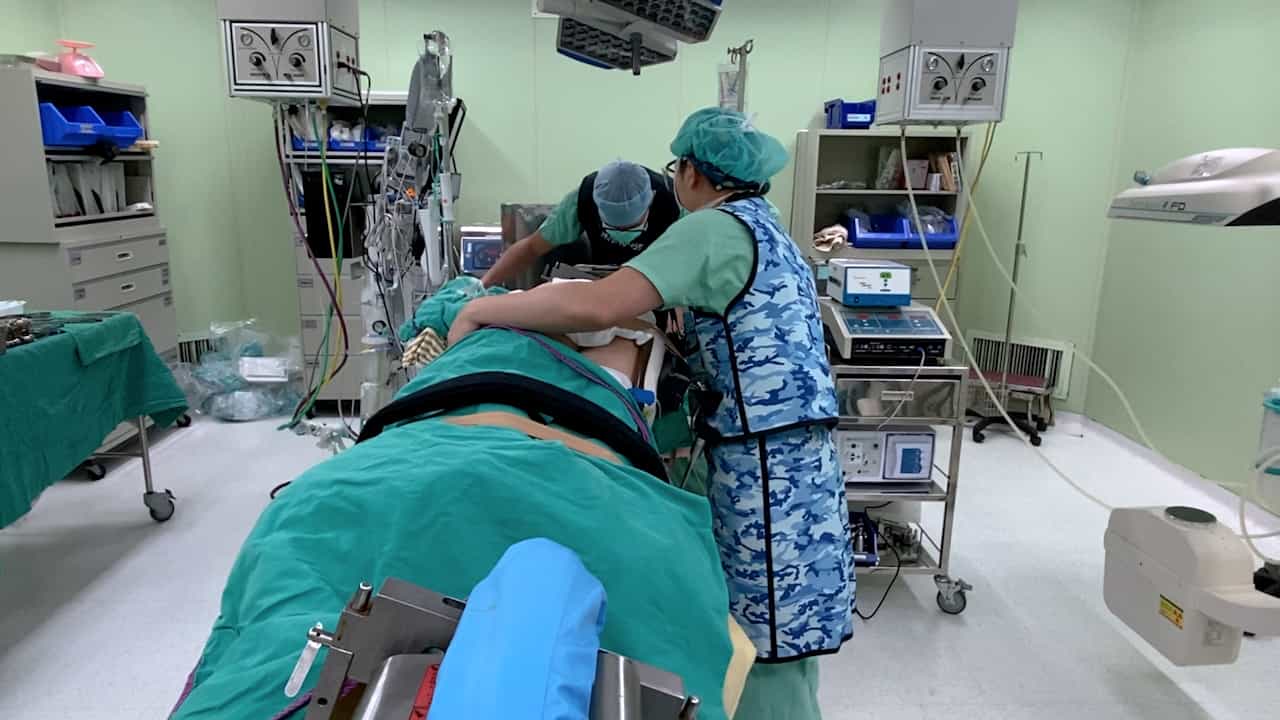
Prone lateral single-position spinal surgery allows simultaneous manipulation of the anterior and posterior columns, avoiding re-draping and improving lordotic alignment. A minimally invasive retropleural approach avoids potential complications associated with one-lung ventilation and diaphragmatic takedown. Using a rotatable radiolucent Jackson table, we perform minimally invasive retropleural corpectomy for lesions from T7 to L1. After securing the patient in the prone position with tape and contralateral positioners, the table is rotated 30° away from the surgical side. True anteroposterior (AP) and lateral views are obtained using intraoperative C-arm fluoroscopy. A 5-6 cm incision is made between the anterior and posterior borders of the targeted vertebra. The nearest rib beneath the incision is resected for approximately 8-9 cm, facilitating access. Careful dissection of the retropleural space is performed without penetrating the parietal pleura, extending along the ventral side of the rib to the rib head of the targeted vertebra. The rib head is excised, and the segmental vessel is ligated. Adjacent disc levels and the anterior vertebral body are exposed. The above and below discs are prepared, and corpectomy is performed using appropriate instruments. The pedicle can be removed to expose the posterior vertebral wall for direct decompression of the ventral dura if needed. Simultaneous percutaneous pedicle screw insertion can be performed during the lateral approach or after rotating the table back to the horizontal position if an osteotomy is needed. An air leak test is conducted before wound closure; a chest tube can be inserted if the pleura is violated. This prone lateral minimally invasive retropleural corpectomy technique allows simultaneous lateral and posterior approaches without re-draping. It is particularly useful for minimally invasive approaches to anterior lesions without sacrificing the posterior ligamentous complex.