Related Experiment Video
Updated: Sep 14, 2025
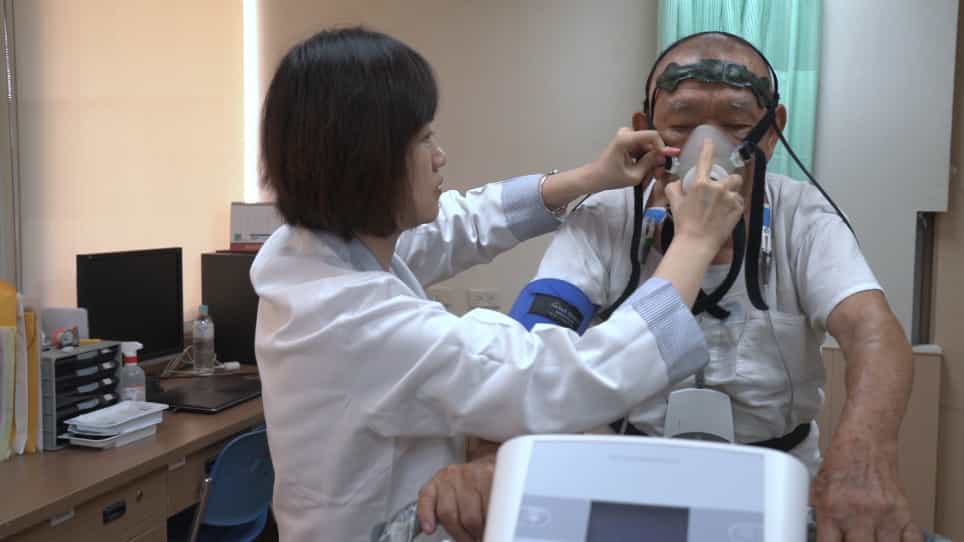

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Effect of moderate altitude and nocturnal oxygen therapy on cerebrovascular function in patients with COPD: A
Dominic Gilliand1, Tsogyal D Latshang1, Sayaka S Aeschbacher1
1Department of Respiratory Medicine, University Hospital of Zurich, Zurich, Switzerland.

Abstract:
We investigated whether nocturnal oxygen therapy improves next-day cerebrovascular function in lowlanders with chronic obstructive pulmonary disease (COPD) staying at moderate altitude. This randomized, placebo-controlled single-blind crossover trial was performed in moderate-to-severe COPD patients [forced expiratory volume in 1 s (FEV1)/forced vital capacity (FVC) <0.7; FEV1 30%-80% of predicted], living at <800 m a.s.l. and arterial oxygen saturation ( ) measured with pulse oximetry ≥92%. Patients underwent assessments at 490 m and during two separate sojourns of 2 days at 2048 m, receiving either 3 L min-1 nocturnal oxygen therapy or placebo in a randomized crossover design. At both altitudes, , cerebral tissue oxygenation (CTO, measured by near-infrared spectroscopy), mean arterial blood pressure (MAP, measured by finger plethysmography) and middle cerebral artery systolic peak blood flow velocity (sMCAv, measured by transcranial Doppler ultrasound) were assessed while patients were quietly breathing with fraction of inspired O2 ( ) 0.21, with 1.0, voluntarily hyperventilating, voluntarily hyperventilating with 1.0, and during a head-up tilt. Overall, 18 patients (8 women) aged (mean ± SD) 65 ± 5 years, with FEV1 54.7% ± 13.9% predicted were analysed. At 2048 m under 0.21, patients became hypoxaemic ( 90.3% ± 1.6%), while MAP, CTO and sMCAv remained unchanged compared with 490 m. All ventilatory manoeuvres at 2048 m induced greater increases in compared with 490 m, while changes in MAP, CTO and sMCAv were similar. Head-up tilt induced a similar decrease in blood pressure, whereas sMCAv changed less in response to systemic hypotension (ΔsMCAv/ΔMAP 0.9 ± 1.3 vs. 2.3 ± 1.7 cm s-1 mmHg-1) at 2048 m. No effect of nocturnal oxygen therapy was observed during any manoeuvres. This randomized clinical trial in moderate-to-severe COPD patients ascending to 2048 m showed that moderate hypoxaemia does not translate to daytime cerebral hypoxia or cerebrovascular autoregulatory impairments while at rest or during ventilatory or orthostatic challenges.
More Related Videos


Related Concept Videos
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue,...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:15
Chronopharmacokinetics: Circadian Rhythms and Influence on Drug Response
The time of drug administration is an important factor to consider, as it can influence the toxic dose of a drug. For example, a study conducted by Prins et al. in 1997 examined the effects of the timing of...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...