Related Experiment Video
Updated: Sep 13, 2025
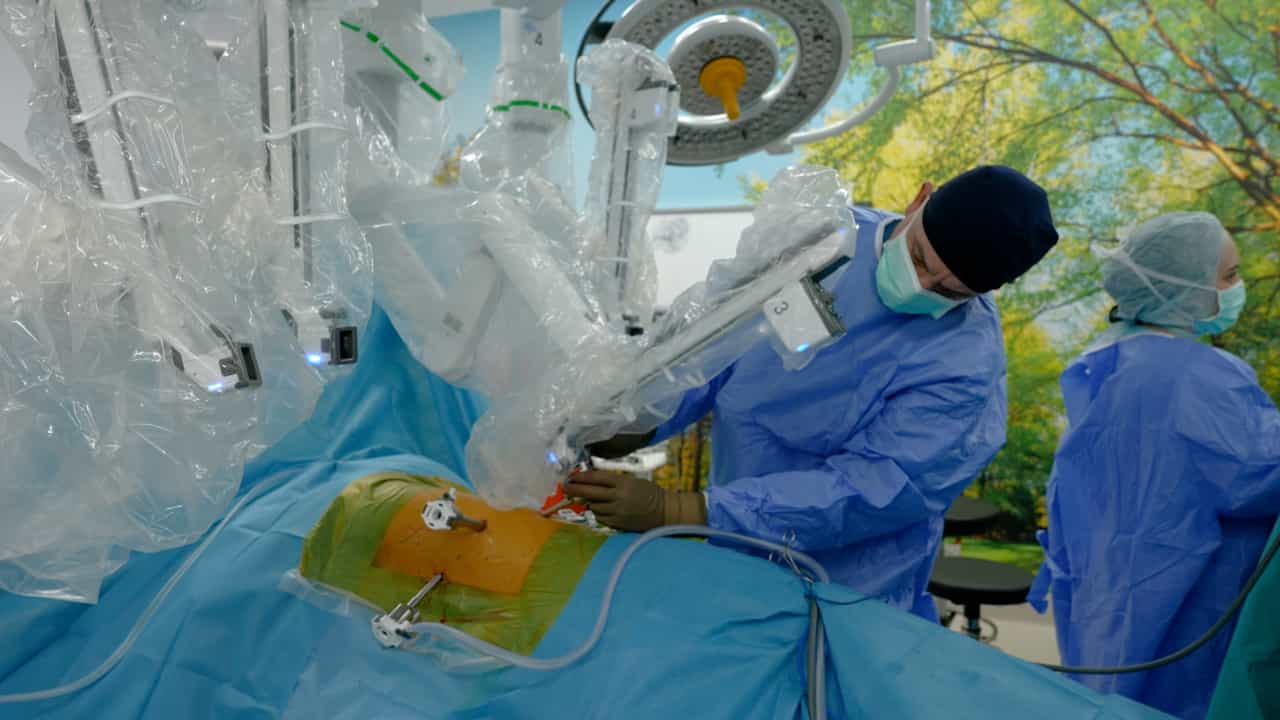
Subcostal Specimen Removal in Completely Portal Robotic Lobectomy
Published on: April 19, 2024
Subcutaneous and mediastinal emphysema after lobectomy: Two case reports with different courses
Yuki Shindo1, Hiroya Ishihara2, Takuro Morita3
1Department of Thoracic Surgery, Takatsuki Red Cross Hospital, Takatsuki, Japan; Department of Thoracic and Cardiovascular Surgery, Osaka Medical and Pharmaceutical University, Takatsuki, Japan.

Introduction:
Subcutaneous and mediastinal emphysema after lobectomy is uncommon and is typically caused by minor air leakage from the residual lung; however, the development of a contralateral pneumothorax is particularly rare, and if missed, it can be fatal.
Presentation Of Cases:
Two cases of subcutaneous and mediastinal emphysema occurring after a lobectomy in a 77-year-old man and a 78-year-old man are reported here. The former received conservative treatment, while the latter he developed a pneumothorax on the side contralateral to the surgical site after readmission. Chest tube drainage was then performed.
Discussion:
The occurrence of subcutaneous and mediastinal emphysema after lobectomy is not uncommon. Conservative management is often sufficient if no pneumothorax is present, as in Case 1. However, in Case 2, pneumothorax occurred on the contralateral side due to a minor air leakage, which is an unusual complication. Generally, a pneumothorax of the residual lung on the surgical side occurs earlier than a pneumothorax on the contralateral lung. The earlier onset on the contralateral side in Case 2 suggests that the pressure threshold for rupturing the contralateral mediastinal pleura and/or alveoli may have been lower than that for collapsing the residual lung on the operative side. We recommend that pulmonologists should also monitor the contralateral side and that follow-up radiographic examinations should be performed a few hours later.
Conclusion:
Pulmonologists should monitor the side contralateral to the surgical site, even if the emphysema is caused by a postoperative minor air leakage.

Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care