Related Experiment Video
Updated: Sep 13, 2025
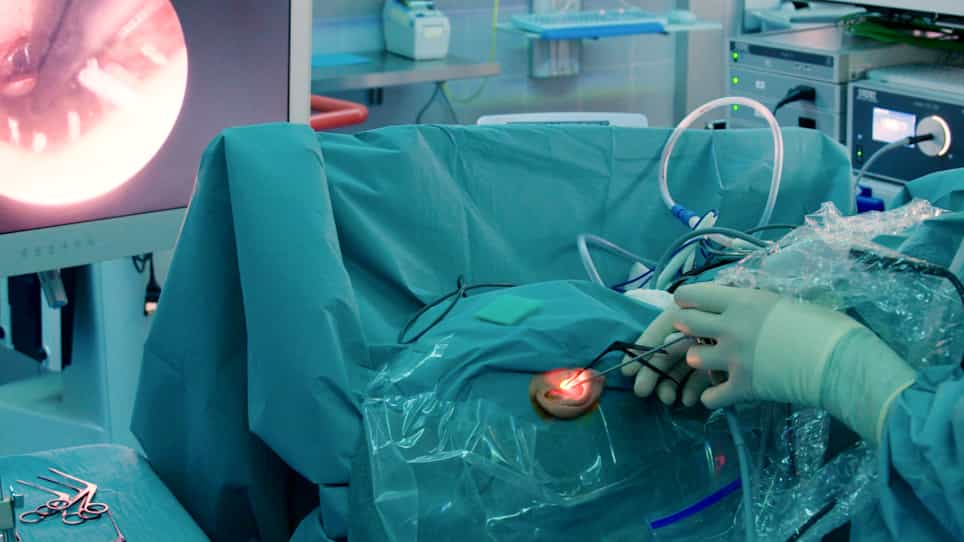
Endoscopic Cholesteatoma Surgery
Published on: January 19, 2022
Primary external auditory canal cholesteatoma: Clinical characteristics and role of endoscopic ear surgery
Yuvatiya Plodpai1, Pittayapon Pitathawatchai1, Pattarawadee Prayuenyong1
1Department of Otolaryngology Head and Neck Surgery, Faculty of Medicine, Prince of Songkla University, Hatyai, Songkhla 90110, Thailand.

Purpose:
Primary external auditory canal cholesteatomas (PEACCs) are uncommon, and the role of endoscopy in managing the lesion has not yet been clarified. We aimed to investigate the clinical characteristics of PEACC and explore the feasibility of endoscopy for its treatment.
Material And Methods:
A retrospective study in patients who diagnosed with PEACC from January 2012 to January 2024 was conducted. The presenting features, disease extension according to Naim's classification, and treatment option used were assessed. The clinical characteristics were compared between the conservative successful group and the surgical group.
Results:
A total of 72 patients who completed the treatment protocols were enrolled. Per the classification by Naim et al., PEACC was categorized as stage II, III, and IV in 7, 42, and 23 cases, respectively. Successful nonoperative treatment using the transcanal endoscopic approach was achieved in 46 patients without tympanic perforation (p = 0.035), scutum erosion (p < 0.001), ossicular involvement (p = 0.02), erosion of the vertical segment of the facial canal (p = 0.018), or mastoid involvement (p = 0.046), with maintenance of dry ear for 2 months (p < 0.001). Endoscopy-assisted and exclusive endoscopic surgery were performed in nine and ten patients, respectively. Canal wall-down mastoidectomy with obliteration was performed in seven patients with advanced stage IV disease. Complications were not reported in either group.
Conclusion:
Endoscopy is useful for PEACC management even in advanced stages. However, the approach varies according to the lesion extent. Successful nonoperative management feasible in patients without tympanic membrane perforation, scutum erosion, facial canal erosion, ossicular or mastoid involvement and in those with ear drainage for <2 months.