Related Experiment Video
Updated: Sep 13, 2025
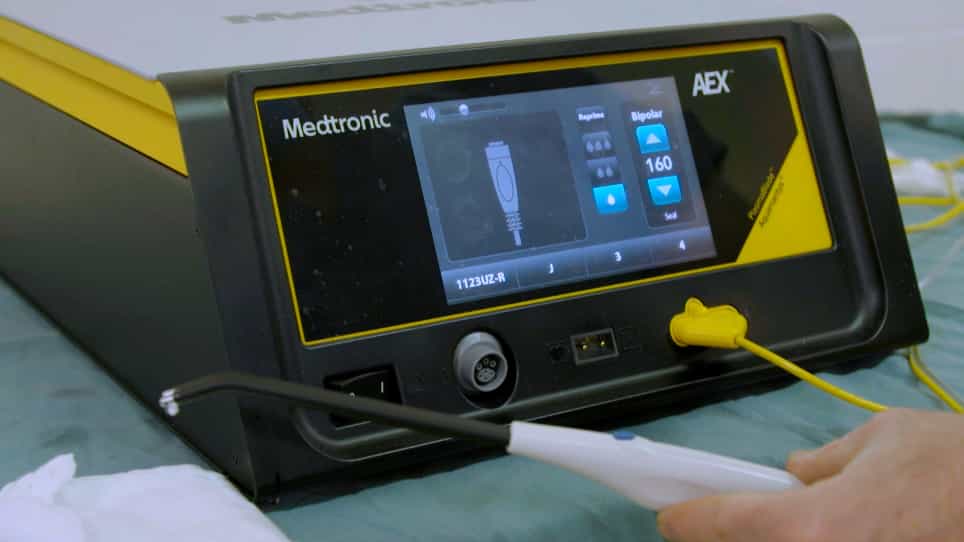

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Report Cards Are Out: Nine Years of Nonoperative Management for Blunt Abdominal Solid Organ Trauma
Muhammad Haris Khurshid1, Francisco Castillo Diaz1, Omar Hejazi1
1Division of Trauma, Critical Care, Burns, and Emergency Surgery, Department of Surgery, College of Medicine, University of Arizona, Tucson, Arizona.

Introduction:
There has been a dramatic shift toward nonoperative management (NOM) of blunt abdominal solid organ injuries (ASOIs) with angioembolization (AE). However, there is a lack of evidence assessing temporal trends in AE use, timing of intervention, and how these trends relate to NOM failure and patient outcomes over time. The aim of this study was to assess the trends in time to AE, its association with failure of NOM, and outcomes of these patients across the United States.
Materials And Methods:
We performed a retrospective analysis of the American College of Surgeons Trauma Quality Improvement Program database over 9 y, ending in 2021. We included adult patients (age ≥ 18 y) with blunt ASOI (spleen, liver, and kidney) who underwent AE within 4 h of hospital arrival. Patients who underwent operative intervention before AE were excluded. The primary outcome measured was the failure of NOM. Secondary outcomes included major complications, 24-h mortality, and in-hospital mortality. Multivariable regression analyses were performed to identify the independent effect of every hour delay in time to AE on outcomes.
Results:
A total of 2203 patients with blunt ASOI who were managed nonoperatively with AE were identified. The mean age was 45, and 68% were male. On arrival, the mean systolic blood pressure was 105, and the median Glasgow coma scale was 15. The median Injury Severity Score and abdominal Abbreviated Injury Scale were 25 and 3, respectively. The median 4-h packed red blood cell, fresh frozen plasma, and platelet requirements were 2, 1, and 0, respectively. Overall, spleen was the most common angioembolized abdominal organ (57.3%), followed by the liver (28.9%) and kidney (13.8%). The median time to AE was 156 [114-195] min. Only 8% of patients underwent AE within the first 60 min of arrival. A significantly decreasing trend over the study period was observed in time to AE (2013:180 min versus 2021:105 min, P < 0.001). Among the study population, 19.7% experienced NOM failure, with a median [interquartile range] time to surgery of 5 [3-11] h. Over the years, there was a significant reduction in NOM failure rates (2013:26.2% versus 2021:8.7%, P < 0.001), major complications (2013:57.5% versus 2021:25.1%, P < 0.001), 24-h mortality (2013:6.8% versus 2021:1.3%, P = 0.006), and in-hospital mortality (2013:16.4% versus 2021:8.1%, P = 0.015). On multivariable regression analyses, every hour delay in time to AE was associated with higher odds of NOM failure (adjusted odds ratio [aOR]: 1.13, 95% confidence interval [CI] [1.02-1.16], P = 0.006), major complications (aOR: 1.12, 95% CI [1.02-1.23], P = 0.019), 24-h mortality (aOR: 1.19, 95% CI [1.09-1.52], P = 0.014), and in-hospital mortality (aOR: 1.17, 95% CI [1.01-1.35], P = 0.041).
Conclusions:
NOM of patients with blunt ASOI has improved over the past 9 y, with failure rates decreasing by approximately 30%, indicating enhanced effectiveness of AE over time. Timely AE was independently associated with lower complication rates and reduced 24-h and in-hospital mortality, likely due to earlier hemorrhage control and mitigation of secondary physiologic decline. Efforts should focus on improving timely access to AE through standardized trauma protocols, early identification of candidates, and streamlined interventional radiology activation.
More Related Videos
 13:57
Laparoscopic Anatomical Liver Segment VII Resection with Liver Parenchymal Transection Following a Priority Approach
Published on: May 23, 2025
 20:33
A Case Series of Successful Abdominal Closure Utilizing a Novel Technique Combining a Mechanical Closure System with a Biologic Xenograft that Accelerates Wound Healing
Published on: July 4, 2019
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:26
Aneurysm III: Interprofessional Care
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:22
Aneurysm IV: Nursing Management