Related Experiment Video
Updated: Sep 13, 2025
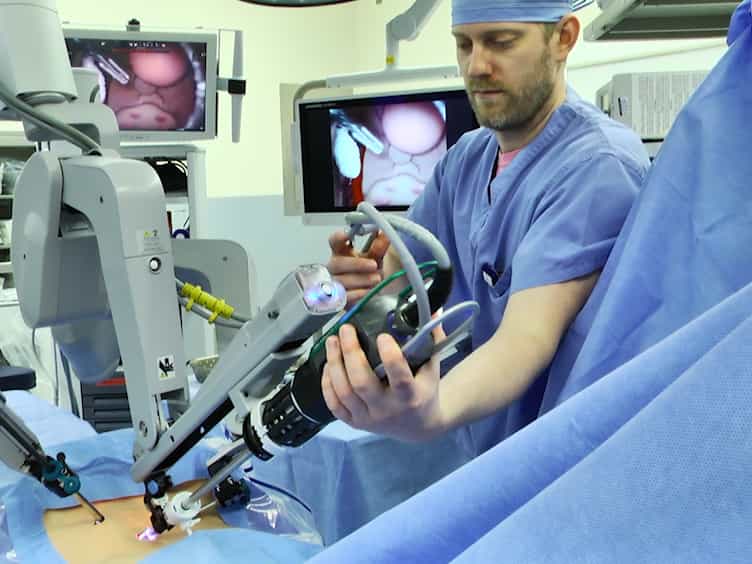

Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
Assessing the Impact of Resident Participation in Emergency General Surgery in the Older Adult Population
Yasmin Arda1, May Abiad1, Wardah Rafaqat1
1Division of Trauma, Emergency Surgery, and Surgical Critical Care, Department of Surgery, Massachusetts General Hospital and Harvard Medical School, Boston, Massachusetts.

Objective:
Although data concerning resident involvement in emergency general surgery (EGS) procedures is abundant, its impact on outcomes in the vulnerable older adult population has not been explored. This study aimed to assess the impact of resident involvement on postoperative outcomes in older adult patients undergoing EGS.
Design:
Propensity-score matched cohort study.
Setting:
The 2007-2012 American College of Surgeons National Surgical Quality Improvement Program (ACS-NSQIP) database.
Participants:
Patients aged ≥65 years who underwent one of eight EGS procedures were included. Patients were stratified based on resident participation (RES vs. NO-RES). After propensity-score matching, each group included 2,796 patients with comparable baseline characteristics.
Results:
Among 24,452 patients identified, 14,381 (58.8%) underwent procedures with resident involvement. Patients in the RES group were more likely to be Black (11.3% vs. 6.1%) and have pre-existing comorbidities, such as ventilator dependence (7.7% vs. 4.0%), and were less likely to be admitted from home (84.3% vs. 88.4%) (all p<0.001). After matching, 30-day mortality was not different between the two groups. However, patients in the RES group demonstrated higher 30-day morbidity (38.8% vs. 36.0%, p = 0.031), likely driven by a greater incidence of superficial surgical site infection (5.6% vs. 3.9%, p = 0.003) and unplanned reoperation (11.0% vs. 7.4%, p<0.001). Operative time was significantly longer in the RES group (p<0.001).
Conclusions:
Participation of residents in EGS procedures is associated with increased operative time, rate of surgical site infection, and unplanned reoperation. However, resident involvement had no effect on patient mortality. Efforts to improve surgical education while not compromising patient safety are needed.


