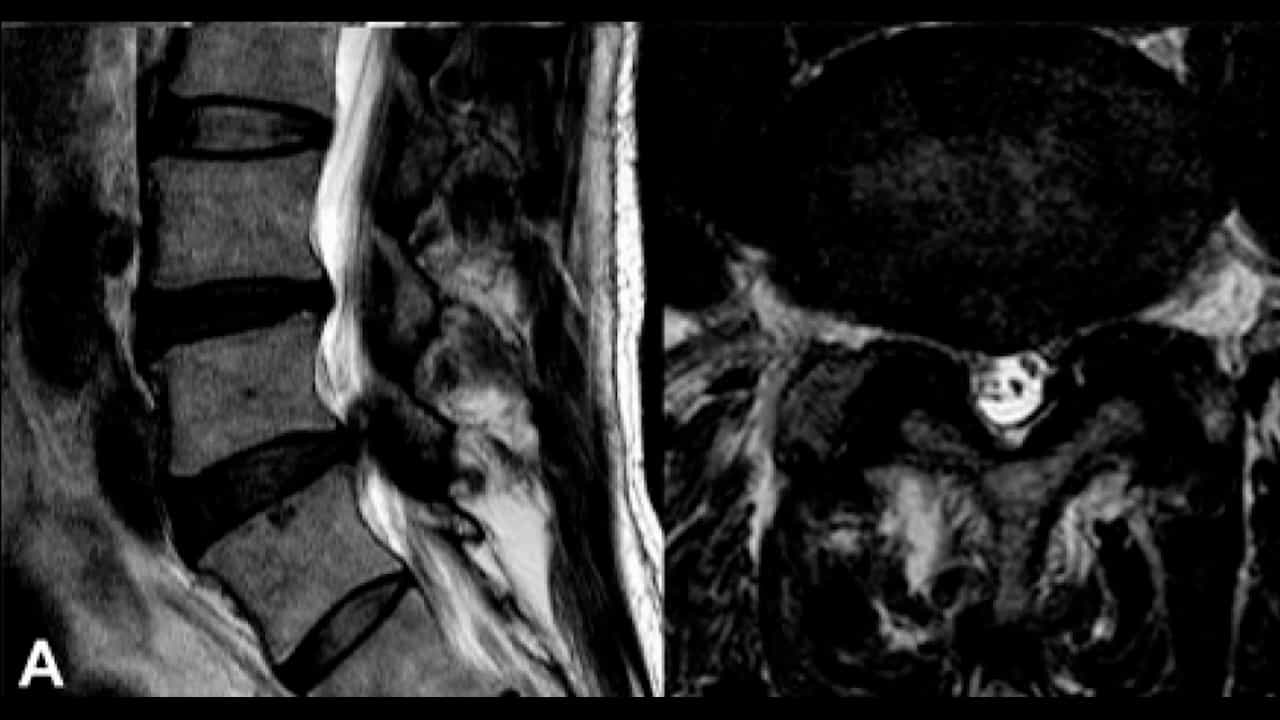
Related Experiment Video
Updated: Sep 13, 2025
Author Spotlight: Scope of LE-ULBD as a Safe, Effective, and Minimally Invasive Approach to Treat Lumbar Spinal Stenosis
Published on: February 9, 2024
Machine learning prediction of extended length of stay following endoscopic decompression for lumbar spinal stenosis:
Fuqiang Tan1,2, Xiaobin Li1,2, Chaoyang Qu1,2
1Department of Orthopaedics, People's Hospital of Chongqing Hechuan, Chongqing, China.

Objective:
The aims of this study were to develop and validate interpretable ML models for extended length of stay (eLOS) prediction following endoscopic lumbar spinal stenosis (LSS) decompression, and identify modifiable risk factors influencing healthcare costs and recovery.
Methods:
A prospective-retrospective cohort of 350 patients (2019-2025) undergoing single-level endoscopic decompression was analyzed. The eLOS was defined as >9 days via classification and regression tree (CART) analysis. Predictors included demographics (age, BMI), comorbidities (osteoporosis, hypertension), surgical parameters, and hospitalization costs. Seven ML models (XGBoost, Lasso Regression, CNN, etc.) were trained using stratified 70:30 splits, SMOTE balancing, and Bayesian hyperparameter tuning. Model performance was evaluated via AUC-ROC, F1-score, and SHAP interpretability.
Results:
The eLOS group (n = 135) exhibited higher age (56.3 vs. 48.6 years, p < 0.001), osteoporosis (23% vs. 3.7%, p < 0.001), and hypertension (33.3% vs. 14.0%, p < 0.001). Gradient Boosting Machines (AUC = 0.96), XGBoost (AUC = 0.99), and Lasso Regression (AUC = 1.00) outperformed other models, identifying L4/L5 involvement, heart rate, age, osteoporosis, and hypertension as top predictors. Post-cross-validation, CNN (Accuracy = 0.75, AUC = 0.89) and XGB (Accuracy = 0.69, AUC = 0.85) demonstrated robustness. eLOS patients incurred 13% higher costs (p = 0.02).
Conclusion:
This study establishes the first ML-driven framework for eLOS prediction in endoscopic LSS surgery, emphasizing age-related comorbidities over procedural factors. The integration of economic and clinical data enables actionable risk mitigation, supporting value-based care initiatives. Future multicenter studies should validate these models across diverse healthcare systems.