Related Experiment Video
Updated: Sep 13, 2025


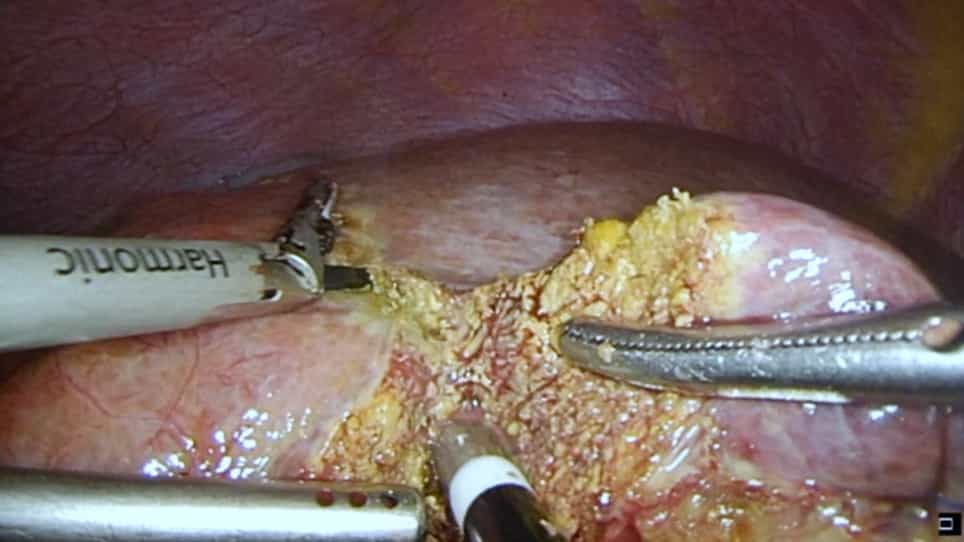
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
Topical hemostatic agents in endoscopy: European Society of Gastrointestinal Endoscopy (ESGE) Technical and
Ian M Gralnek1,2, Pradeep Bhandari3,4, Asma Alkandari5
1Ellen and Pinchas Mamber Institute of Gastroenterology and Hepatology, Emek Medical Center, Afula, Israel.

Background:
Gastrointestinal (GI) endoscopy has evolved from a diagnostic tool into a therapeutic modality, leading to a higher incidence of bleeding complications during and after procedures. To address this issue, various hemostatic agents have been developed, including injectable, mechanical, thermal, and topical products. Topical hemostatic agents, available in powder or gel forms, can be used as standalone treatments or as adjuncts to traditional hemostatic therapies to control or prevent bleeding.
Methods:
This Technical and Technology Review examines the commercially available topical hemostatic agents used in endoscopy, specifically Purastat, TC-325 Hemospray, EndoClot PHS, Nexpowder, Ankaferd Blood Stopper, and CG GEL. A systematic literature review was conducted up to January 2025, focusing on randomized controlled trials (RCTs), meta-analyses, and observational studies. Each product was assessed for its composition, mechanism of action, regulatory status, mode of use, efficacy, safety, and financial considerations.
Results:
Purastat showed 94% efficacy in acute GI bleeding, reducing delayed bleeding to 4.3% in endoscopic submucosal dissection (ESD) and endoscopic mucosal resection cases, with significantly lower thermal device usage. TC-325 Hemospray achieved 85%–98.5% primary hemostasis in upper and lower GI bleeding, with pooled hemostasis rates of 93.1% and rebleeding rates of 8.9%. It was also effective in malignancy-related bleeding, with hemostasis success up to 100%. EndoClot PHS demonstrated 76%–100% hemostasis efficacy, comparable with TC-325, with rebleeding rates of 24%–25%. It showed prophylactic potential post-ESD, with rebleeding rates of 7.3%–9.1%. Nexpowder achieved 94% hemostasis in refractory upper GI bleeds and reduced rebleeding in lower GI bleeds to 5.5% at 28 days. Ankaferd Blood Stopper demonstrated 73%–100% hemostasis across various GI bleeding sources, including peptic ulcers and malignancies, though further data on rebleeding are needed.
Conclusion:
Topical hemostatic agents offer effective options for managing GI bleeding. Products like Purastat, TC-325 Hemospray, EndoClot PHS, Nexpowder, Ankaferd Blood Stopper, and CG GEL have shown promising results in achieving hemostasis; however, further RCTs and cost-effectiveness analyses are needed to better establish their roles in endoscopic practice.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:29
Venous Thrombosis III: Interprofessional Care
 01:18
Anticoagulant Drugs: Vitamin K Antagonists and Direct Oral Anticoagulants
Warfarin, a prominent vitamin K antagonist family member, exerts its effect by inhibiting the enzyme VKORC1 (vitamin K epoxide reductase complex 1). By hindering this enzyme, warfarin...
 01:30
Venous Thrombosis IV: Nursing Management
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized,...