Ultrasound and 99mTc-DMSA Scan Versus Voiding Cystourethrography in Diagnosis of Vesicoureteral Reflux in Children
Related Experiment Video
Updated: Sep 13, 2025

Ultrasonography of the Adult Male Urinary Tract for Urinary Functional Testing
Published on: August 14, 2019
Elham Zarei1, Sepideh Hekmat2, Jilla Armandeh3
1Department of Radiology, Ali Asghar Children Hospital, School of Medicine, Iran University of Medical Sciences, Tehran, Iran.

Insights
Early detection of vesicoureteral reflux (VUR) in children is vital. Combining ultrasound and 99mTc-DMSA scans effectively rules out high-grade VUR, potentially avoiding unnecessary voiding cystourethrography (VCUG).
Area of Science:
- Pediatric Nephrology
- Diagnostic Imaging
- Urology
Background:
- Early detection of vesicoureteral reflux (VUR) is critical to prevent kidney damage and recurrent urinary tract infections (UTIs).
- Noninvasive imaging modalities like ultrasound (US) and 99mTc-DMSA scans offer safer alternatives to voiding cystourethrography (VCUG) for VUR diagnosis in children.
- This study evaluated the diagnostic efficacy of US and 99mTc-DMSA scans compared to VCUG in pediatric UTI patients.
Purpose of the Study:
- To assess the accuracy of ultrasound (US) and 99mTc-DMSA scan in detecting VUR in children with UTI.
- To compare the performance of US and 99mTc-DMSA scan against the gold standard, voiding cystourethrography (VCUG).
- To determine if combined imaging can reliably exclude high-grade VUR, potentially reducing the need for VCUG.
Main Methods:
- An observational study included 540 hospitalized children diagnosed with UTI.
- All patients underwent US and VCUG; 99mTc-DMSA scans were performed on a subset.
- Diagnostic performance metrics including sensitivity, specificity, and predictive values were calculated.
Main Results:
- VCUG identified VUR in 143 children, with 90 cases being high-grade (III-V).
- Ultrasound showed 67.8% sensitivity and 58.94% specificity for VUR detection; 99mTc-DMSA scan had 59.42% sensitivity and lower specificity.
- Combined US and 99mTc-DMSA scans demonstrated high sensitivity (92%) and negative predictive value (93.20%) for high-grade VUR.
Conclusions:
- Neither US nor 99mTc-DMSA scan alone is fully reliable for detecting all VUR grades.
- The combination of US and 99mTc-DMSA scans effectively excludes high-grade VUR.
- Normal results from both US and 99mTc-DMSA scans may obviate the need for VCUG, reducing radiation exposure and improving diagnostic efficiency.
Background:
Early detection of vesicoureteral reflux (VUR) is crucial to prevent potential complications such as recurrent urinary tract infections and kidney damage. Noninvasive diagnostic alternatives to voiding cystourethrography (VCUG), such as ultrasound (US) and 99mTc-DMSA scan, offer effective and safe methods for identifying VUR without exposing children to ionizing radiation. This investigation aimed to evaluate the efficacy of US and 99mTc-DMSA scan in detecting VUR compared with VCUG among children with urinary tract infection (UTI).
Methods:
In this observational study, we included 540 hospitalized children with UTI in Aliasghar Children`s Hospital between April 2017 and May 2019. US and VCUG were performed on all patients, with 99mTc-DMSA administered to some to detect VUR. Sensitivity, specificity, positive and negative predictive values, overall accuracy, and kappa agreement were calculated to evaluate ultrasound efficacy in predicting VUR based on VCUG-confirmed existence or nonexistence of VUR.
Results:
Out of 540 patients, VCUG identified VUR in 143 cases, with 90 (63%) classified as grades III to V. US results were abnormal in 97 of the 143 patients (67.8%) confirmed to have VUR via VCUG, while the 99mTc-DMSA scan showed abnormalities in 41 out of 69 (59%) cases detected by VCUG. The sensitivity and negative predictive value (NPV) of the 99mTc-DMSA scan for diagnosing VUR were recorded at 59.42% and 46.59%, respectively. For ultrasound, the overall accuracy was 61.30%, with sensitivity at 67.83%, specificity at 58.94%, NPV at 37.31%, and positive predictive value (PPV) at 83.57%. In children with high-grade VUR (grades III-V) as determined by VCUG, the sensitivity, specificity, and NPV for ultrasound were found to be 80%, 58.2%, and 93.60%, respectively. However, when both US and 99mTc-DMSA scan results were utilized for detecting high-grade VUR, the sensitivity, specificity, and NPV were calculated to be 92%, 42.30%, and 93.20%, respectively.
Conclusion:
While both US and the 99mTcDMSA scan are not fully reliable in detecting all grades of VUR individually, integration of US and ^99mTc-DMSA scan demonstrates reliable sensitivity and NPV for effectively excluding high-grade VUR. These findings suggest that in children with normal results from both US and ^99mTc-DMSA scans, there may be no need for VCUG. This approach could significantly reduce unnecessary VCUG procedures, minimizing patient exposure to radiation and enhancing overall diagnostic efficiency in pediatric care.
Related Concept Videos
 01:22
Imaging Studies VI: Voiding Cystourethrography and Cystography
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:24
Imaging Studies II: Ultrasonography
 01:27
Imaging Studies IV: Magnetic Resonance Imaging
 01:27
Imaging Studies III: Computed Tomography
 01:19
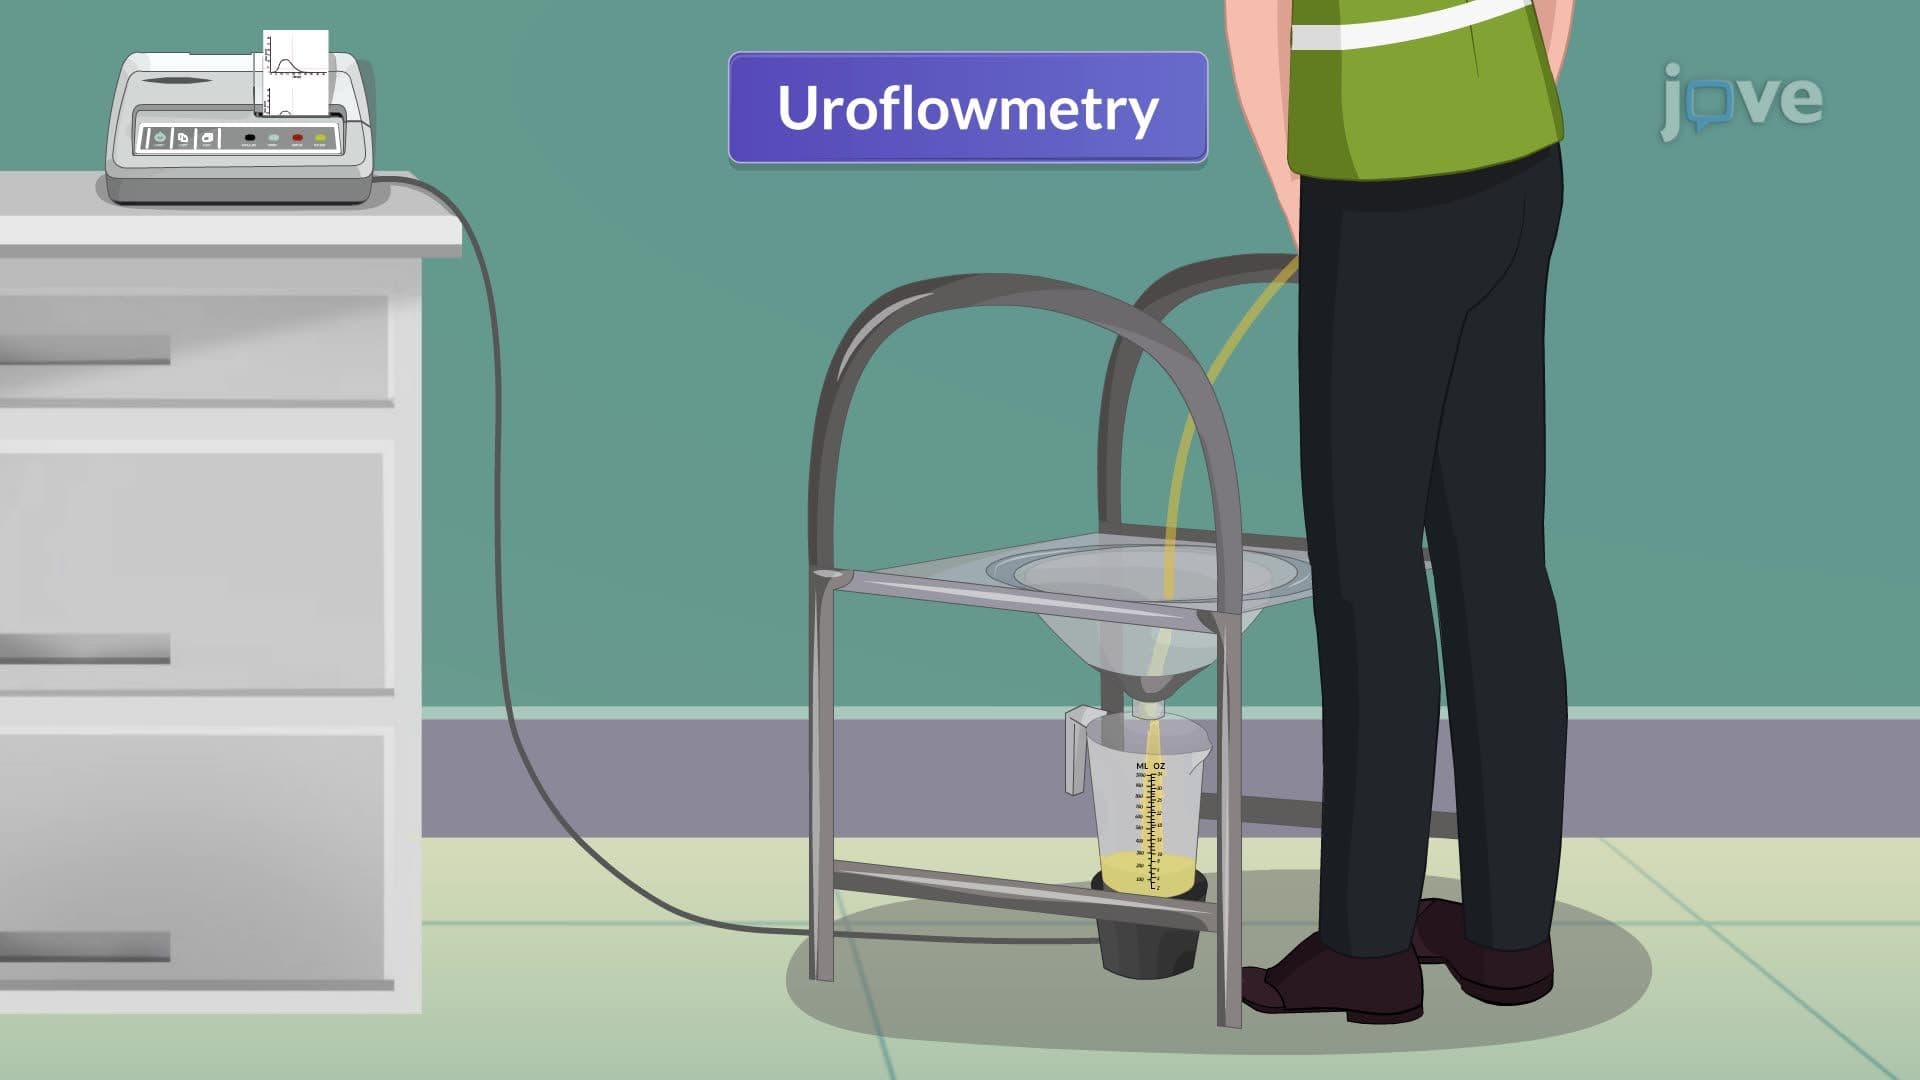
Urodynamic Studies: Uroflowmetry