Related Experiment Video
Updated: May 7, 2026


Characterization of Recombination Effects in a Liquid Ionization Chamber Used for the Dosimetry of a Radiosurgical Accelerator
Published on: May 9, 2014
Patient Size Estimation Methods for CMS Size-Adjusted Dose Reporting: Variability, Challenges, and Recommendations
Gary Ge1, Charles M Weaver1, Alexander Alsalihi1
1Division of Diagnostic & Nuclear Medical Physics, Department of Radiology, University of Kentucky College of Medicine, Lexington, Kentucky.

Objective:
The new CMS1074v3 measure assesses CT size-adjusted dose (SAD) and image quality as part of a reimbursement-linked quality measure. However, a key calculation, patient size estimation, is not strictly defined by CMS, introducing variability that may compromise consistency. This study evaluates five methods for calculating patient size and their impact on SAD and compliance.
Methods:
A retrospective analysis of 719 CT examinations across seven CT protocols was performed. These included five abdomen and two chest protocols covering various CT categories based on University of California San Francisco examples cited in the CMS measure. Five methods for calculating patient diameter were evaluated: Hounsfield unit (HU) Value Thresholding, Water-Equivalent Diameter (WED), Lateral (LAT) or anterior-posterior (AP) Conversion, LAT×AP, and (LAT + AP)/2. Statistical differences were assessed using Kruskal-Wallis and pairwise tests.
Results:
SAD values demonstrate significant variability between calculation methods. Attenuation-based methods (HU threshold, WED) overestimated SAD in chest examinations, and projection-based methods showed greater variability in abdominal examinations. This variability affects compliance with CMS-defined dose thresholds, with attenuation-based methods resulting in more failures in chest examinations and projection-based methods in abdominal examinations. The Urogram protocol had SAD values >30% below CMS thresholds despite its high-dose category, suggesting potential error in classification or threshold value. Statistically significant differences (P < .05) were found in Chest pulmonary embolism, Chest without, and Urogram protocols.
Conclusions:
Inconsistencies in SAD estimation methods and protocol mapping pose technical challenges that compromise the effectiveness of the metric. Standardized examination mapping and revisiting dose thresholds may improve alignment with clinical practice and enhance the reliability of the CMS measure.
More Related Videos
 10:33
Expedited Radiation Biodosimetry by Automated Dicentric Chromosome Identification ADCI and Dose Estimation
Published on: September 4, 2017
 09:49
A Whole Body Dosimetry Protocol for Peptide-Receptor Radionuclide Therapy PRRT: 2D Planar Image and Hybrid 2D+3D SPECT/CT Image Methods
Published on: April 24, 2020
Related Concept Videos
 01:28
Dosage Regimens: Designs and Approaches
 01:24
Dosage Regimen: Individualization
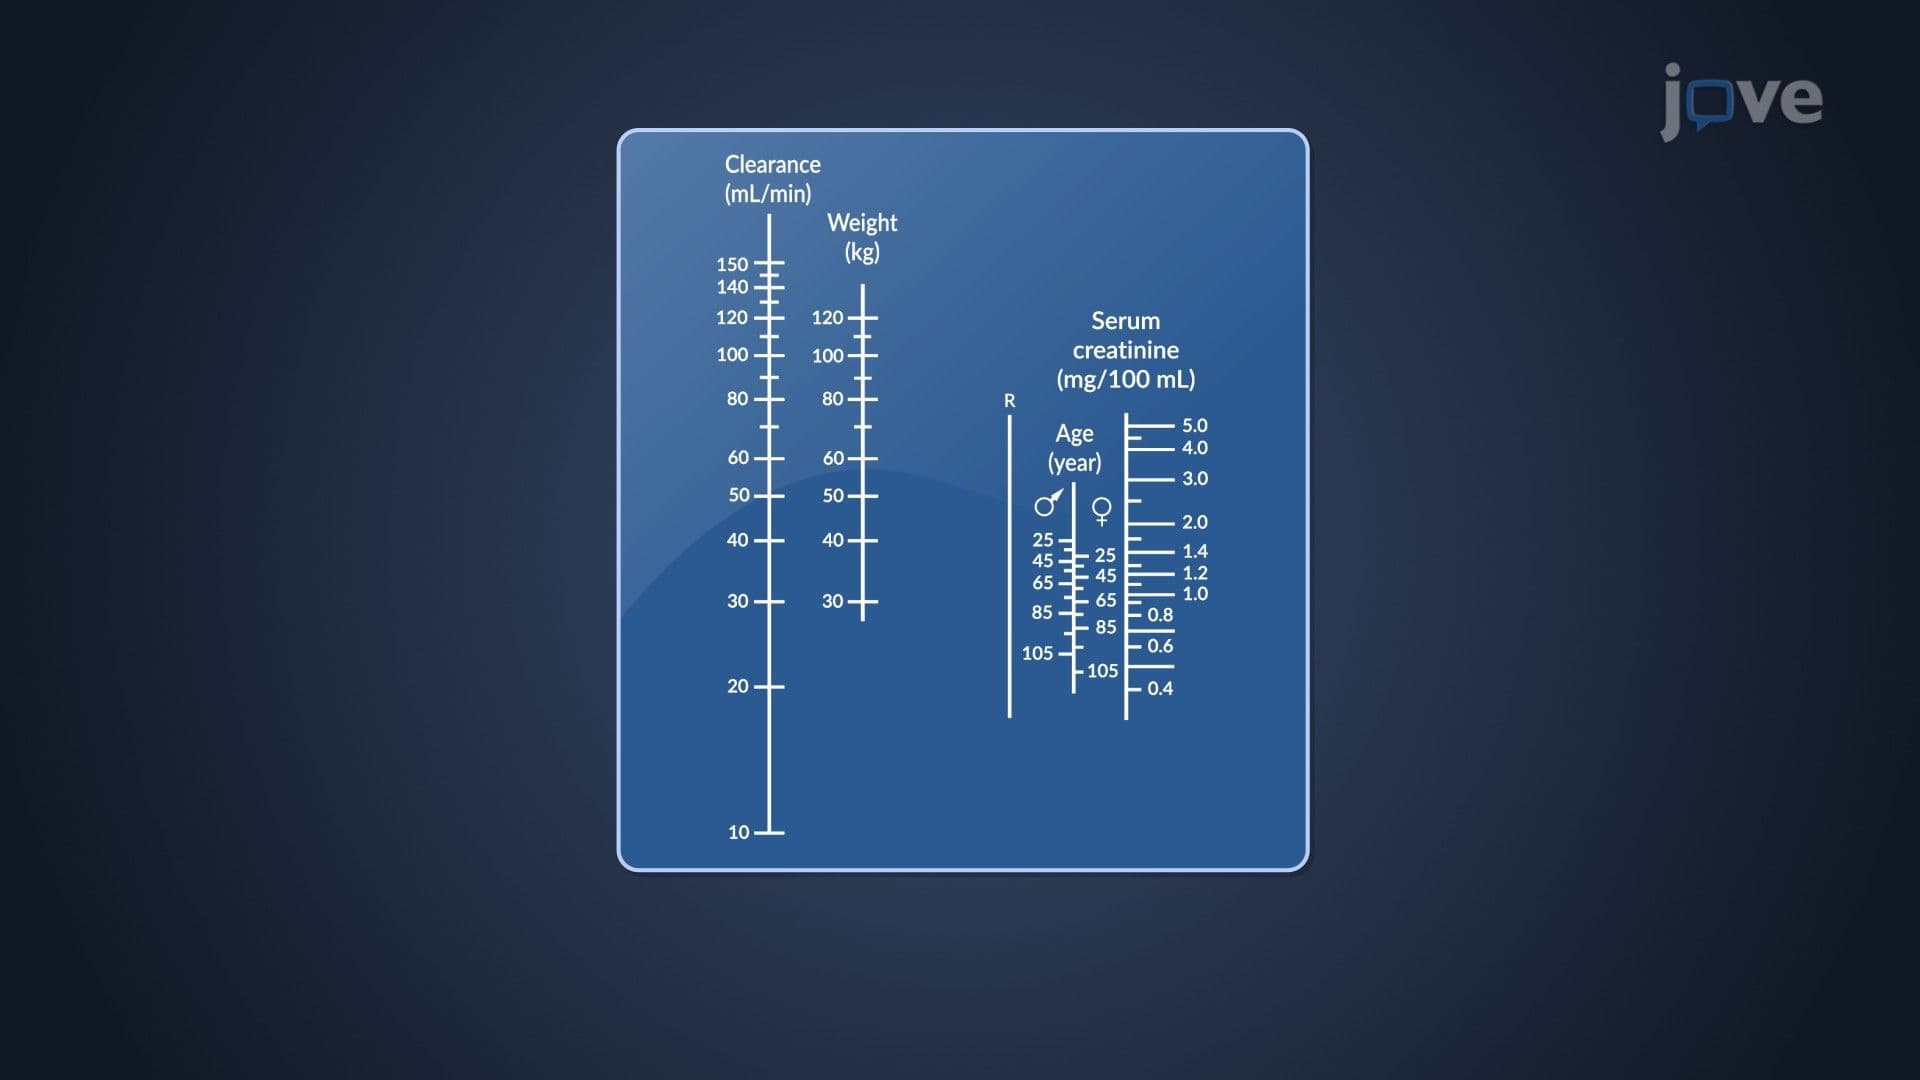 01:23
Dosage Regimen Designs: Nomograms and Tabulations
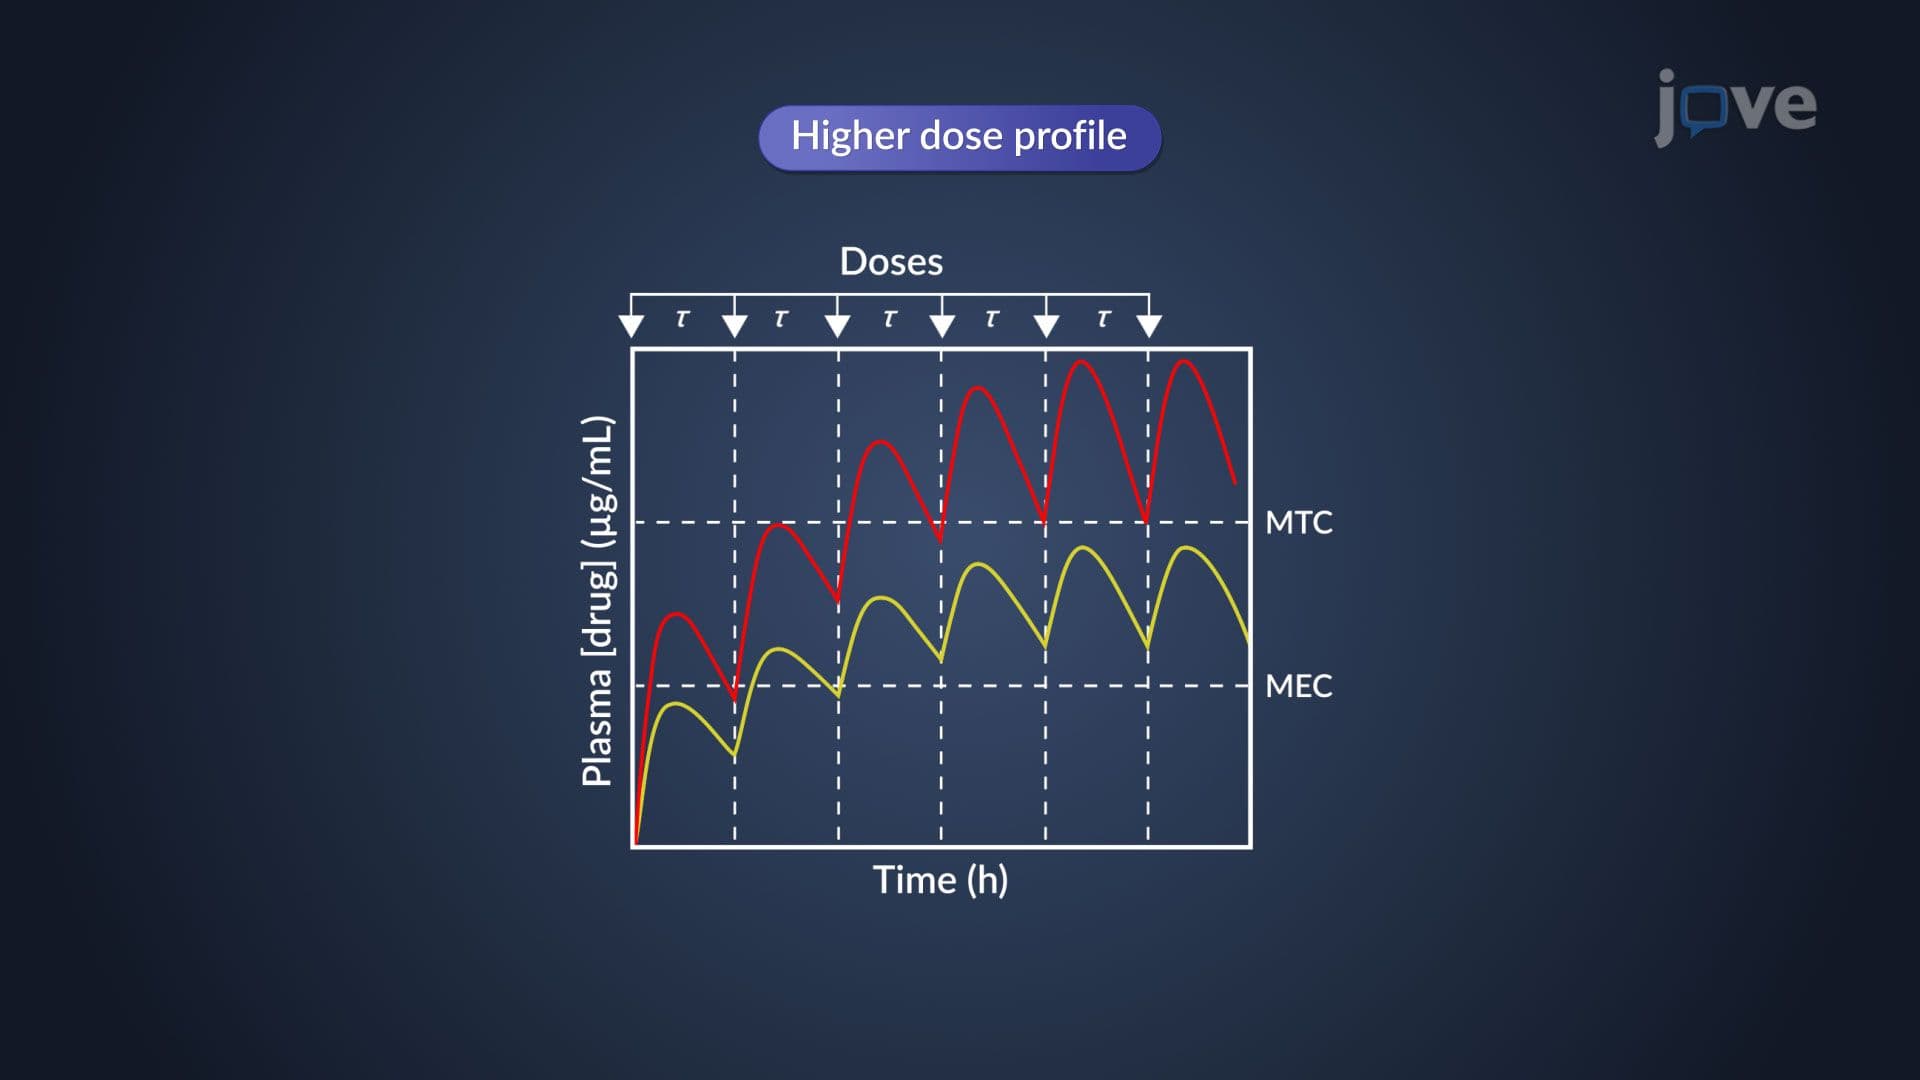 01:21
Dose Size and Dosing Frequency: Determination Methods
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:29
Drug Dosing: Infants and Children