Related Experiment Video
Updated: Sep 13, 2025

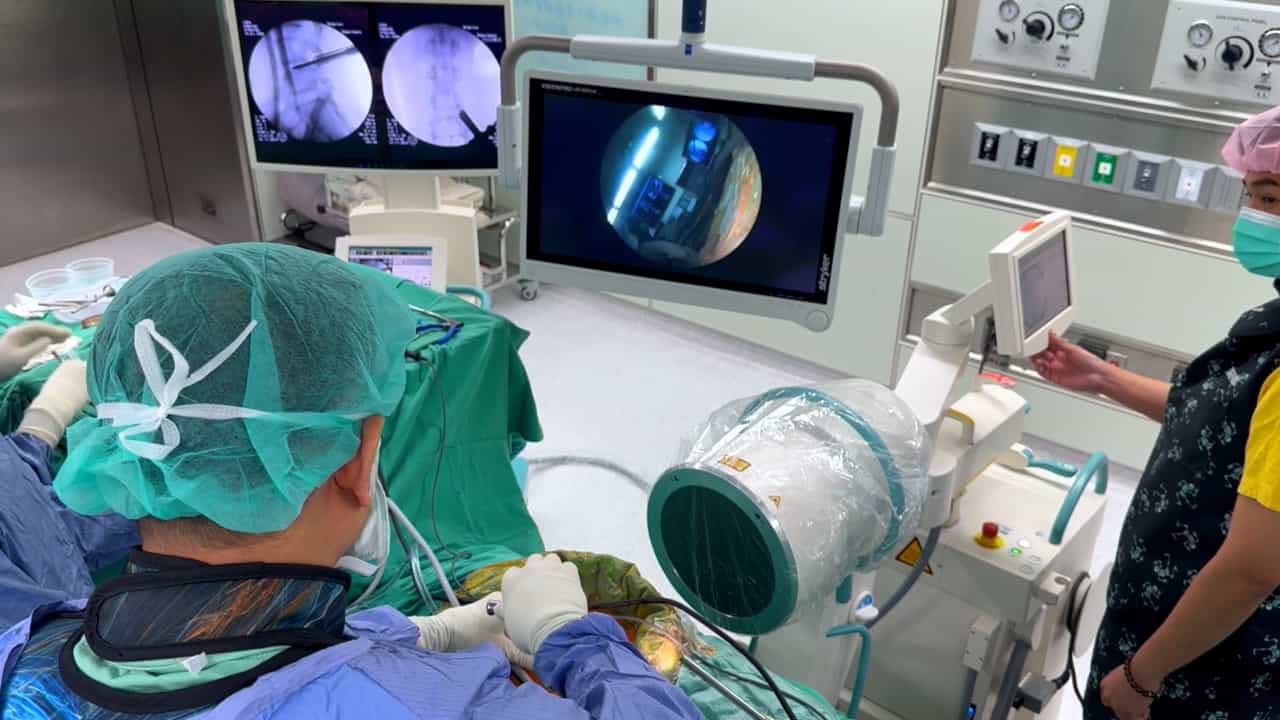
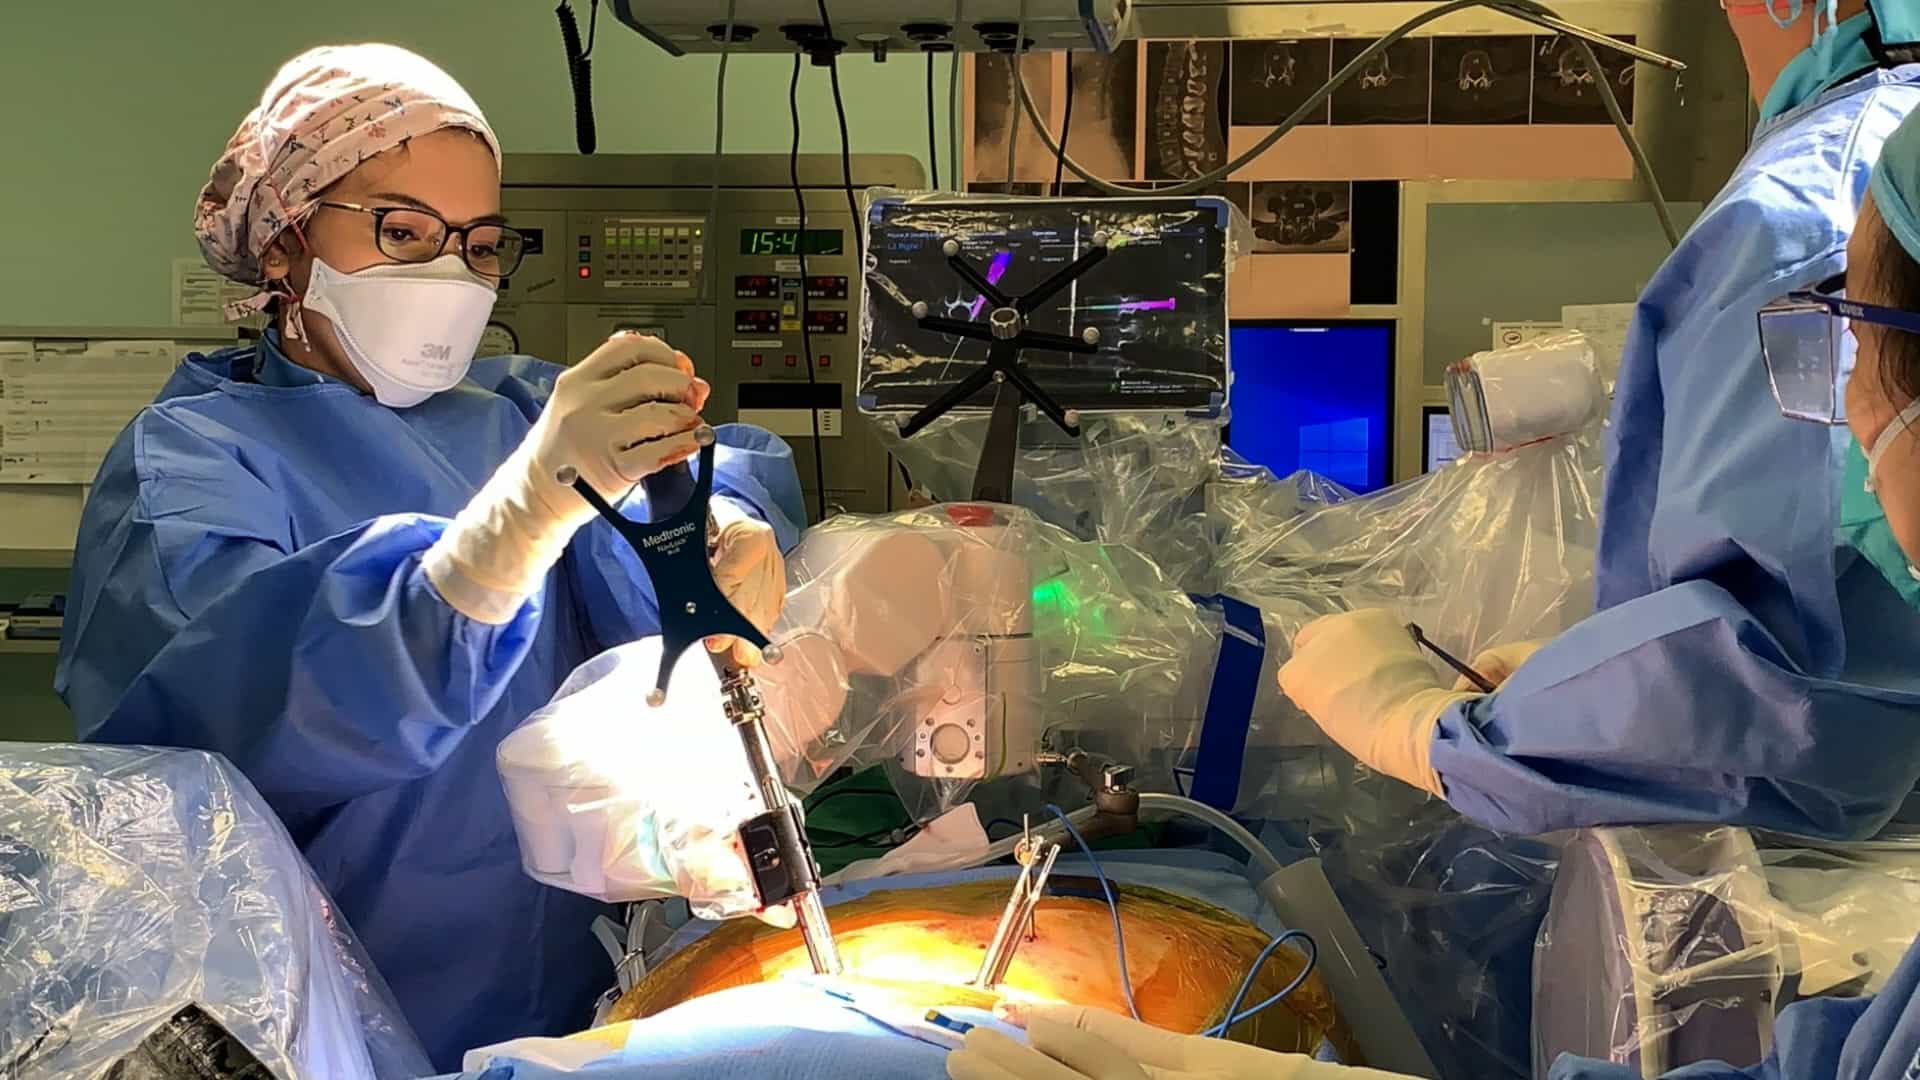
Novel Mini-open Transforaminal Lumbar Interbody Fusion
Published on: June 6, 2025
How are we defining preoperative anemia? A comparison of various anemia thresholds among patients undergoing
Tariq Z Issa1, Omar H Tarawneh2, Teeto Ezeonu2
1Department of Orthopaedic Surgery, Icahn School of Medicine at Mount Sinai Hospital, New York, NY.

Background:
Anemia is a risk factor for increased transfusions. However, various definitions of anemia have been described in scientific literature and a consensus on how to appropriately diagnose anemia or who to preoperatively optimize is lacking. We aimed to compare multiple anemia definitions and evaluate if any threshold best predicts transfusion requirements and surgical outcomes following spinal fusion.
Methods:
We conducted a retrospective cohort study of 1-2 level posterior spinal fusions. Preoperative hemoglobin was defined based on preoperative laboratories within 28 days of surgery. Anemia was diagnosed using the World Health Organization (WHO), the American Society of Hematology (ASH), and the Cleveland Clinic (CC) thresholds. Youden's index and multivariable regressions were utilized to analyze associations of anemia with postoperative outcomes.
Results:
A total of 2257 patients were included. Patients who received a transfusion were more likely anemic regardless of definition (WHO: 60.0% vs. 14.0%, P < 0.001; ASH: 61.0% vs. 17.8%; CC: 70.0% vs. 26.6%; all, P < 0.001). On multivariable regression, all anemia definitions were independently associated with transfusions and nonhome discharge. WHO anemia was associated with the highest odds of transfusion (odds ratio [OR]: 7.48, P < 0.001), followed by ASH anemia (OR: 6.63, P < 0.001), ASH preoperative anemia (OR: 6.45, P < 0.001), and CC anemia (OR: 5.92, P < 0.001). Only WHO anemia was associated with complications (OR: 1.55, P = 0.045). Receiver operating characteristic curves suggest that every anemia threshold was acceptable (area under the curve [AUC] >0.70) for identifying patients needing a postoperative transfusion: ASH preoperative demonstrated the greatest AUC (AUC: 0.746), followed by WHO anemia (AUC: 0.730). All performed poorly in predicting complications (AUC: 0.541-0.553), readmissions (AUC: 0.525-0.535), and nonhome discharge (AUC: 0.561-0.596).
Conclusions:
Small variations in anemia definitions do not significantly impact the identification of patients necessitating a transfusion. However, the more discriminative WHO definition may best predict postoperative complications for lumbar fusions.