Related Experiment Video
Updated: Sep 12, 2025


Measuring Local Anaphylaxis in Mice
Published on: October 14, 2014
Optimizing Adrenaline Administration in Anaphylaxis: Clinical Practice Considerations and Safety Insights
Motohiro Ebisawa1, Antonella Muraro2, Margitta Worm3
1Clinical Research Center for Allergy and Rheumatology, NHO Sagamihara National Hospital, Sagamihara, Kanagawa, Japan.

Background:
Anaphylaxis is an acute, severe, and potentially fatal reaction marked by the fast onset of symptoms and organ involvement that may lead to death from vascular collapse or airway obstruction. Despite adrenaline (epinephrine) being the first-line medication for reversing anaphylactic symptoms, misconceptions about its safe and correct use persist and lead to improper administration.
Methods:
This review provides a comprehensive overview of clinical use of adrenaline autoinjectors (AAIs) in the management of anaphylaxis, key safety considerations, and pharmacokinetic/pharmacodynamic profile of three of the currently marketed AAIs.
Results:
When administered intramuscularly (IM) at the recommended dose for anaphylaxis, adrenaline is considered safe; however, adequate training in emergency care is essential to minimize dosage errors and mitigate safety risks. In specific situations, such as refractory anaphylaxis, intravenous (IV) administration is advised under specialized settings due to the potential risk of severe cardiovascular complications that can result from dosing errors.
Conclusion:
Although adrenaline can cause mild and transient side effects even when administered correctly at the recommended dosage, the potential side effects should not deter its use in critical situations such as anaphylaxis. This review aims to highlight the role of AAIs in improving patient outcomes during anaphylactic emergencies.


Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and...
 02:06
Allergic Reactions
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:23
Cardiopulmonary Resuscitation III: AED Use
 01:26
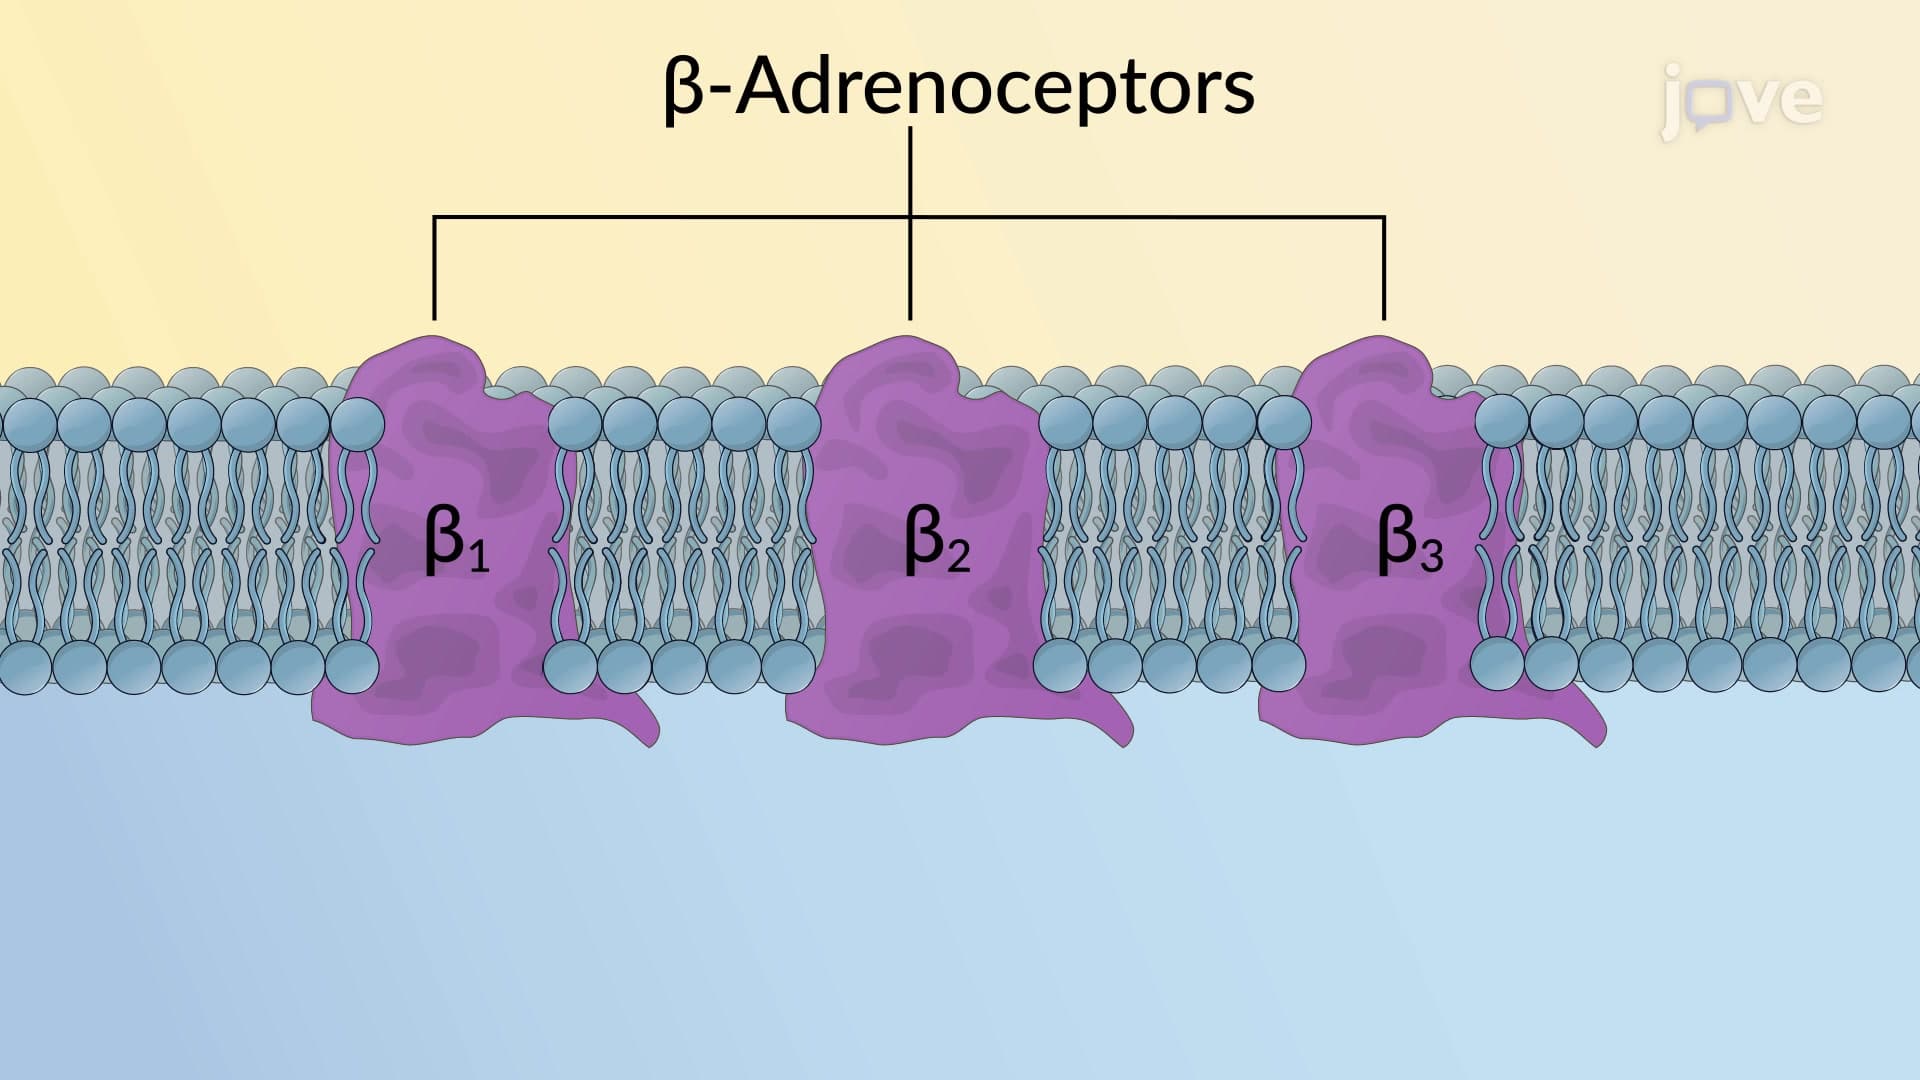
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:28
Adrenergic Agonists: Mixed-Action Agents
Ephedrine and pseudoephedrine lack a catecholamine group, making them less susceptible to degradation by metabolic enzymes. They have increased oral bioavailability and lipophilicity, resulting in a longer duration of action. Their response is reduced by...