Related Experiment Video
Updated: Sep 12, 2025


Role of Diffusion MRI Tractography in Endoscopic Endonasal Skull Base Surgery
Published on: July 5, 2021
Prediction of Diffuse High-Grade Glioma Survival Outcomes Using Preoperative Whole-Brain Tractography-Based
Noah M Nichols1, Nitish Seenarine2, Chi H Le1
1Department of Neurosurgery, Icahn School of Medicine at Mount Sinai, New York , New York , USA.

Background And Objectives:
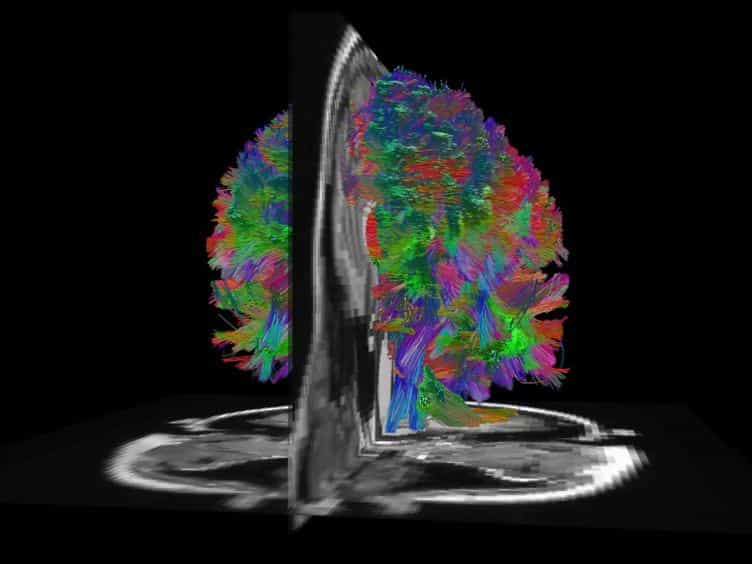
Extent of resection (EOR) is a recognized predictor of survival in adults with diffuse high-grade glioma (HGG) but can only be calculated postoperatively. We developed novel whole-brain tractography (WBT)-based metrics to quantify tumor resectability and predict survival outcomes using only preoperative data.
Methods:
Consecutive adults with biopsied or resected HGGs were retrospectively reviewed. Unresectable tumor volume (UTV) was the total overlapping volume of tumor with eloquent tracts and deep brain structures. Resectability index (RI) was (preoperative tumor volume [PTV]-UTV)/PTV, where PTV was preresection tumor volume. Modified metrics (mRI and mUTV) considered only the corticospinal tract and left arcuate fasciculus. Progression-free and overall survival (OS) were modeled using Cox proportional hazards and accelerated failure time (AFT) multivariable regression.
Results:
We analyzed 146 tumors, of which 84 had preoperative WBT available. Both mRI (area under receiver operating characteristic curve = 0.953) and mUTV (area under receiver operating characteristic curve = 0.854) had robust accuracy in predicting biopsy vs resection at cutoff values of 0.75 and 2.5 cm 3 , respectively. Tumors with the mRI above and below 0.65 had the most significant difference in median OS (not reached vs 82 days, P < .0001). The best-performing AFT model of OS using only preoperative covariates was a log-logistic AFT model (k-fold validated mean C-index = 0.788), in which mUTV was an independent predictor of outcome ( P = .008). Postoperative OS models using WBT-based resectability metrics exhibited significantly higher mean C-indices compared with those using the conventional metrics, EOR and residual tumor volume (0.927 vs 0.874, P < .001).
Conclusion:
Our patient-specific WBT-based HGG resectability metrics closely approximate EOR and residual tumor volume, can be calculated on preoperative imaging, and are strong predictors of survival outcomes after HGG biopsy or resection.