Related Experiment Video
Updated: Sep 12, 2025


Ferric Chloride-induced Murine Thrombosis Models
Published on: September 5, 2016
Complement in antiphospholipid syndrome, time to target?
Marie-Agnès Dragon Durey1, Houcine Hamidi2, Luc Darnige3
1Laboratoire d'immunologie biologique, Hôpital Européen Georges Pompidou, APHP, Paris, France; INSERM UMRS 1138, team "Inflammation, Complement and Cancer", Cordeliers Research Center, Paris, France; Université de Paris Cité, Paris, France; University Hospital Federation (FHU) COMET, Paris, France.

Antiphospholipid syndrome (APS) is an acquired autoimmune thrombophilia. Complement system, which shares common actors with the coagulation cascade, is nowadays well established to be implicated in APS pathophysiology by different mechanisms. In APS, complement activation assessment is not included in the routine care despite numerous studies showing the presence of activation fragments (C4d, C3d, and C5b9) at a systemic level in sera and blood cells' surface but also in affected arterial walls, kidneys, placentas, or heart valves. APS patients are treated to prevent thrombosis recurrence by long-term anticoagulation with vitamin K antagonist. Several case reports described the use of an anti-C5 antibody to treat particular forms of APS (recurrent thrombosis, catastrophic APS) but are not sufficient to conclude on its efficacy. There is still a need to identify relevant biomarkers to help establish the role of the various recently developed complement-targeting molecules in the therapeutic approach to APS.
Antiphospholipid syndrome (APS) is an acquired autoimmune thrombophilia. Complement system, which shares common actors with the coagulation cascade, is nowadays well established to be implicated in APS pathophysiology by different mechanisms. In APS, complement activation assessment is not included in the routine care despite numerous studies showing the presence of activation fragments (C4d, C3d, and C5b9) at a systemic level in sera and blood cells' surface but also in affected arterial walls, kidneys, placentas, or heart valves. APS patients are treated to prevent thrombosis recurrence by long-term anticoagulation with vitamin K antagonist. Several case reports described the use of an anti-C5 antibody to treat particular forms of APS (recurrent thrombosis, catastrophic APS) but are not sufficient to conclude on its efficacy. There is still a need to identify relevant biomarkers to help establish the role of the various recently developed complement-targeting molecules in the therapeutic approach to APS.


Related Concept Videos
 01:27
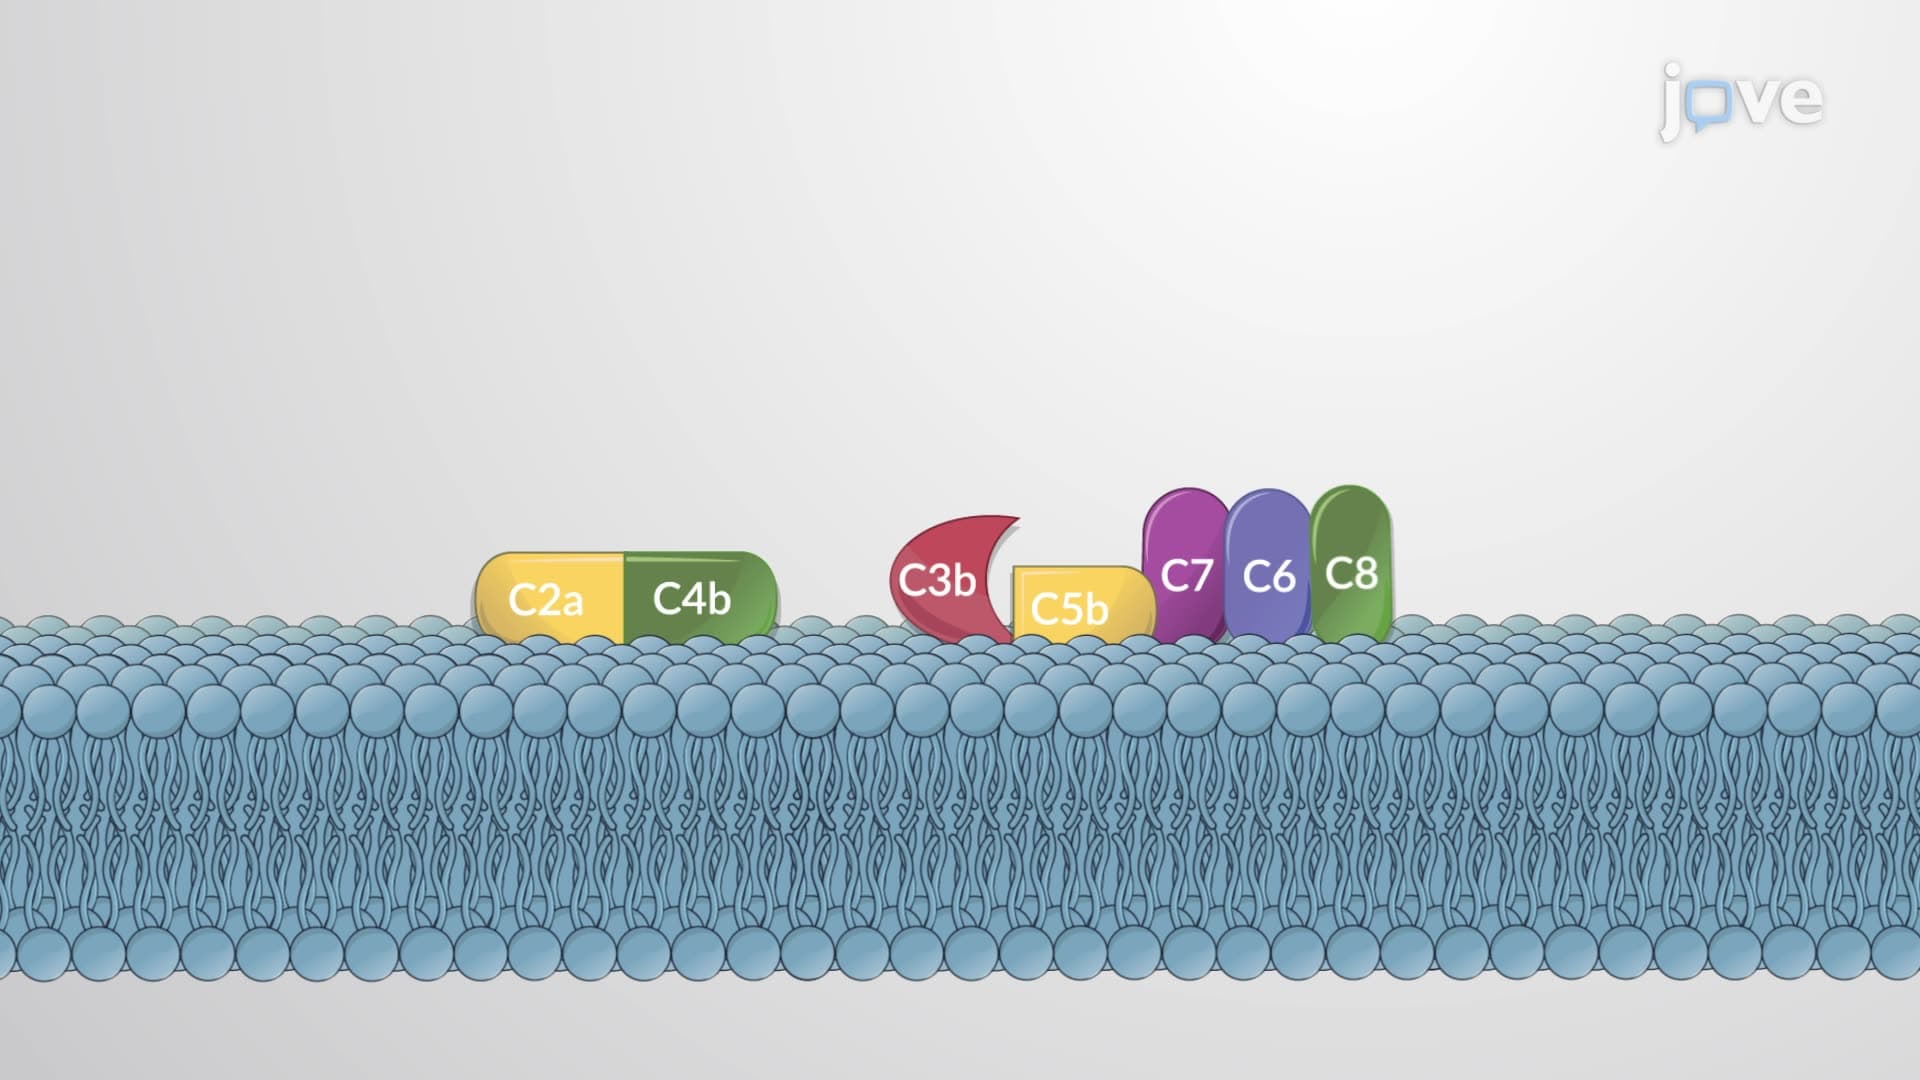
Complement System
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:29
Venous Thrombosis III: Interprofessional Care
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:22
Formation of the Platelet Plug
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...