Risk stratification of childhood infection using host markers of immune and endothelial activation in Asia (Spot Sepsis): a multi-country, prospective, cohort study
Related Experiment Video
Updated: Sep 12, 2025
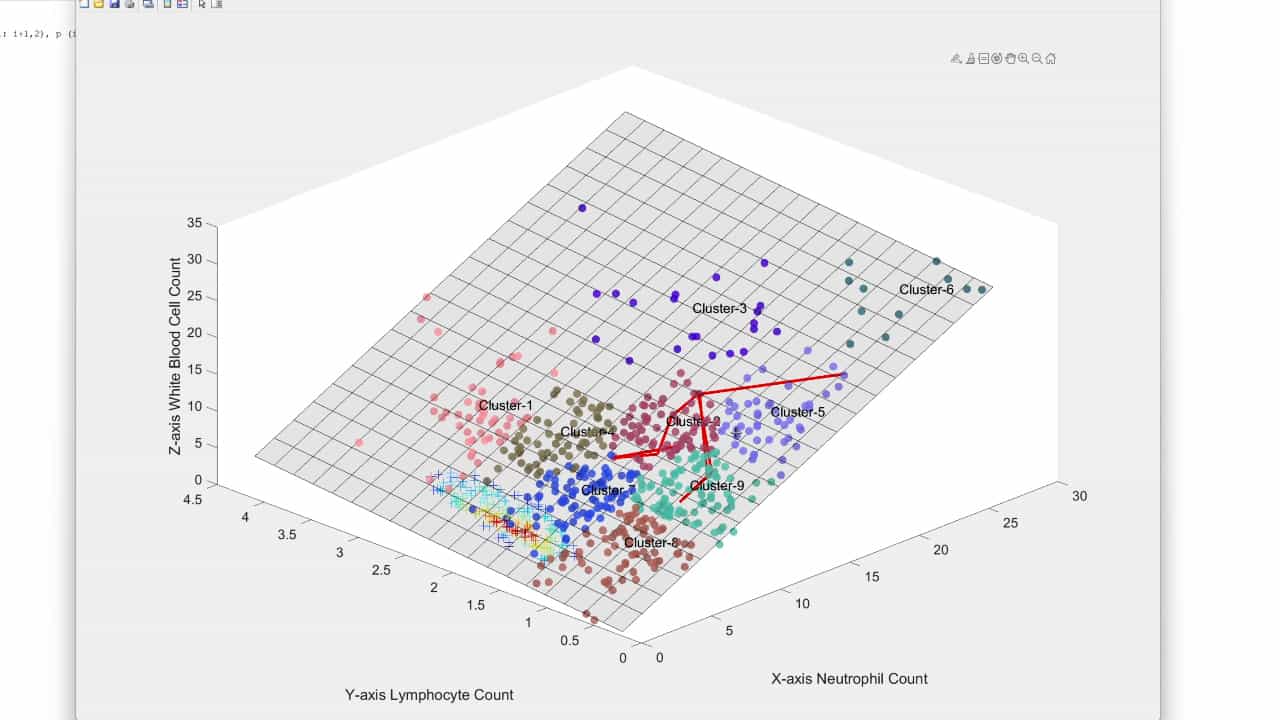
A Data-Driven Approach to Quantifying Immune States in Sepsis
Published on: February 7, 2025
Arjun Chandna1, Constantinos Koshiaris2, Raman Mahajan3
1Cambodia Oxford Medical Research Unit, Angkor Hospital for Children, Siem Reap, Cambodia; Centre for Tropical Medicine and Global Health, University of Oxford, Oxford, UK.

Insights
A novel biomarker, soluble TREM1 (sTREM1), accurately predicts severe febrile illness in children in low-resource Asian settings. This finding supports developing sTREM1-based triage strategies for early risk identification and improved outcomes.
Area of Science:
- Pediatric infectious diseases
- Biomarker discovery
- Global health
Background:
- Prognostic tools for febrile illnesses are crucial in resource-limited community settings.
- Immune and endothelial activation markers can stratify risk in childhood infections.
- This study assessed these markers in children with febrile illness in rural Asia.
Purpose of the Study:
- To evaluate the prognostic accuracy of various biomarkers and clinical scores in identifying severe febrile illness in children.
- To compare the performance of immune and endothelial activation markers against established clinical criteria.
Main Methods:
- Prospective cohort study (Spot Sepsis) in seven Asian hospitals involving children aged 1-59 months with acute febrile illness.
- Measured concentrations of immune and endothelial activation markers, WHO danger signs, LqSOFA, and SIRS scores.
- Compared prognostic accuracy using weighted AUC, logistic regression, and NNT.
Main Results:
- 3423 children were recruited; 3.9% developed severe febrile illness.
- Soluble TREM1 (sTREM1) demonstrated the highest prognostic accuracy (AUC 0.86), outperforming WHO danger signs, LqSOFA, and SIRS.
- Combining WHO danger signs with sTREM1 did not improve accuracy over sTREM1 alone.
Conclusions:
- sTREM1 exhibits superior prognostic accuracy for identifying children at risk of severe febrile illness.
- An sTREM1-based triage strategy could enhance early recognition of poor outcomes in resource-constrained settings.
Background:
Prognostic tools for febrile illnesses are urgently required in resource-constrained community contexts. Circulating immune and endothelial activation markers stratify risk in common childhood infections. We aimed to assess their use in children with febrile illness presenting from rural communities across Asia.
Methods:
Spot Sepsis was a prospective cohort study across seven hospitals in Bangladesh, Cambodia, Indonesia, Laos, and Viet Nam that serve as a first point of contact with the formal health-care system for rural populations. Children were eligible if aged 1-59 months and presenting with a community-acquired acute febrile illness that had lasted no more than 14 days. Clinical parameters were recorded and biomarker concentrations measured at presentation. The primary outcome measure was severe febrile illness (death or receipt of organ support) within 2 days of enrolment. Weighted area under the receiver operating characteristic curves (AUC) were used to compare prognostic accuracy of endothelial activation markers (ANG-1, ANG-2, and soluble FLT-1), immune activation markers (CHI3L1, CRP, IP-10, IL-1ra, IL-6, IL-8, IL-10, PCT, soluble TNF-R1, soluble TREM1 [sTREM1], and soluble uPAR), WHO danger signs, the Liverpool quick Sequential Organ Failure Assessment (LqSOFA) score, and the systemic inflammatory response syndrome (SIRS) score. Prognostic accuracy of combining WHO danger signs and the best performing biomarker was analysed in a weighted logistic regression model. Weighted measures of classification were used to compare prognostic accuracies of WHO danger signs and the best performing biomarker and to determine the number of children needed to test (NNT) to identify one additional child who would progress to severe febrile illness. The study was prospectively registered on ClinicalTrials.gov, NCT04285021.
Findings:
3423 participants were recruited between March 5, 2020, and Nov 4, 2022, 18 (0·5%) of whom were lost to follow-up. 133 (3·9%) of 3405 participants developed severe febrile illness (22 deaths, 111 received organ support; weighted prevalence 0·34% [95% CI 0·28-0·41]). sTREM1 showed the highest prognostic accuracy to identify patients who would progress to severe febrile illness (AUC 0·86 [95% CI 0·82-0·90]), outperforming WHO danger signs (0·75 [0·71-0·80]; p<0·0001), LqSOFA (0·74 [0·69-0·78]; p<0·0001), and SIRS (0·63 [0·58-0·68]; p<0·0001). Combining WHO danger signs with sTREM1 (0·88 [95% CI 0·85-0·91]) did not improve accuracy in identifying progression to severe febrile illness over sTREM1 alone (p=0·24). Sensitivity for identifying progression to severe febrile illness was greater for sTREM1 (0·80 [95% CI 0·73-0·85]) than for WHO danger signs (0·72 [0·66-0·79]; NNT=3000), whereas specificities were comparable (0·81 [0·78-0·83] for sTREM1 vs 0·79 [0·76-0·82] for WHO danger signs). Discrimination of immune and endothelial activation markers was best for children who progressed to meet the outcome more than 48 h after enrolment (sTREM1: AUC 0·94 [95% CI 0·89-0·98]).
Interpretation:
sTREM1 showed the best prognostic accuracy to discriminate children who would progress to severe febrile illness. In resource-constrained community settings, an sTREM1-based triage strategy might enhance early recognition of risk of poor outcomes in children presenting with febrile illness.
Funding:
Médecins Sans Frontières, Spain, and Wellcome.
Translations:
For the Arabic and French translations of the abstract see Supplementary Materials section.