Comparative longitudinal analysis of pulmonary function post-pediatric Allo-HSCT: benign vs. malignant diseases and early predictors
Related Experiment Video
Updated: Sep 12, 2025

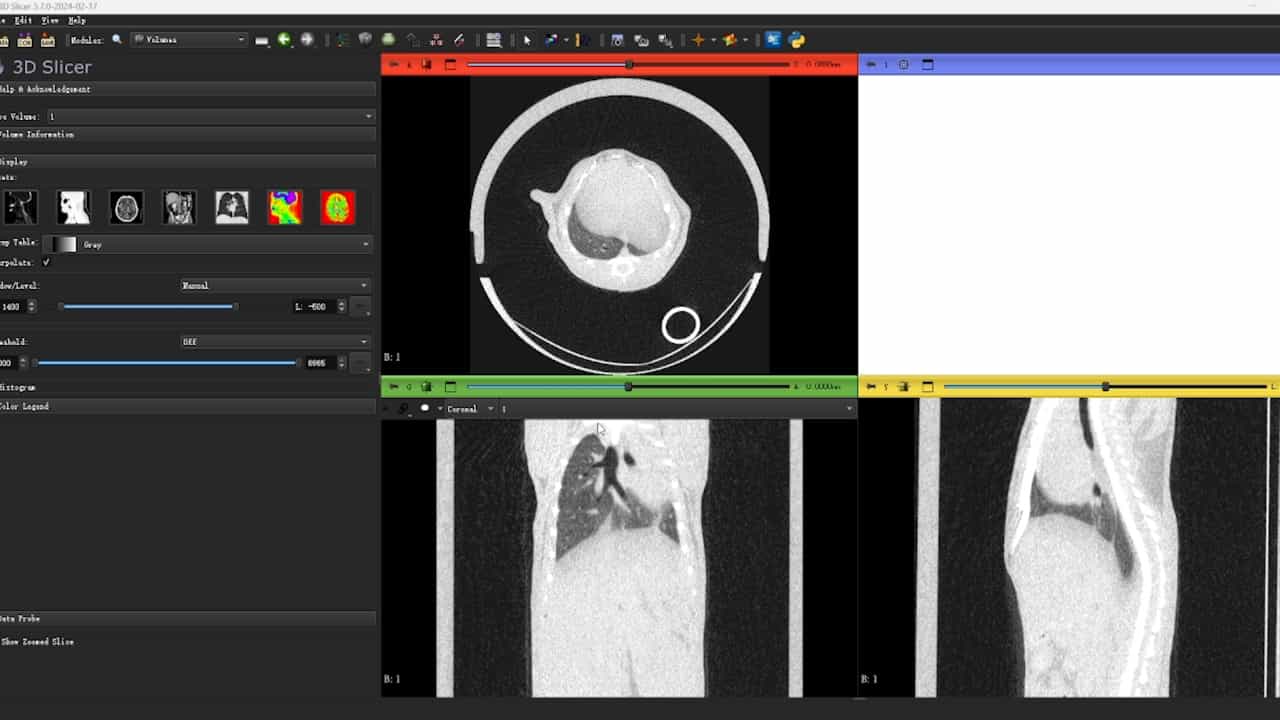
Pre-Conditioning the Airways of Mice with Bleomycin Increases the Efficiency of Orthotopic Lung Cancer Cell Engraftment
Published on: June 28, 2018
Hongjuan Li1, Yan Gu1, Xiaowei Zhao1
1Department of Pediatric Hematology, The First Affiliated Hospital of Shandong First Medical University & Shandong Provincial Qianfoshan Hospital, No. 16766, Jing Shi Road, Lixia District, Jinan, 250014, Shandong, China.

Insights
Pediatric stem cell transplant patients with malignant diseases face higher risks of long-term lung problems. Early pulmonary function tests and graft-versus-host disease presence predict future breathing issues.
Area of Science:
- Pediatric Hematology
- Pulmonology
- Transplantation Medicine
Background:
- Pulmonary complications are a significant cause of morbidity after pediatric allogeneic hematopoietic stem cell transplantation (allo-HSCT).
- Longitudinal pulmonary function test (PFT) trajectories and early predictors of lung dysfunction, especially concerning underlying disease, PFTs, and graft-versus-host disease (GVHD), are not well understood.
Purpose of the Study:
- To analyze longitudinal PFT trajectories in children post-allo-HSCT.
- To identify early predictors of obstructive (OVD) and restrictive ventilatory disorders (RVD), including 3-month PFT values and GVHD.
Main Methods:
- Retrospective analysis of 233 children undergoing their first allo-HSCT with ≥100-day survival.
- Patients categorized into benign (aplastic anemia) and malignant (leukemia/lymphoma) groups.
- Longitudinal PFTs assessed over 24 months; Kaplan-Meier and multivariate logistic regression used for predictor analysis.
Main Results:
- The malignant group showed slower FEV1 recovery, more severe RVD, and diffusion impairment.
- Malignant group had higher cumulative incidences of OVD and RVD, along with increased rates of acute and chronic GVHD.
- Lower 3-month FVC%pred and chronic GVHD predicted RVD; lower 3-month MEF50%pred, acute, and chronic GVHD predicted OVD.
Conclusions:
- Children with malignant diseases experience greater post-HSCT pulmonary dysfunction due to disease intensity and higher GVHD incidence.
- Early post-transplant PFTs (FVC%pred, MEF50%pred) and GVHD development are strong, independent predictors of long-term ventilatory disorders.
- Routine, stratified longitudinal monitoring is crucial for early risk stratification and intervention in pediatric allo-HSCT recipients.
Abstract:
Pulmonary complications are a major cause of morbidity following pediatric allogeneic hematopoietic stem cell transplantation (allo-HSCT). However, longitudinal pulmonary function test (PFT) trajectories and early predictors of dysfunction, particularly the interplay between underlying disease, PFTs, and graft-versus-host disease (GVHD), remain poorly understood. In this retrospective single-center study, we analyzed 233 children undergoing their first allo-HSCT with ≥ 100-day survival. Patients were categorized into benign (acquired aplastic anemia, n = 142) and malignant (leukemia/lymphoma, n = 91) groups. We assessed longitudinal PFTs over 24 months and used Kaplan-Meier and multivariate logistic regression analyses to identify early predictors (including 3-month PFT values and GVHD) for subsequent Obstructive (OVD) and Restrictive Ventilatory Disorders (RVD). Over a median follow-up of 33.1 months, the malignant group exhibited significantly slower FEV1 recovery, greater severity of RVD (P = 0.006) and diffusion impairment (P = 0.040), and higher cumulative incidences of OVD (HR = 3.34, P = 0.013) and RVD (HR = 2.16, P = 0.013). The malignant group also had significantly higher rates of acute (P < 0.001) and chronic GVHD (P < 0.001). In multivariate analysis, the strongest independent predictors for RVD were lower 3-month FVC%pred (OR = 0.85, P < 0.001) and the presence of chronic GVHD (OR = 5.97, P = 0.027). For OVD, predictors were lower 3-month MEF50%pred (OR = 0.95, P = 0.030), acute GVHD (OR = 4.24, P = 0.014), and chronic GVHD (OR = 4.20, P = 0.018). Children with malignant diseases face a higher burden of post-HSCT pulmonary dysfunction, driven by both the underlying disease/treatment intensity and a higher incidence of GVHD. Early post-transplant PFTs (FVC%pred, MEF50%pred) and the development of GVHD are powerful, independent predictors of long-term ventilatory disorders. These findings underscore the need for routine, stratified longitudinal monitoring to facilitate early risk stratification and intervention.