Related Experiment Video
Updated: Sep 11, 2025
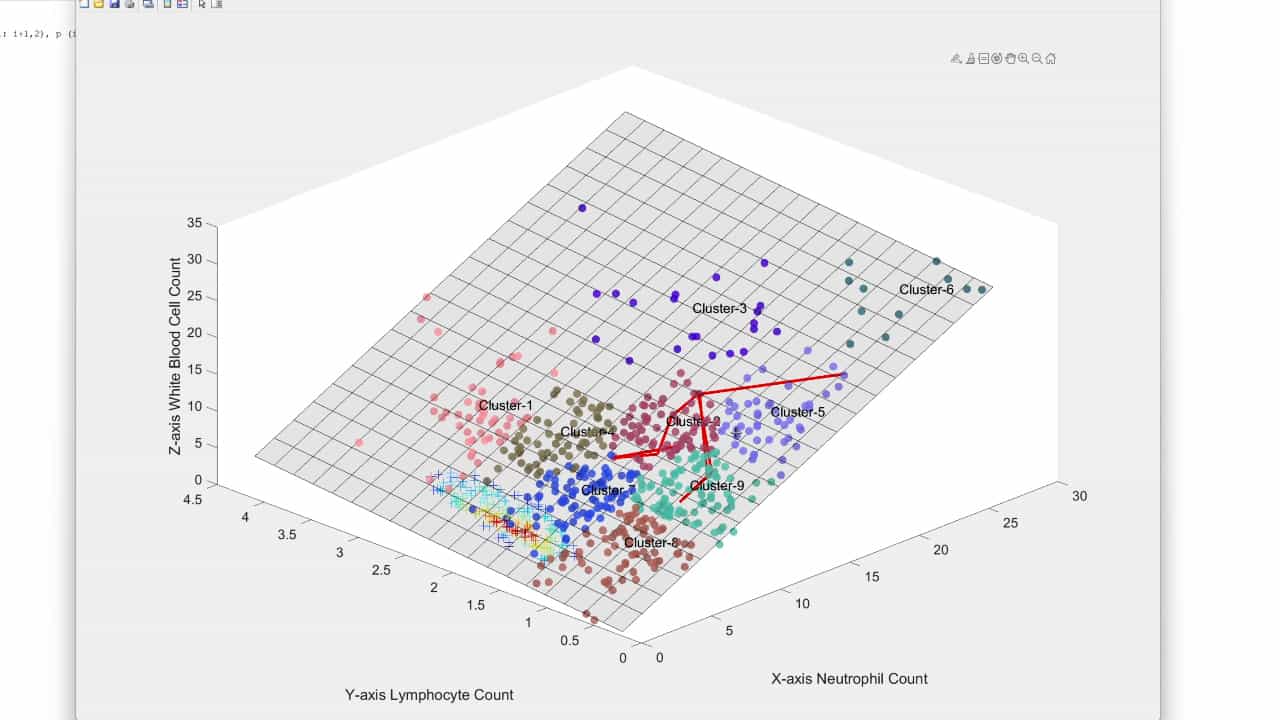

A Data-Driven Approach to Quantifying Immune States in Sepsis
Published on: February 7, 2025
Proactive Telehealth-Based Sepsis Transition and Recovery Support, Hospital Readmission, and Mortality: A Randomized
Stephanie Parks Taylor1, Tara Eaton2, Aleta Rios3
1Division of Hospital Medicine, University of Michigan, Ann Arbor.

Importance:
Sepsis survivors experience high morbidity and mortality after discharge, but health systems lack effective approaches to improve recovery.
Objective:
To evaluate the effect of a sepsis transition and recovery (STAR) program compared with usual care on postdischarge outcomes.
Design, Setting, And Participants:
The ENCOMPASS (Engagement and Collaborative Management to Proactively Advance Sepsis Survivorship) stepped-wedge cluster randomized clinical trial was conducted among adults hospitalized with sepsis at 7 US hospitals in a single health care system from July 2020 to June 2023. Each hospital was a cluster, with 1 randomly transitioning to STAR every 4 months. Follow-up ended in December 2023.
Interventions:
The STAR program was a navigator-led, telehealth-based strategy to proactively deliver evidence-driven postsepsis care to high-risk patients for 90 days after discharge.
Main Outcomes And Measures:
The primary outcome was the composite of all-cause hospital readmission or mortality within 90 days of discharge.
Results:
Of 3548 patients enrolled, 1843 (52%) were women, and the median (IQR) age was 68 (57-77) years; 1160 (33%) were admitted to the intensive care unit. A total of 1426 patients were randomized to the usual care group and 2122 patients were randomized to the STAR group. In the STAR group, 1393 patients (66%) engaged with the STAR program at least once after discharge. The composite all-cause readmission or mortality at 90 days did not differ between the STAR and usual care groups (1023 [48.2%] vs 684 [48.0%]; adjusted odds ratio, 1.05; 95% CI, 0.90-1.24; P = .53). Analysis of the outcomes separately demonstrated a lower frequency of death among patients in the STAR group compared with those in the usual care group (367 [17.3%] vs 292 [20.5%]; adjusted odds ratio, 0.88; 95% CI, 0.77-0.99; P = .04) and a higher frequency of readmission among patients in the STAR group (763 [35.9%] vs 478 [33.5%]; adjusted odds ratio, 1.13; 95% CI, 0.92-1.38; P = .24).
Conclusions And Relevance:
In this randomized clinical trial, a multicomponent, navigator-led STAR program did not reduce the composite of all-cause readmission and mortality at 90 days after discharge.
Trial Registration:
ClinicalTrials.gov Identifier: NCT04495946.
More Related Videos
 07:30
Design of Cecal Ligation and Puncture and Intranasal Infection Dual Model of Sepsis-Induced Immunosuppression
Published on: June 15, 2019
 07:31
Implementation of a Real-Time Psychosis Risk Detection and Alerting System Based on Electronic Health Records using CogStack
Published on: May 15, 2020
Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:11
Clinical Trials: Overview
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:16
Clinical Trials
There are four phases in a clinical trial. A phase one...