Related Experiment Video
Updated: Sep 11, 2025

Multispectral Real-time Fluorescence Imaging for Intraoperative Detection of the Sentinel Lymph Node in Gynecologic Oncology
Published on: October 20, 2010
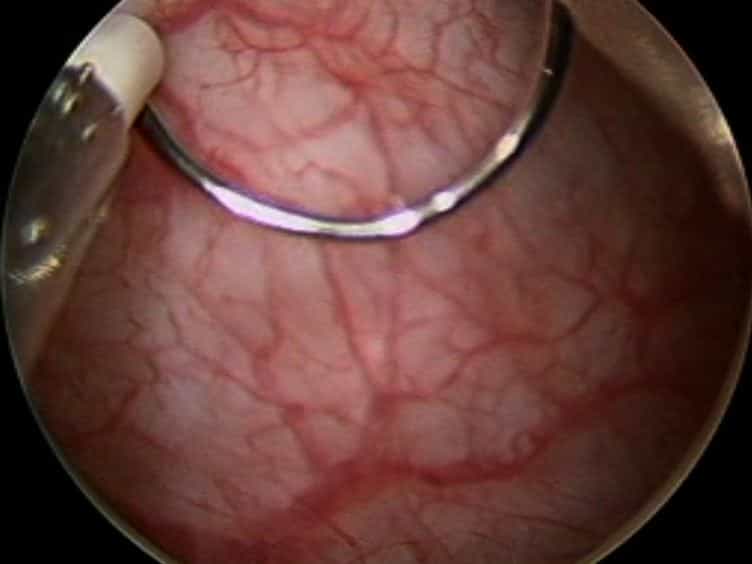
Transanal endoscopic microsurgery with the fluorescence lymphangiography
Kseniia Vorotyntseva1, Vladymyr Grubnik2, Viktor Grubnyk2
1Department of Surgery, Radiation Diagnostics, Radiation Medicine, Therapy and Oncology, Odessa National Medical University, Valikhovsky Lane 2, Odesa, 65082, Ukraine. drvorotyntseva@ukr.net.

Background:
Early-stage rectal cancer can be managed with transanal endoscopic microsurgery (TEM) as a minimally invasive alternative to radical surgery. However, a major limitation of TEM is the potential for occult metastases in mesorectal lymph nodes.
Objective:
To evaluate the feasibility and clinical utility of indocyanine green (ICG) fluorescence lymphangiography for sentinel lymph node detection during TEM.
Methods:
A total of 95 patients with early-stage rectal cancer underwent TEM using a rigid rectoscope platform (Karl Storz TEO, Germany). Full-thickness local excision with 1-2 cm margins and primary defect closure was performed. In patients with enlarged mesorectal nodes on preoperative MRI, 5 mg of ICG was injected submucosally around the tumor, followed by laparoscopic near-infrared observation and sentinel node excision for pathological analysis.
Results:
From 2009 to 2024, 95 patients (52 men, 43 women; mean age 67.4 ± 7.2 years) underwent TEM. The mean operative time was 95.5 ± 15.4 min. Postoperative complications occurred in 7 patients (7.4%), primarily bleeding and pulmonary events; no anastomotic leaks or perioperative mortality were observed. Sentinel lymph node mapping was performed in 23 patients, with occult metastases detected in 6 cases (26.1%). These patients were advised radical resection with total mesorectal excision (TME); 4 underwent TME, and 2 opted for chemotherapy. During a 12-60 month follow-up, local recurrence occurred in 3 of 56 patients with T1-T2 tumors (5.4%) and in 5 of 39 downstaged T3 patients (12.8%).
Conclusions:
TEM offers a safe, minimally invasive approach for early-stage rectal cancer. The adjunct use of ICG lymphangiography enhances detection of mesorectal lymph node metastases and helps identify patients who may require additional radical surgery with TME.
Insights
Transanal endoscopic microsurgery (TEM) is a minimally invasive option for early rectal cancer. Adding indocyanine green (ICG) fluorescence lymphangiography helps detect lymph node metastases, guiding further treatment decisions.
Area of Science:
- Surgical Oncology
- Minimally Invasive Surgery
- Diagnostic Imaging
Background:
- Transanal endoscopic microsurgery (TEM) is a minimally invasive surgical option for early-stage rectal cancer.
- A key limitation of TEM is the potential for undetected metastases in mesorectal lymph nodes.
Purpose of the Study:
- To assess the feasibility and clinical value of using indocyanine green (ICG) fluorescence lymphangiography for sentinel lymph node detection during TEM.
- To improve the accuracy of staging for early-stage rectal cancer patients undergoing TEM.
Main Methods:
- 95 patients with early-stage rectal cancer underwent TEM with a rigid rectoscope platform.
- Indocyanine green (ICG) was injected submucosally around the tumor in patients with enlarged mesorectal nodes on MRI.
- Sentinel lymph nodes were identified using laparoscopic near-infrared observation and surgically removed for pathological analysis.
Main Results:
- Sentinel lymph node mapping was successful in 23 patients, identifying occult metastases in 6 cases (26.1%).
- Patients with detected metastases were recommended for radical resection with total mesorectal excision (TME) or chemotherapy.
- Follow-up showed local recurrence rates of 5.4% for T1-T2 tumors and 12.8% for downstaged T3 tumors.
Conclusions:
- Transanal endoscopic microsurgery (TEM) provides a safe and minimally invasive approach for early rectal cancer.
- Indocyanine green (ICG) lymphangiography enhances the detection of mesorectal lymph node metastases.
- This technique aids in identifying patients who may benefit from additional radical surgery (TME).