Related Experiment Video
Updated: Sep 11, 2025
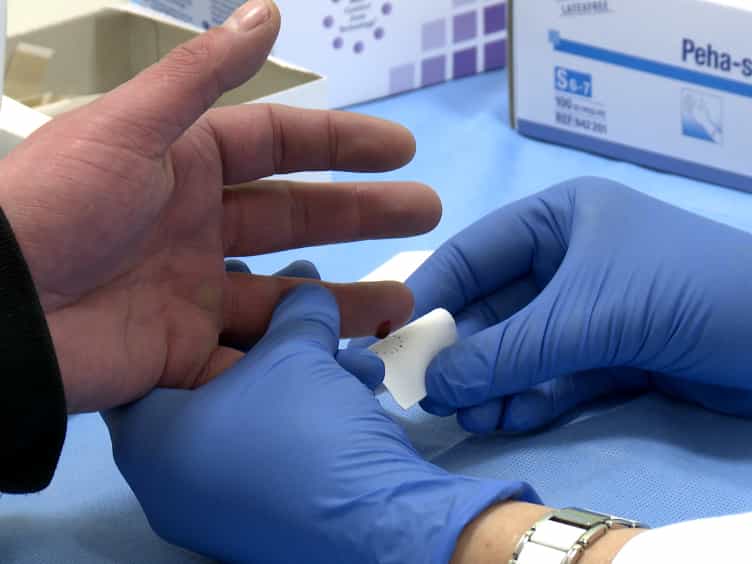

Dried Blood Spots - Preparing and Processing for Use in Immunoassays and in Molecular Techniques
Published on: March 13, 2015
Interlaboratory comparison of a dried blood spot assay for antiretroviral adherence: implications for clinical
Nathan Engel1, Craig Sykes1, Amanda P Schauer1
1Division of Pharmacotherapy and Experimental Therapeutics, UNC Eshelman School of Pharmacy, University of North Carolina at Chapel Hill, 301 Pharmacy Ln, Chapel Hill, NC 27599, USA.

Background And Objectives:
The active metabolites of HIV pre-exposure prophylaxis (PrEP)-tenofovir-diphosphate and emtricitabine-triphosphate-can be measured in dried blood spots (DBSs) to monitor patient adherence. To this end, multiple HPLC-MS/MS assays have been developed. To inform DBS clinical application by characterizing (i) bias between two HPLC-MS/MS approaches (direct versus indirect measurement) to quantify tenofovir-diphosphate/emtricitabine-triphosphate in DBS; and (ii) room temperature (RT) storage stability.
Methods:
Thirty-eight DBS cards from adults taking emtricitabine/tenofovir disoproxil fumarate or emtricitabine/tenofovir alafenamide for PrEP were analysed by UNC Clinical Pharmacology and Analytical Chemistry Core (CPAC) and Colorado Antiviral Pharmacology Laboratory (CAVP) using published methods. Samples were selected from larger clinical trial datasets to represent a wide range of clinically relevant concentrations. CPAC extracts one 3 mm DBS punch using a directly measured metabolite method, whereas CAVP extracts either one 3 mm (emtricitabine/tenofovir disoproxil fumarate) or two 7 mm (emtricitabine/tenofovir alafenamide) DBS punches using an indirect method. Concentrations were converted to fmol/mm². Bias was assessed by CPAC:CAVP concentration ratios and linear regression. Percent change versus time at RT was fit to a nonlinear regression model.
Results:
CPAC tenofovir-diphosphate was higher [median (IQR) ratio = 1.60 (1.38-1.75)] correlating strongly with CAVP (r2 = 0.97). CPAC emtricitabine-triphosphate was similar [median (IQR) = 1.08 (1.05-1.20)] and correlated (r2 = 0.90) only for CAVP's 3 mm assay. Tenofovir-diphosphate/emtricitabine-triphosphate RT decay fit a three-parameter exponential decay model (r2 = 0.87).
Conclusions:
A 1.6-fold bias adjustment is needed for tenofovir-diphosphate concentrations between assays. When punch size is matched, emtricitabine-triphosphate adjustment is unnecessary, otherwise variability confounds comparison. Bias and stability adjustments aid clinical interpretation for real-world application of this adherence monitoring technique.

