Related Experiment Video
Updated: Sep 11, 2025
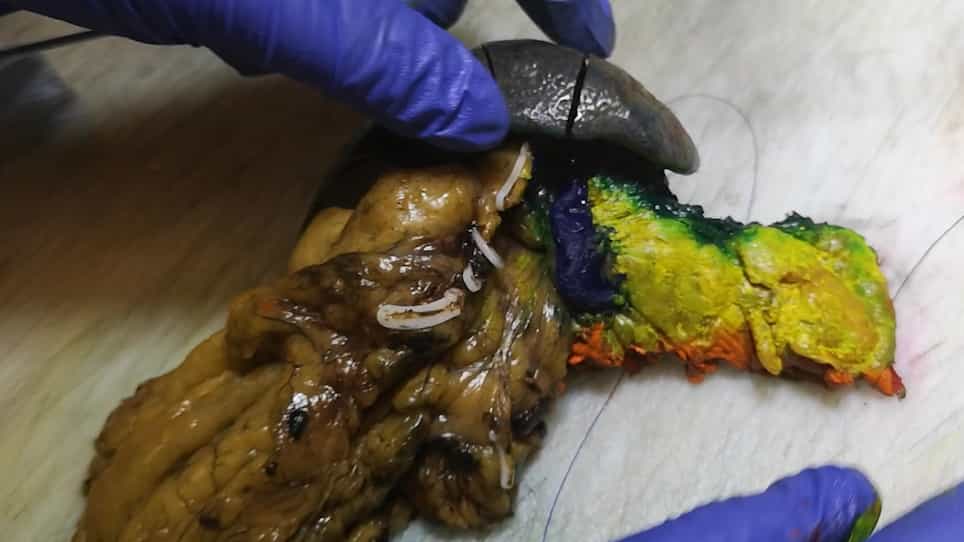

DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Surgical, Histopathological, and Quality of Life Outcomes Following Neoadjuvant Chemotherapy and Pancreatectomy for
Ingvild Farnes1,2, Caroline S Verbeke2,3, Dyre Kleive1
1Department of Hepato-Pancreato-Biliary Surgery, Oslo University Hospital, Rikshospitalet, 0372 Oslo, Norway.

Abstract:
Background/Objectives: Treatment of borderline resectable (BRPC) and locally advanced (LAPC) pancreatic cancer involves neoadjuvant chemotherapy followed by complex surgery, posing significant risks of toxicity, complications, and changes in quality of life (QoL). This study aims to investigate the impact of neoadjuvant chemotherapy followed by resection on overall survival (OS) and QoL. Methods: Consecutive patients with BRPC and LAPC included in a population-based study (NORPACT-2) from January 2018 to December 2020 were reviewed. Results: A total of 54 patients (BRPC; n = 43, LAPC; n = 11) underwent neoadjuvant chemotherapy followed by pancreatectomy. The majority (66.7%) received (m)FOLFIRINOX. Forty-six (85.2%) patients underwent pancreatoduodenectomy. Vascular resection was performed in 32 (59.3%) patients. Fourteen (25.9%) patients experienced major complications. The majority of the resected specimens demonstrated T2 (63%), N+ (79.6%), and R1 (85.2%) status. Median OS was 31 (CI 24.7-37.3) months. In multivariate analysis, only CAP 3 (p = 0.035) predicted worse survival. Forty (74.1%) patients experienced recurrence. Global QoL (p = 0.031), social and role functioning (p = 0.024, p = 0.031), improved three months after surgery. Pain (p = 0.042), dyspnea (p = 0.004), appetite loss (p = 0.028), and diarrhea (p = 0.007) improved post-resection. Conclusions: Patients with BRPC and LAPC undergoing neoadjuvant chemotherapy and resection have survival comparable to primary resectable pancreatic cancer. Postoperative morbidity was acceptable, and QoL recovered post-surgery. CAP grade was the only independent negative prognostic factor.