Related Experiment Video
Updated: Sep 11, 2025


Bronchoalveolar Lavage Exosomes in Lipopolysaccharide-induced Septic Lung Injury
Published on: May 21, 2018
Pleural Fluid Biomarkers in Focus: The Role of Cholesterol and Lactate Dehydrogenase (LDH) in Differentiating
AkhilAnand Pg1, Elen Ann Abraham1, Ghanshyam Verma1
1Department of Respiratory Medicine, Sree Balaji Medical College and Hospital, Chennai, IND.

Abstract:
Background Pleural effusion affects approximately 320 individuals per 100,000 population and can result from a wide range of pulmonary and extrapulmonary conditions. It may present as a complication of an existing illness or as an initial clinical sign, making accurate diagnosis and timely management essential. Under normal physiological conditions, the pleural space contains 7-16 mL of fluid (approximately 0.26 ± 0.1 mL/kg in healthy non-smokers). Effusion develops when fluid production exceeds clearance. Based on pathophysiology, pleural effusions are classified as either transudates or exudates. Light's criteria remain the standard diagnostic tool but may misclassify up to 25% of cases. Recent studies suggest that pleural fluid cholesterol (pCHOL) may offer superior diagnostic accuracy. Aim This study aims to evaluate the reliability and diagnostic accuracy of pCHOL and lactate dehydrogenase (LDH) in distinguishing between transudative and exudative effusions in a tertiary care setting. Methods In this cross-sectional study, 80 patients with pleural effusion were classified as transudative (n = 30) or exudative (n = 50) based on clinical and radiological criteria. Paired pleural fluid and serum samples were collected. Pleural fluid protein, LDH, and cholesterol levels, as well as serum protein and LDH, were analyzed to apply Light's criteria. Diagnostic performance was evaluated using sensitivity, specificity, and predictive values. Statistical analysis was conducted using IBM SPSS Statistics for Windows, Version 21.0 (Released 2012; IBM Corp., Armonk, NY, US), with p < 0.05 considered statistically significant. Results Mean pCHOL was significantly higher in exudative effusions (68.5 ± 20.3 mg/dL) than in transudative effusions (25.2 ± 9.6 mg/dL, p < 0.001). At a cutoff value of 45 mg/dL, pCHOL showed a sensitivity of 98% and specificity of 100%. This outperformed the pleural/serum protein ratio (78%/82%), pleural/serum LDH ratio (86%/93%), and pleural LDH level (88%/90%). The statistically significant difference in pCHOL levels underscores its superior diagnostic utility (p < 0.001). Conclusion pCHOL is a highly sensitive and specific biomarker for identifying exudative pleural effusions and demonstrates better diagnostic performance than Light's criteria. Its simplicity, cost-effectiveness, and diagnostic reliability support its routine inclusion in pleural fluid analysis.
Related Concept Videos
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's...
 01:28
Pleural Effusion II: Symptoms and Management
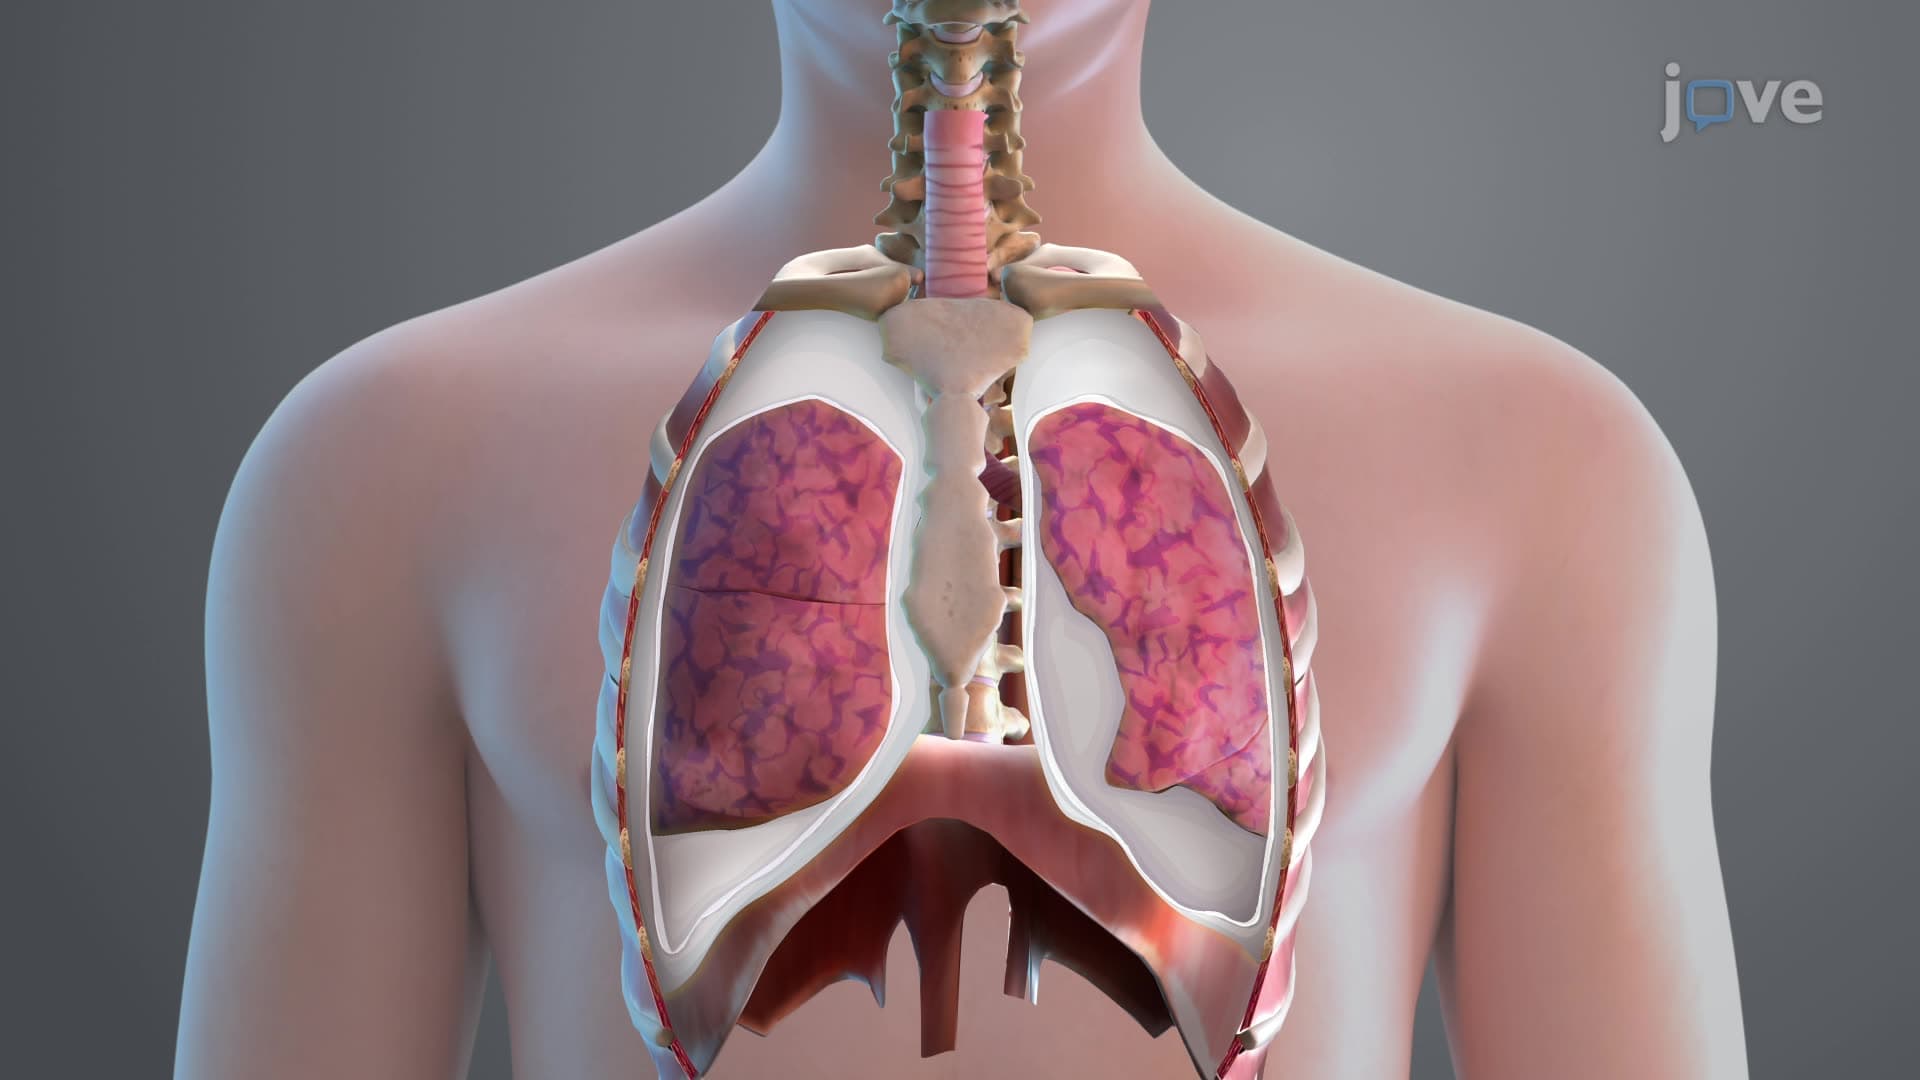
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:13
Pleura of the Lungs
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:24
Inflammatory Response II: Inflammatory Exudate and Tissue Repair
The typical wound exudate is odorless, transparent, straw-colored, thin, and watery. Exudate, however, can differ depending on the state of wound healing. Likewise, the...