Related Experiment Video
Updated: Sep 11, 2025
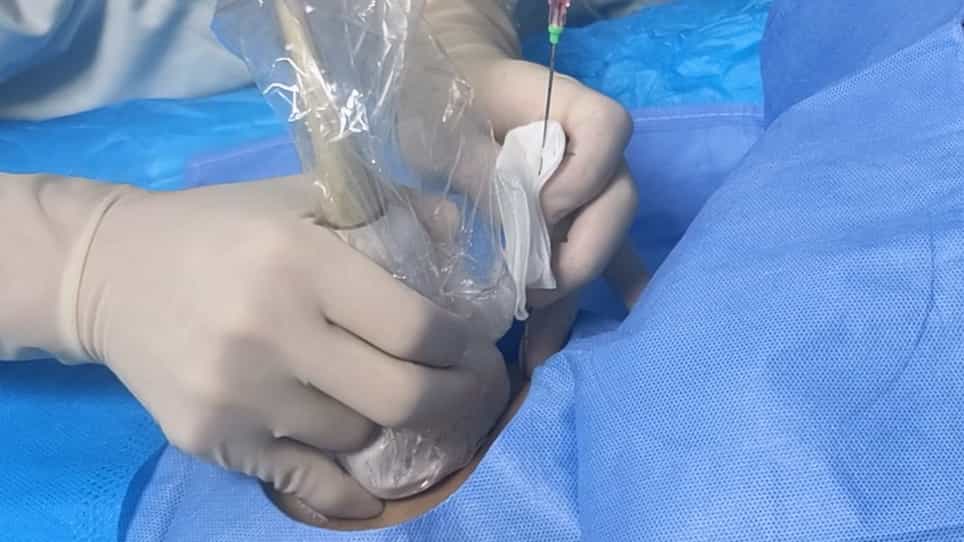
A Two-Step Method for Percutaneous Transhepatic Choledochoscopic Lithotomy
Published on: September 13, 2022
Clinical and cost-effectiveness of percutaneous nephrolithotomy, flexible ureterorenoscopy and extracorporeal
Oliver Wiseman1, Daron Smith2, Kath Starr3
1Department of Urology, Addenbrooke's Hospital, Cambridge University Hospitals NHS Trust, Cambridge, UK.

Background:
Renal tract stone disease is common. The three intervention options are shockwave lithotripsy, flexible ureteroscopic stone treatment and keyhole surgery.
Objectives:
To determine which of shockwave lithotripsy, flexible ureteroscopic stone treatment and keyhole surgery offer the best outcomes in terms of health and quality of life, clinical effectiveness and cost-effectiveness for people with lower pole kidney stones.
Design:
The PUrE study comprised two pragmatic multicentre, open-label, superiority randomised controlled trials: RCT1 for lower pole stones ≤ 10 mm and RCT2 for lower pole stones > 10 and ≤ 25 mm.
Setting:
National Health Service Urology departments.
Participants:
Adults presenting with lower pole renal stones, able to undergo any of the treatments and complete trial procedures.
Intervention:
Eligible participants were randomised in RCT1 to flexible ureteroscopic stone treatment or shockwave lithotripsy; and in RCT2 to flexible ureteroscopic stone treatment or keyhole surgery.
Main Outcome Measures:
The primary outcome measure was health status 'area under the curve', measured weekly to 12 weeks post intervention with the EuroQol-5 Dimensions, five-level version. The primary economic outcome was the incremental cost per quality-adjusted life-year gained at 12 months from randomisation.
Results:
RCT1: A total of 461 participants were randomised: 231 to flexible ureteroscopic stone treatment; and 230 to shockwave lithotripsy. RCT2: A total of 159 participants were randomised: 73 to flexible ureteroscopic stone treatment; and 86 to keyhole surgery.
Primary Outcome:
RCT1: The mean health status area under the curve was 0.807 (standard deviation 0.205) in the flexible ureteroscopic stone treatment group (n = 164) and 0.826 (standard deviation 0.207) in the shockwave lithotripsy group (n = 188). The between-group difference, 0.024 (95% confidence interval -0.004 to 0.053), was a small difference in favour of flexible ureteroscopic stone treatment after correcting for a baseline imbalance. Complete stone clearance was higher with flexible ureteroscopic stone treatment (72%) than shockwave lithotripsy (36%). RCT2: The mean health status area under the curve was 0.794 (standard deviation 0.198) in the flexible ureteroscopic stone treatment group (n = 57) and 0.818 (standard deviation 0.217) in the keyhole surgery group (n = 63). The between-group difference, -0.07 (95% confidence interval -0.11 to -0.02), was a borderline meaningful difference favouring keyhole surgery. Complete stone clearance was higher with keyhole surgery (71%) than flexible ureteroscopic stone treatment (48%).
Economic Evaluation:
RCT1: Flexible ureteroscopic stone treatment is more costly (£1138; 95% confidence interval £646 to £1631) and produces 0.017 (95% confidence interval -0.008 to 0.043) additional quality-adjusted life-years; with an incremental cost-effectiveness ratio of £65,163 per quality-adjusted life-year gained. Shockwave lithotripsy has a 99.9% chance of being cost-effective at a £20,000 threshold value. RCT2: Flexible ureteroscopic stone treatment is more costly (£733; 95% confidence interval -£508 to £1973) and produces fewer quality-adjusted life-years (-0.001; 95% confidence interval -0.044 to 0.042). Keyhole surgery has an 87% chance of being cost-effective at a £20,000 threshold value.
Limitations:
Blinding of participants and healthcare providers was not possible. There were differential waiting times between interventions in RCT1; however, adjusting for this gave similar treatment effect estimates.
Conclusions:
The PUrE study found in RCT1 that shockwave lithotripsy was more cost-effective than flexible ureteroscopic stone treatment, with no meaningful difference in patient health status even though complete stone-free rates were higher with flexible ureteroscopic stone treatment. In RCT2, keyhole surgery was more cost-effective than flexible ureteroscopic stone treatment on a micro-costing basis, which better reflects treatment cost differences to the NHS. Keyhole surgery was marginally beneficial for health status with higher complete stone-free rates.
Future Work:
What effect will suction devices, improvements in laser technology, and intraoperative pressure monitoring have on postoperative pain, quality of life, stone-free rates, complications, and costs of flexible ureteroscopic stone treatment? What effect does miniaturisation of keyhole surgery have on postoperative pain, length of stay, complications, stone-free rates and costs?
Trial Registration:
This trial is registered as ISRCTN98970319.
Funding:
This award was funded by the National Institute for Health and Care Research (NIHR) Health Technology Assessment programme (NIHR award ref: 13/152/02) and is published in full in Health Technology Assessment; Vol. 29, No. 40. See the NIHR Funding and Awards website for further award information.
More Related Videos
 03:19
Author Spotlight: Developing a Bedside Protocol for Kidney and Genitourinary Ultrasonography
Published on: June 21, 2024
 06:39
Technical Modification of the Terminal Ureter During Total Transperitoneal Laparoscopic Nephroureterectomy for Upper Urinary Tract Urothelial Carcinoma
Published on: November 22, 2019
Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:30
Urinary Tract Calculi III: Medical Management
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:28
Urinary Tract Calculi V: Nursing Management
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management