Related Experiment Video
Updated: Sep 11, 2025

Application of Laparoscopic Ultrasonography in Primary Choledochal Suture during Combined Two-lens Surgery
Published on: March 28, 2025
The diagnostic performance of ultrasound features for biliary atresia: a systematic review and updated meta-analysis
Qianhui Yang1,2, Yanran Zhang1,2, Yu Meng1,2
1Clinical School of Pediatrics, Tianjin Medical University, Tianjin, 300070, China.

Abstract:
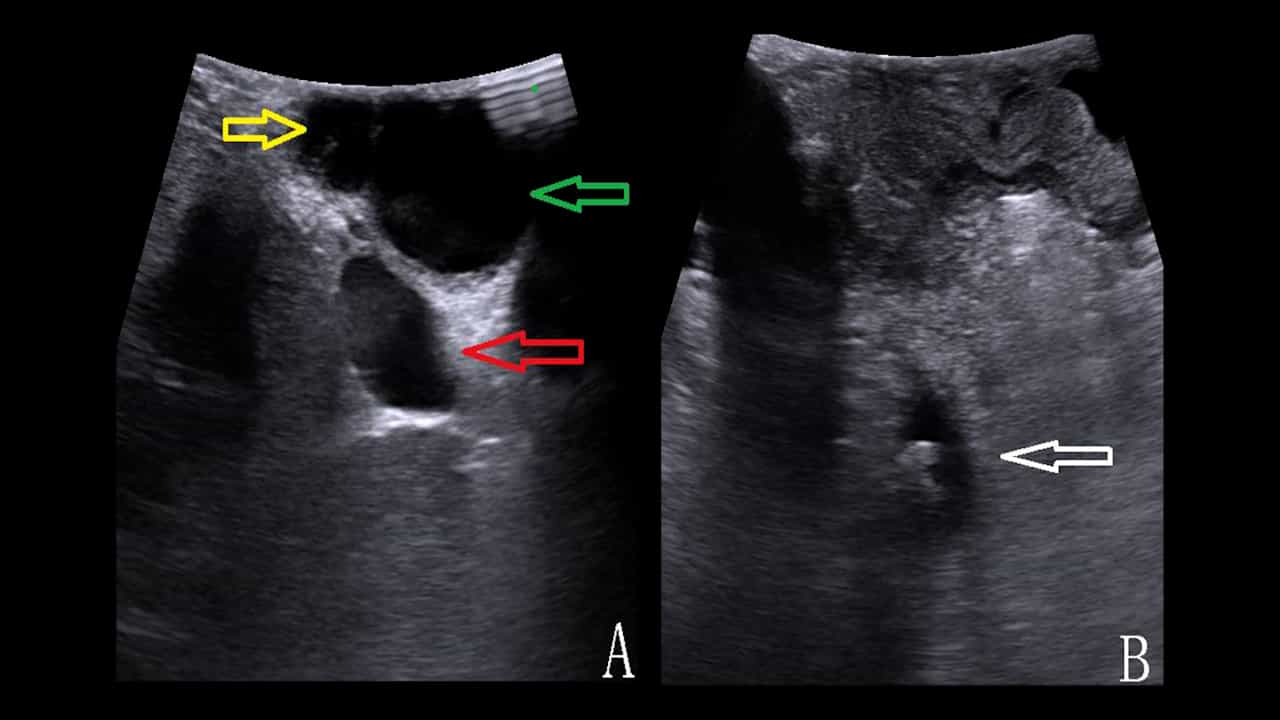
Previous meta-analyses have evaluated the diagnostic performance of various ultrasound (US) features in differentiating biliary atresia (BA) from infantile cholestasis, but none have specifically addressed the accuracy of these features in differentiating cystic biliary atresia (CBA) from infants with jaundice and porta hepatis cysts. We searched PubMed, Embase, Web of Science, Cochrane, China National Knowledge Infrastructure, China Biology Medicine, Wanfang, and VIP databases for articles that evaluated the US features of BA. We pooled effect estimates and constructed summary receiver operating characteristic curves, along with meta-regression and subgroup analysis. The summary sensitivity and specificity for TCS in differentiating BA from infantile cholestasis and CBA from infants with jaundice and porta hepatis cysts were 49.6% (95% CI 48.2%-51.0%) and 70.3% (95% CI 62.7%-77.2%), respectively, and 95.5% (95% CI 94.9%-96.1%) and 99.6% (95% CI 98.0%-100.0%) for the latter. For porta hepatis cysts, sensitivity and specificity were 17.1% (95% CI 13.7%-21.1%) and 84.2% (95% CI 72.1%-92.5%) in differentiating BA, and 99.0% (95% CI 97.4%-99.7%) and 91.3% (95% CI 82.8%-96.4%) for cyst size (length) in distinguishing CBA. For US-guided PTCC, sensitivity and specificity were 100.0% (95% CI 94.9%-100.0%) and 90.6% (95% CI 84.1%-95.0%) for differentiating BA from infantile cholestasis. TCS remains the relatively higher accurate and widely accepted conventional US feature for differentiating BA from infantile cholestasis and CBA from infants with jaundice and porta hepatis cysts. Porta hepatis cysts have the highest specificity for diagnosing BA, with size (length) aiding in distinguishing CBA. The undetected proportions of gallbladder abnormalities-related features were quite variable. Other US features, such as HSF, CBD, and liver stiffness, can support BA diagnosis. While US-guided PTCC is effective in certain cases, its clinical application is limited by technical complexity and patient requirements. Furthermore, artificial intelligence, especially deep learning, holds promising potential for improving the accuracy of BA diagnosis.
More Related Videos
 07:44
Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
 06:15
Protocol and Guidelines for Point-of-Care Lung Ultrasound in Diagnosing Neonatal Pulmonary Diseases Based on International Expert Consensus
Published on: March 6, 2019
