Related Experiment Video
Updated: Sep 10, 2025

Cell-based Assay Protocol for the Prognostic Prediction of Idiopathic Scoliosis Using Cellular Dielectric Spectroscopy
Published on: October 16, 2013
How Can We Predict Dominant Compensatory Curves in Congenital Scoliosis?
Myung-Jin Cha1, William ElNemer, Paul D Sponseller
1Department of Orthopaedic Surgery, Division of Pediatrics, The Johns Hopkins University School of Medicine, Baltimore, MD.

Background:
Patients with congenital scoliosis may develop a large, unbalancing "compensatory" curve as they grow, which can be severely deforming. It is important to identify characteristics of patients who develop a "dominant" compensatory curve (one that is larger than the congenital curve) to help identify patients who may benefit from prophylactic treatment.
Methods:
By searching the Pediatric Spine Study Group database, we identified 307 patients 18 years and above with congenital scoliosis who had preoperative radiographs taken during at least 2 years of natural growth (period of no bracing or surgery). Seventeen patients (6%) had a dominant compensatory curve, and 290 had no compensatory curve or one that was smaller than the congenital curve. Of those 290 patients, 100 were randomly selected to serve as a control group, which we refer to as the "nondominant curve group." We analyzed the type of congenital anomaly and its vertebral level, as well as the major curve angles of the congenital and compensatory curves at initial and latest follow-up. We compared vertebral level and type of anomaly between groups using χ 2 tests. Alpha = 0.05.
Results:
The congenital anomaly was at L4 or more caudal in 18% of patients in the dominant curve group and no patients in the nondominant curve group ( P <0.001). Similarly, the congenital anomaly was at T6 or more cranial in 59% of patients in the dominant curve group and 28% of patients in the nondominant curve group ( P <0.001). At the latest follow-up, the dominant curve group had a mean (and SD) congenital curve of 55±19 degrees and a compensatory curve of 73±24 degrees. The frequencies of wedge, hemivertebrae, and bar vertebral anomalies did not differ between groups.
Conclusions:
In pediatric patients with congenital scoliosis, a dominant compensatory curve was associated with vertebral anomaly at L4 or caudal, or T6 or cranial. These findings can help clinicians prioritize prophylactic treatment for patients who may be at high risk for developing a dominant compensatory curve.
Level Of Evidence:
Level III.


Related Concept Videos
 01:16
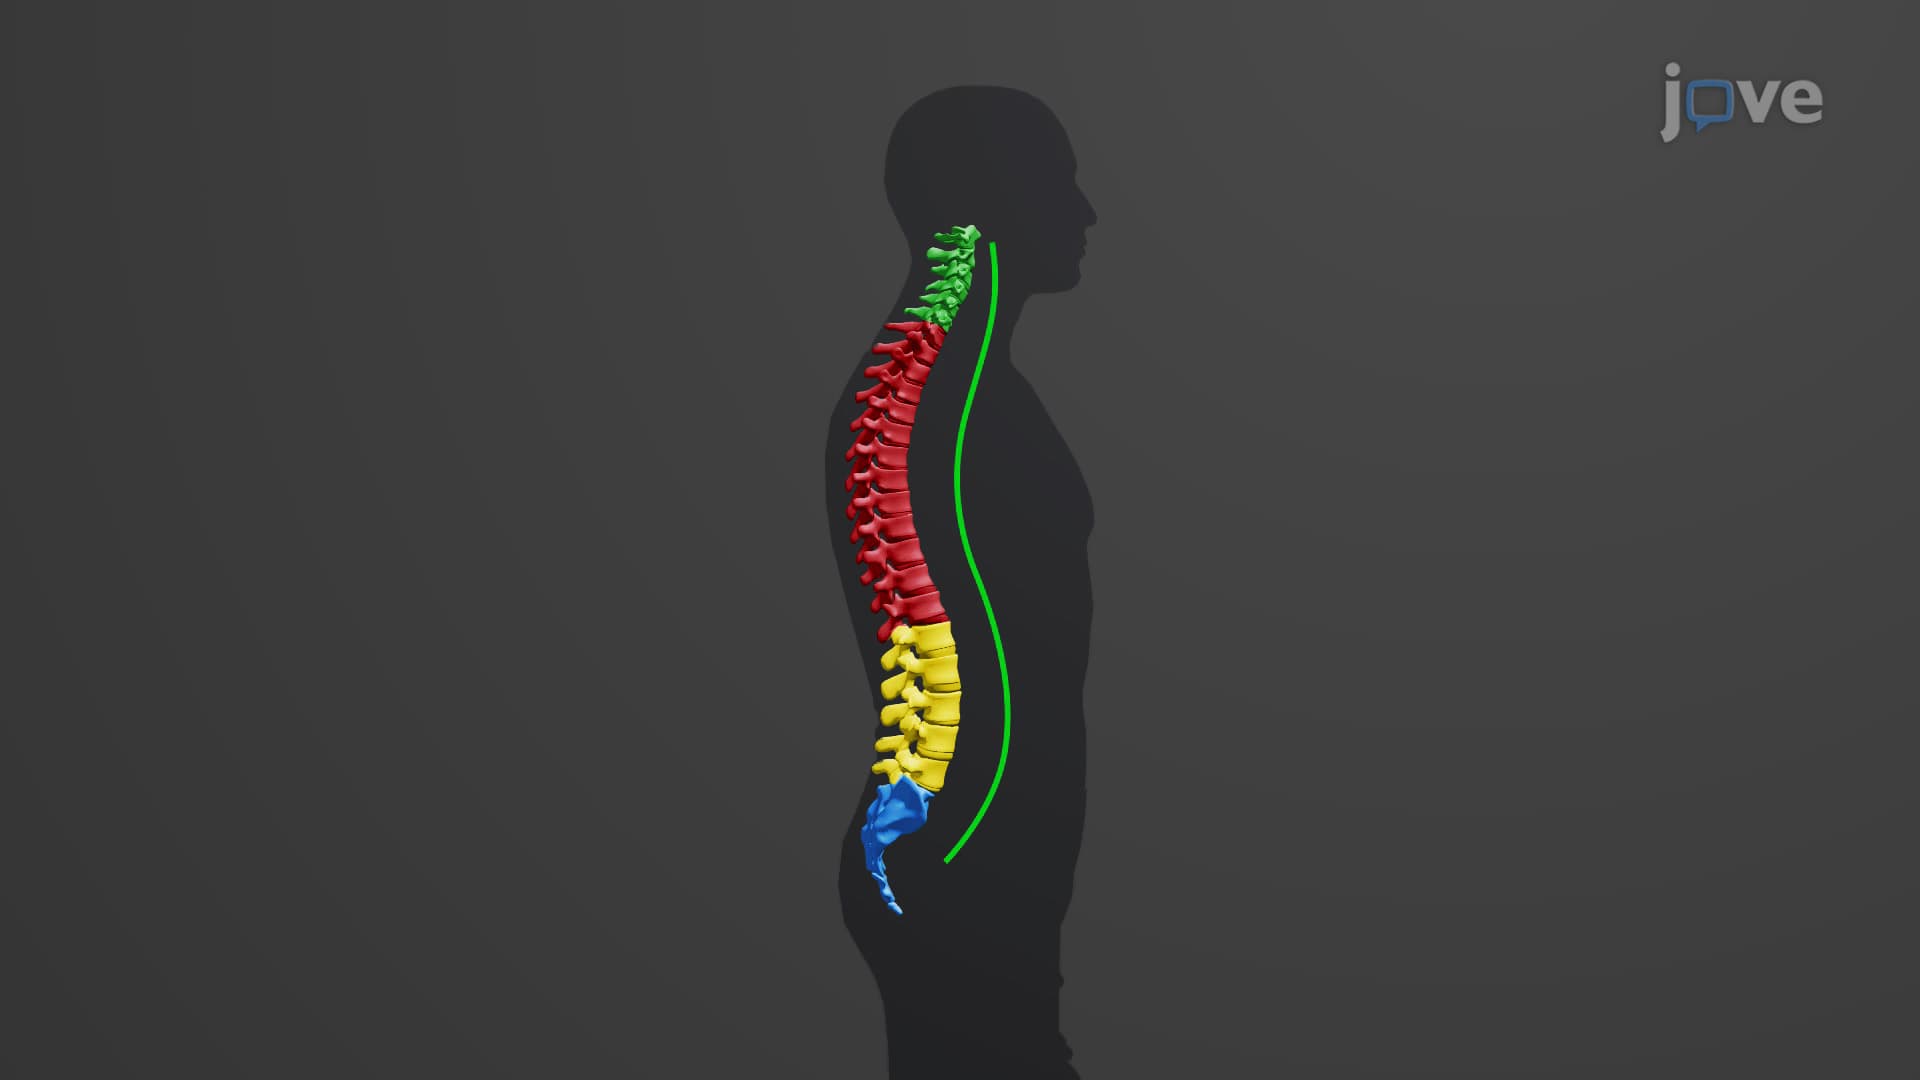
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:16
Elastic Curve from the Load Distribution
For all beams, the analysis of the beam's reaction to distributed loads begins by understanding the relationship between a beam's load and the resulting shear forces and bending moments.
 01:14
Bending of Curved Members - Strain Analysis
The important part of bending analysis for such a member...
 01:23
Equation of the Elastic Curve
Consider a cantilever beam with a point load at its free end (for instance, a diving board). When analyzing beam deflection with small slopes, the shape of the beam's elastic curve becomes key. The governing equation for this analysis involves the bending moment and the beam's flexural...
 01:16
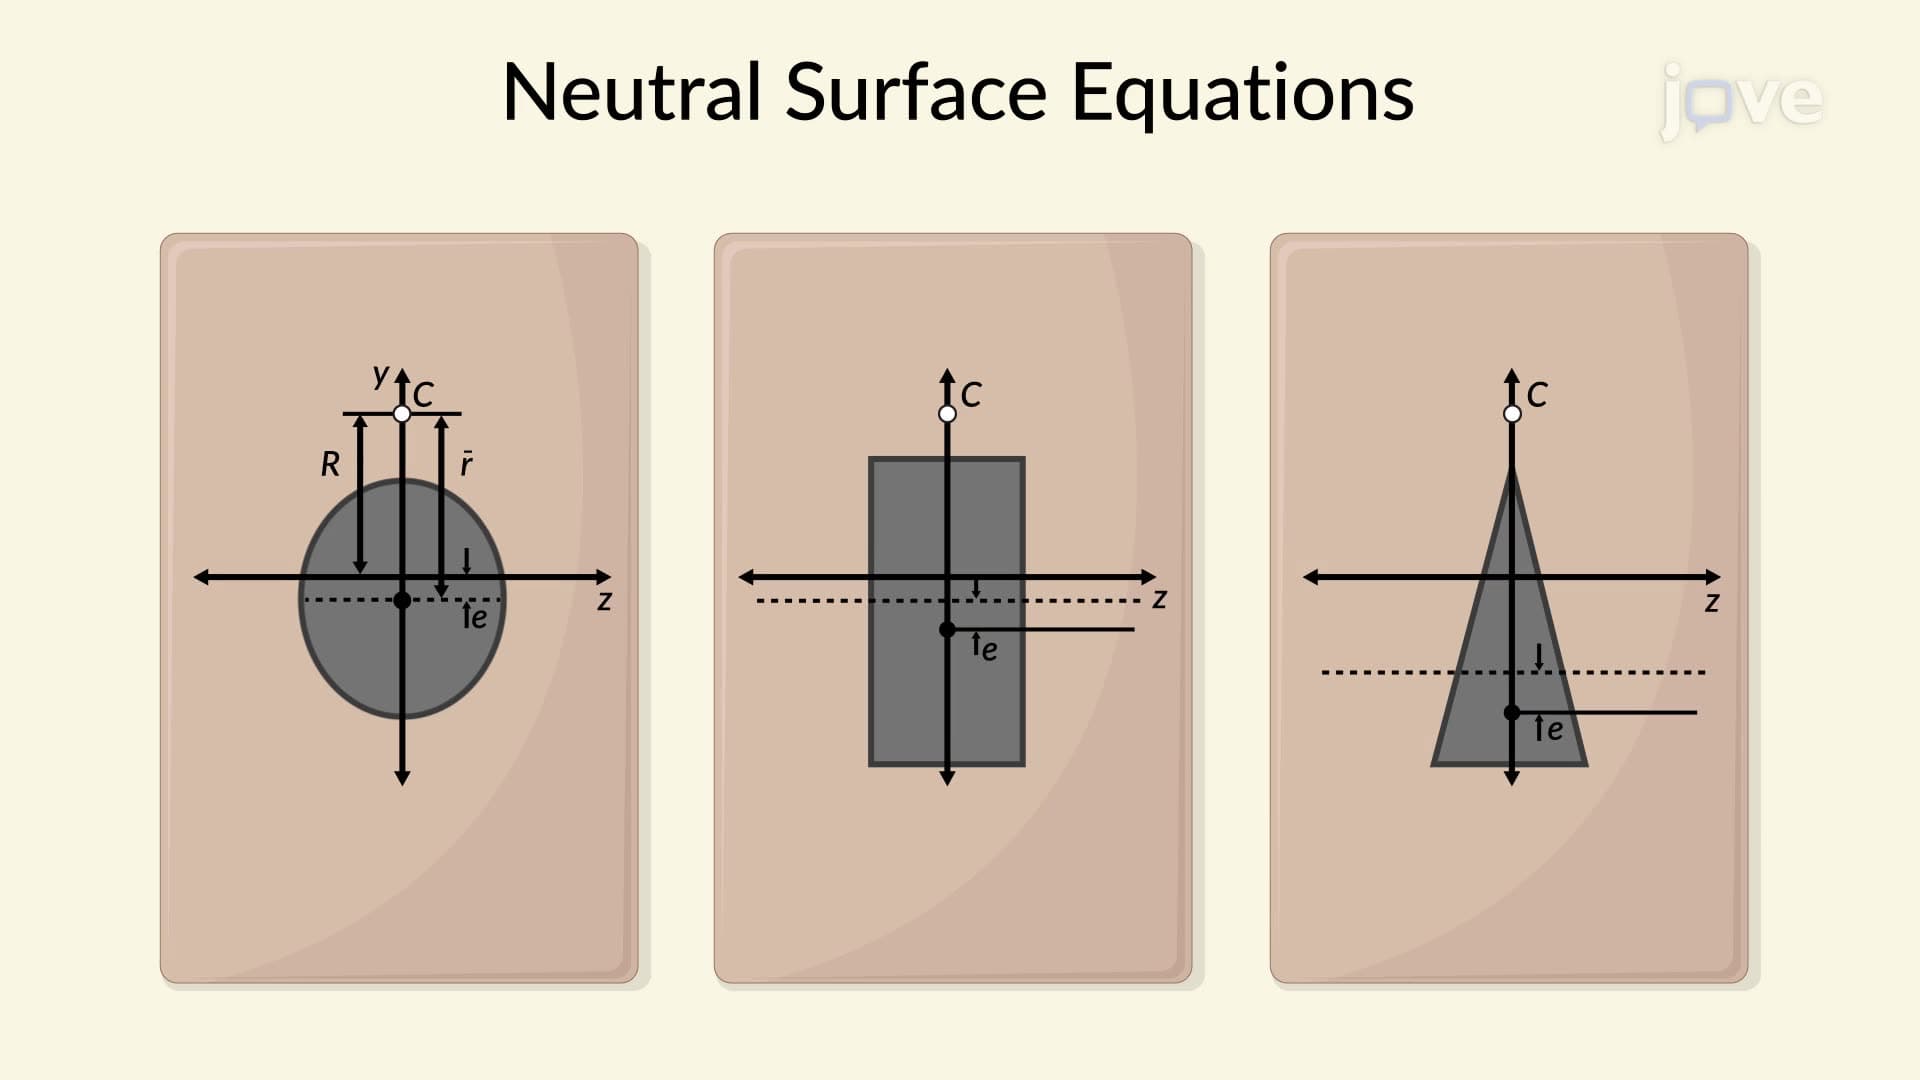
Bending of Curved Members - Neutral Surface
Consider the curved member described in the previous lesson. According to Hooke's law, which relates stress to strain within...
 01:12
General Case of Eccentric Axial Loading
Consider a member subjected to equal and opposite forces that are applied along a line that does not coincide with the member's neutral axis. In unsymmetrical...