Related Experiment Video
Updated: Sep 10, 2025
Treatment of Ankle Osteoarthritis with Total Ankle Replacement Through a Lateral Transfibular Approach
Published on: January 24, 2018
Use of bony landmarks for more accurate tibiofibular syndesmotic fixation: Validity and safety analysis of the angle
Bedri Karaismailoglu1, Julian J Hollander2, Jiyong Ahn3
1Foot & Ankle Research and Innovation Lab (FARIL), Department of Orthopaedic Surgery, Massachusetts General Hospital, Harvard Medical School, Boston, MA, United States; Department of Orthopaedics and Traumatology, Istanbul University-Cerrahpasa, Istanbul, Turkey; CAST (Cerrahpasa Research, Simulation and Design Laboratory), Istanbul University-Cerrahpasa, Istanbul, Turkey.

Background And Aims:
The Angle Bisector Method uses the cortices of the tibia and fibula as reference points and suggests a syndesmotic fixation trajectory through the bisector of the angle formed by two lines tangent to the anterior and posterior aspects of the tibia and fibula. This study aimed to assess whether the Angle Bisector Method can provide a patient- and level-specific syndesmotic fixation angle that is reproducible, safe, and independent of the surgeon in a cadaveric setting.
Methods:
Twelve matched above-knee leg specimens from six cadavers, underwent syndesmotic fixation (using either screws or suture-buttons) at two levels-2 cm and 3.5 cm proximal to the tibial plafond. The fixations were carried out using the angle bisector method by two surgeons employing an open lateral approach. Subsequently, CT images of the cadavers were obtained. The angle between the true centroidal axis and the axis of the syndesmotic implant trajectory was measured using radiological software. Additionally, distances between fibular entry points of the centroidal axis and the implant trajectory were measured. Distances between the positioned K-wires and major neurovascular structures were measured on cadaver dissections, and any resultant damage was documented.
Results:
The average angle between the centroidal axis and screw trajectory was 2.7 ± 2.9 degrees at the 2 cm level and 1.8 ± 2.5 degrees at the 3.5 cm level. The average distance between the fibular entry points of the centroidal axis and the screw was 1.7 ± 1.2 mm at the 2 cm level and 1.2 ± 1.0 mm at the 3.5 cm level. The results demonstrated low inter-surgeon variability and high intra- and inter-observer reliability (ICC>0.80). The distance between the placed K-wires and major neurovascular structures was always higher than 5 mm, affirming the safety of the technique.
Conclusion:
Our data suggests that the angle bisector method can provide a reliable trajectory for syndesmotic fixation and may be safely used in surgical procedures. This approach can be applied with K-wires or a specially designed jig to facilitate syndesmotic fixation.
More Related Videos
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
 05:34
A Mini-Invasive Internal Fixation Technique for Studying Immobilization-Induced Knee Flexion Contracture in Rats
Published on: May 20, 2019
Related Concept Videos
 01:10
Bones of the Lower Limb: Tibia and Fibula
 01:12
Adjusting a Traverse
 01:16
Bones of the Lower Limb: Femur and Patella
 01:10
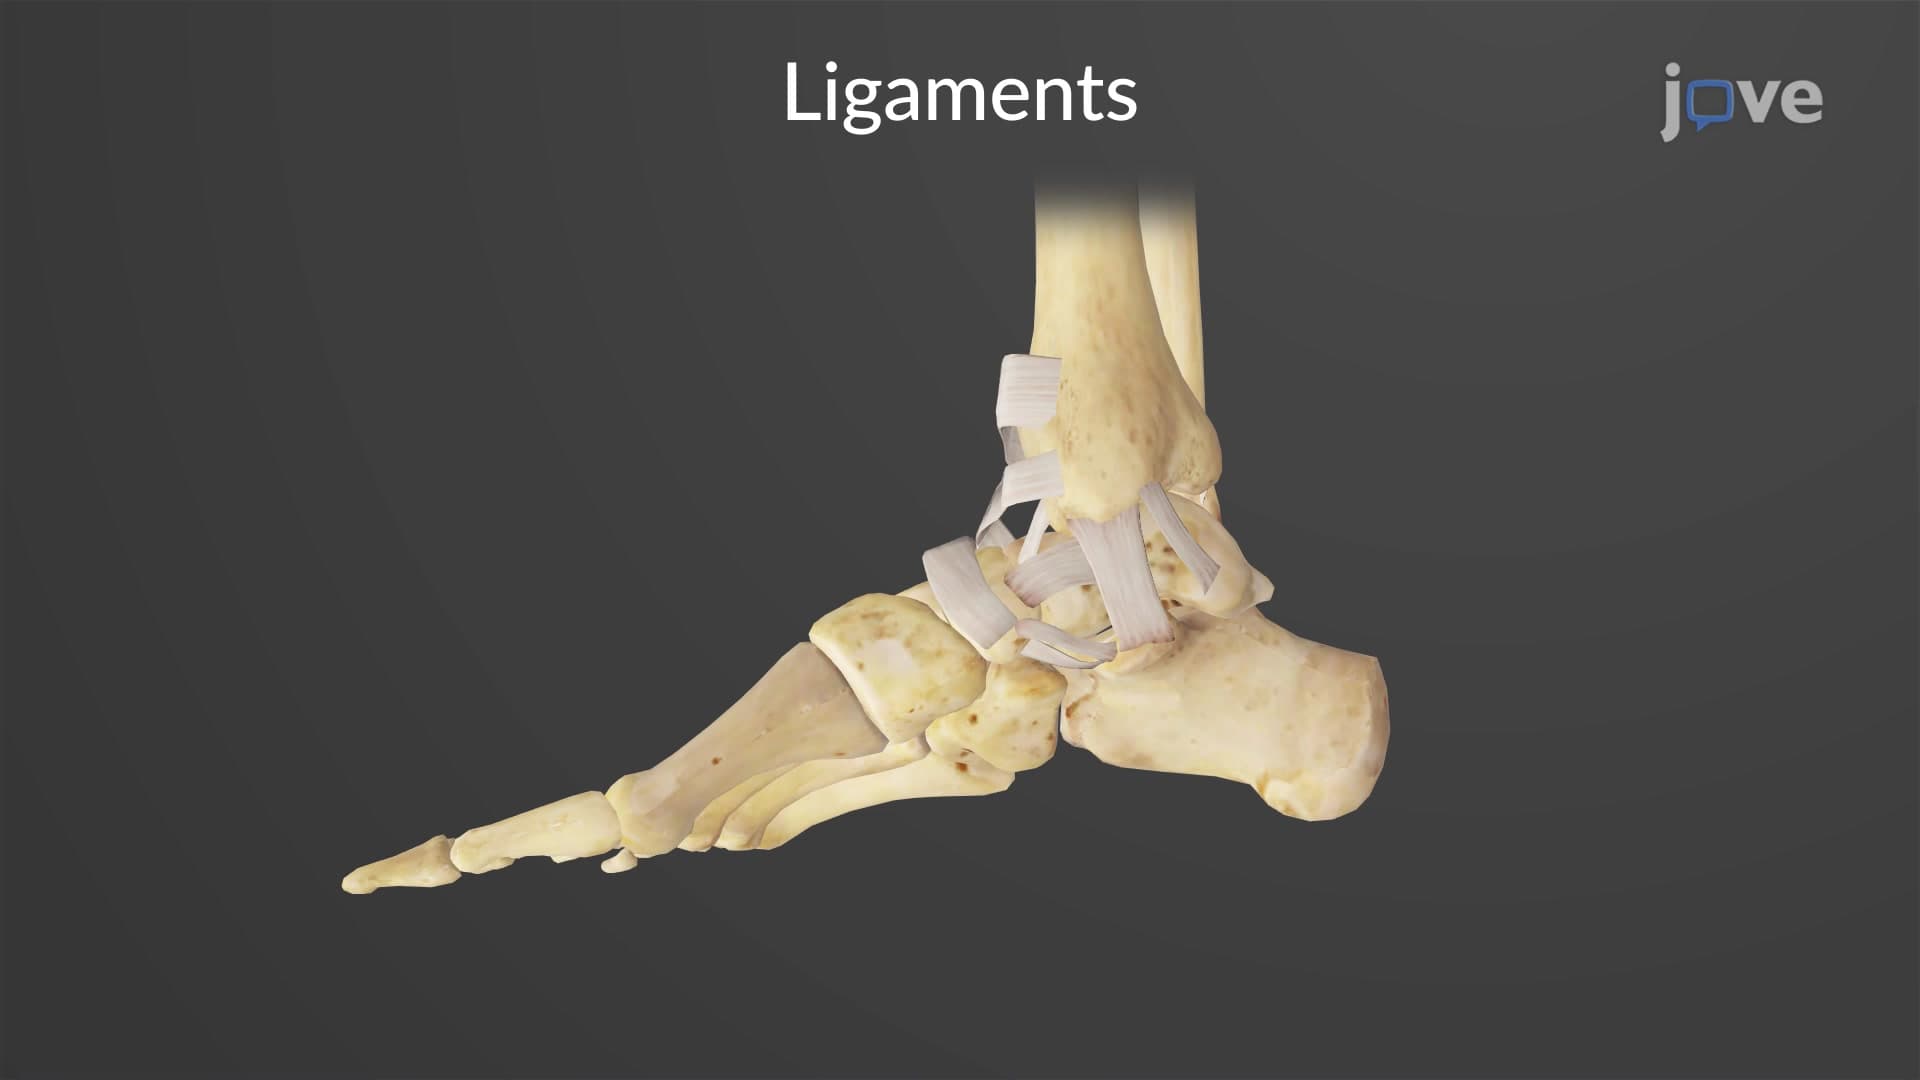
Ankle Joint