Related Experiment Video
Updated: Sep 10, 2025
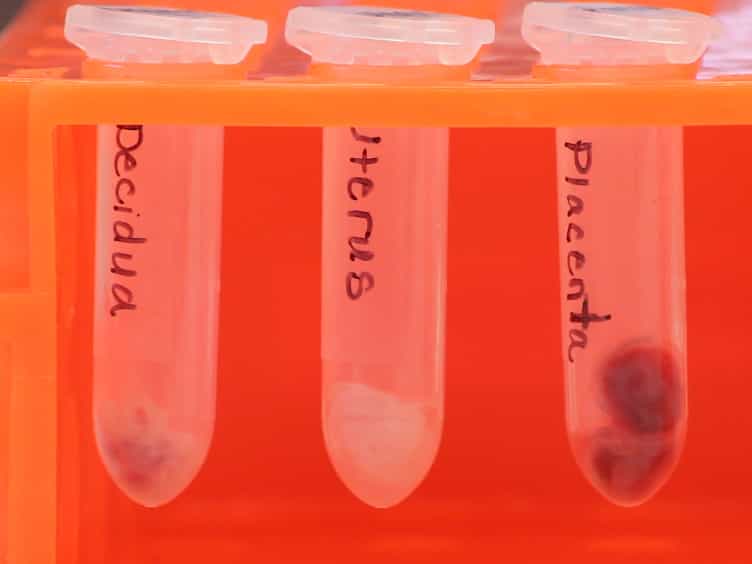

Isolation of Leukocytes from the Murine Tissues at the Maternal-Fetal Interface
Published on: May 21, 2015
Maternal-Foetal HLA-DQB1 Incompatibility Is Associated With Pregnancy-Induced Hypertensive Disorders in a Genetically
Liseanne J Van't Hof1, Marie-Louise P van der Hoorn2, Selena Migdis2
1Department of Immunology, Leiden University Medical Center, Leiden, the Netherlands.

In pregnancy, semi-allogenic foetal trophoblasts express a specific HLA profile mediating maternal leukocyte contact, crucial for placentation. Paradoxically, maternal immunomodulation requires foetal antigen recognition, especially involving certain HLA molecules. Pre-eclampsia, a severe hypertensive complication, has been linked to antigenic similarity. Previously, we showed no selection for HLA (in)compatibility in uncomplicated naturally conceived pregnancies. However, pre-eclamptic pregnancies were associated with increased total maternal-foetal HLA and HLA-C matching. These associations suggest a role for HLA mismatches in immune regulation leading to an uncomplicated pregnancy. To better understand HLA homozygosity in human reproduction, we aimed to determine if there is a preferential selection for HLA compatibility in a genetically isolated population, and its relation to hypertensive complications. A nested case-control study, comprising 125 uncomplicated pregnancies and 50 with hypertensive complications (29 with pregnancy-induced hypertension, 21 with pre-eclampsia) was conducted in a genetically isolated Dutch population (FROH 1.3-3.1). Maternal and foetal HLA-A, -B, -C, -DRB1, -DQA1, -DQB1 and maternal killer-cell immunoglobulin-like receptor (KIR) genotyping were performed. Maternal-foetal HLA (mis)match counts were compared to expected values from randomisation of paternal HLA haplotypes over maternal haplotypes of the foetuses. Mismatched CD4+ T cell epitopes presented by maternal HLA class II were predicted using the PIRCHE-II algorithm. In uncomplicated pregnancies, no difference was found between observed and expected maternal-foetal HLA (mis)matches. However, pregnancies with hypertensive complications showed significantly higher observed HLA-DQB1 mismatches, reflected in PIRCHE-II scores. No significant differences were found in KIR/HLA-C frequencies. Interpretation is limited by the small sample size and the grouping of distinct hypertensive disorders. Nonetheless, maternal-foetal HLA-DQB1 mismatch seems to play a role in the aetiology of hypertensive complications during pregnancy in this population.
In pregnancy, semi-allogenic foetal trophoblasts express a specific HLA profile mediating maternal leukocyte contact, crucial for placentation. Paradoxically, maternal immunomodulation requires foetal antigen recognition, especially involving certain HLA molecules. Pre-eclampsia, a severe hypertensive complication, has been linked to antigenic similarity. Previously, we showed no selection for HLA (in)compatibility in uncomplicated naturally conceived pregnancies. However, pre-eclamptic pregnancies were associated with increased total maternal-foetal HLA and HLA-C matching. These associations suggest a role for HLA mismatches in immune regulation leading to an uncomplicated pregnancy. To better understand HLA homozygosity in human reproduction, we aimed to determine if there is a preferential selection for HLA compatibility in a genetically isolated population, and its relation to hypertensive complications. A nested case-control study, comprising 125 uncomplicated pregnancies and 50 with hypertensive complications (29 with pregnancy-induced hypertension, 21 with pre-eclampsia) was conducted in a genetically isolated Dutch population (FROH 1.3-3.1). Maternal and foetal HLA-A, -B, -C, -DRB1, -DQA1, -DQB1 and maternal killer-cell immunoglobulin-like receptor (KIR) genotyping were performed. Maternal-foetal HLA (mis)match counts were compared to expected values from randomisation of paternal HLA haplotypes over maternal haplotypes of the foetuses. Mismatched CD4+ T cell epitopes presented by maternal HLA class II were predicted using the PIRCHE-II algorithm. In uncomplicated pregnancies, no difference was found between observed and expected maternal-foetal HLA (mis)matches. However, pregnancies with hypertensive complications showed significantly higher observed HLA-DQB1 mismatches, reflected in PIRCHE-II scores. No significant differences were found in KIR/HLA-C frequencies. Interpretation is limited by the small sample size and the grouping of distinct hypertensive disorders. Nonetheless, maternal-foetal HLA-DQB1 mismatch seems to play a role in the aetiology of hypertensive complications during pregnancy in this population.


Related Concept Videos
 01:19
Rh Blood Group
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:07
Teratogenicity