Related Experiment Video
Updated: May 2, 2026


The Impact of Motor Task Conditions on Goal-Directed Arm Reaching Kinematics and Trunk Compensation in Chronic Stroke Survivors
Published on: May 2, 2021
A Generalized Risk-Adjusted Cost-Effectiveness Economic Model for Measuring the Value of Interventions That Delay
Jason Shafrin1, Jaehong Kim2, Jacob Fajnor2
1FTI Consulting, Los Angeles, CA, USA; University of Southern California, Los Angeles, CA, USA.

Objectives:
To quantify how incorporating patient risk preferences and severity adjustments affect the value of a hypothetical treatment for mobility impairments caused by neurological conditions.
Methods:
A 5-state Markov model was developed to measure the health economic value of a hypothetical treatment delaying the progression of mobility impairments by 30.7% versus standard of care for patients who were 45-year-old, minimally impaired, and had received a diagnosis of a neurological condition. A generalized and risk-adjusted cost-effectiveness (GRACE) model was implemented using relative risk aversion estimates from a US general population survey. Treatment value was measured as risk-aversion and severity-adjusted net monetary benefit (NMB), defined as (1) risk-adjusted health gains (generalized risk-adjusted quality-adjusted life-years [GRA-QALYs]) monetized by (2) risk-aversion and severity-adjusted willingness to pay less (3) incremental costs. Risk-neutral results (traditional cost-effectiveness analysis [TCEA]) were compared.
Results:
Incorporating risk preferences and disease severity increased the value of health benefits. Incremental health gains from using the hypothetical treatment (vs standard of care) were valued more when accounting for risk preferences with GRACE (1.358 GRA-QALYs vs 1.199 QALY). Willingness to pay for these health gains was higher when computed under GRACE compared with TCEA ($109 656 per GRA-QALY vs $100 000 per QALY). Overall, NMB increased by 11.6% (risk-aversion and severity-adjusted NMB = $278 324 vs TCEA NMB = $249 311) using GRACE versus TCEA. Results were sensitive to risk-aversion estimates and the functional form of patient utility.
Conclusions:
In the first application of GRACE within neurology, GRACE increased the health economic value of a hypothetical neurology treatment, suggesting that TCEA may undervalue treatments for mobility-related neurological impairments.


Related Concept Videos
 01:17
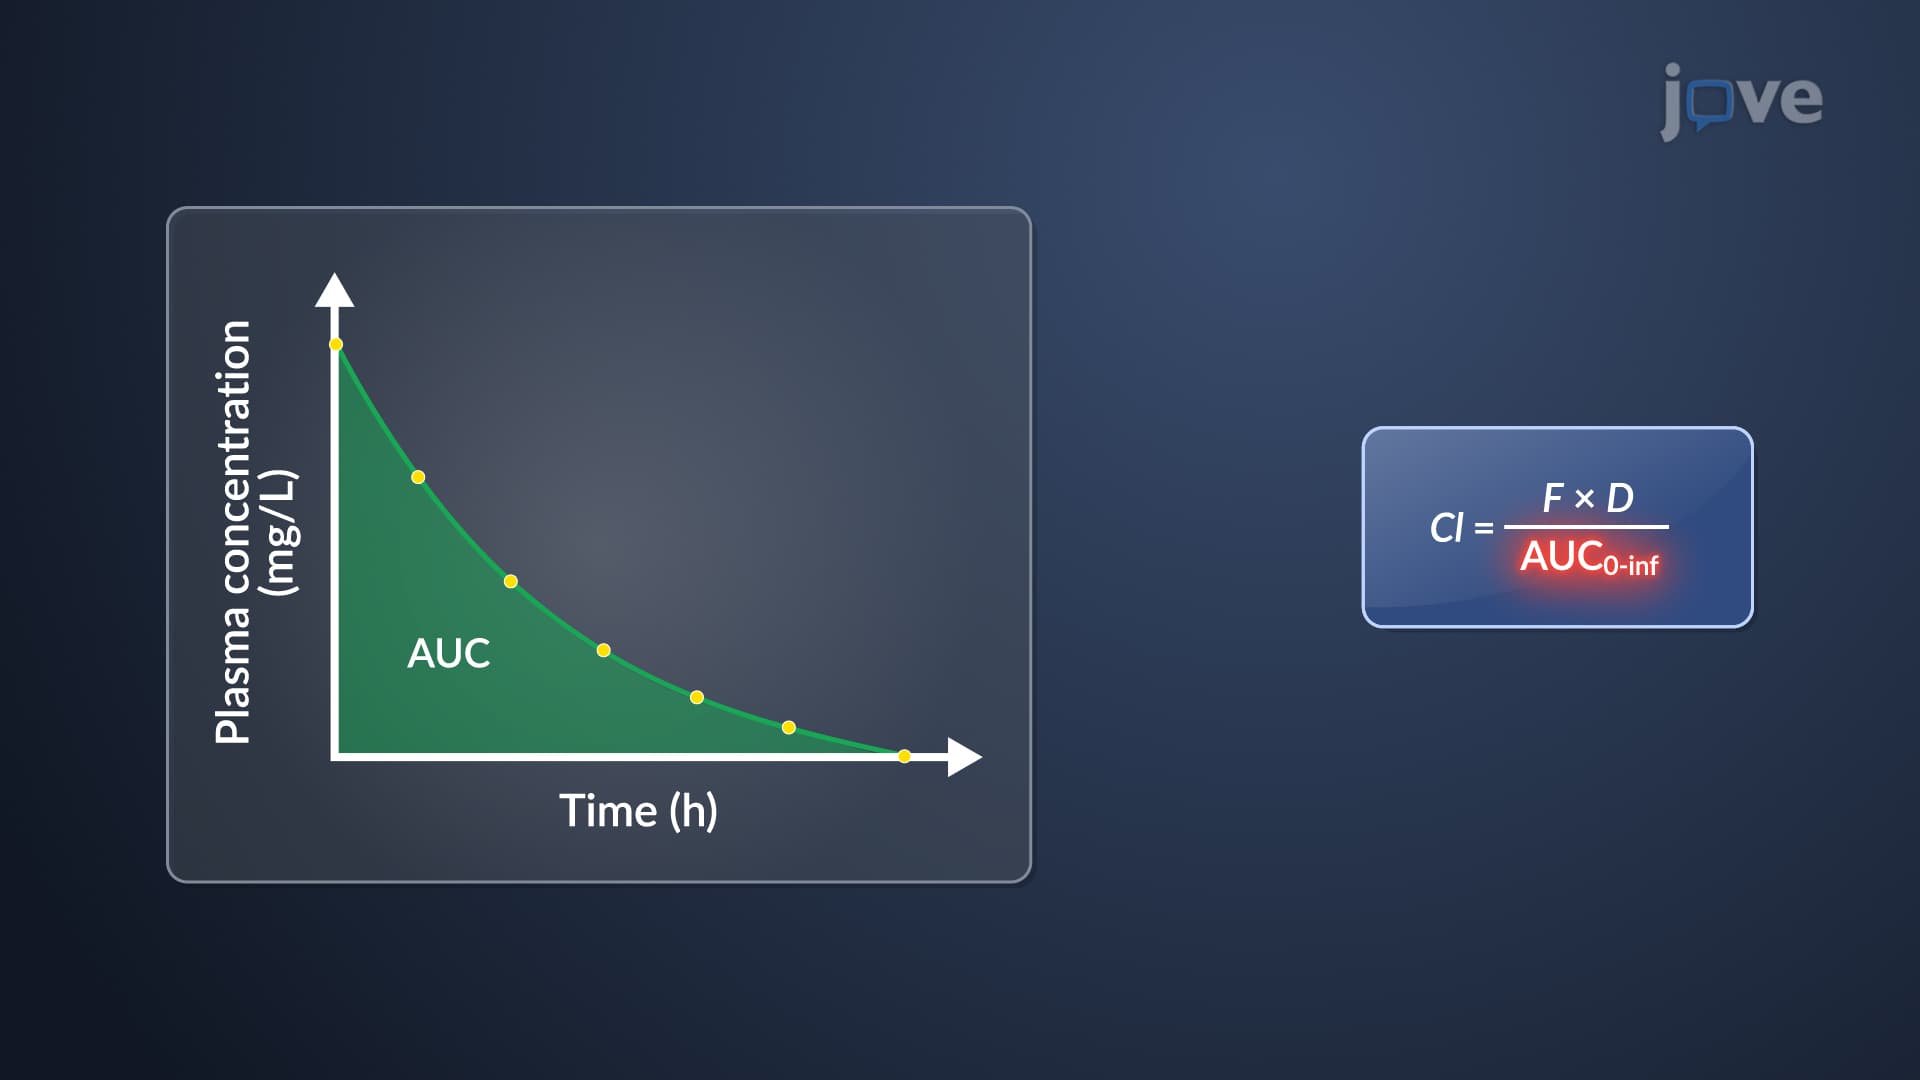
Clearance Models: Noncompartmental Models
The noncompartmental approach capitalizes on extensive sampling data, correlating the volume of distribution to systemic exposure and the administered dosage. This method enables...
 01:27
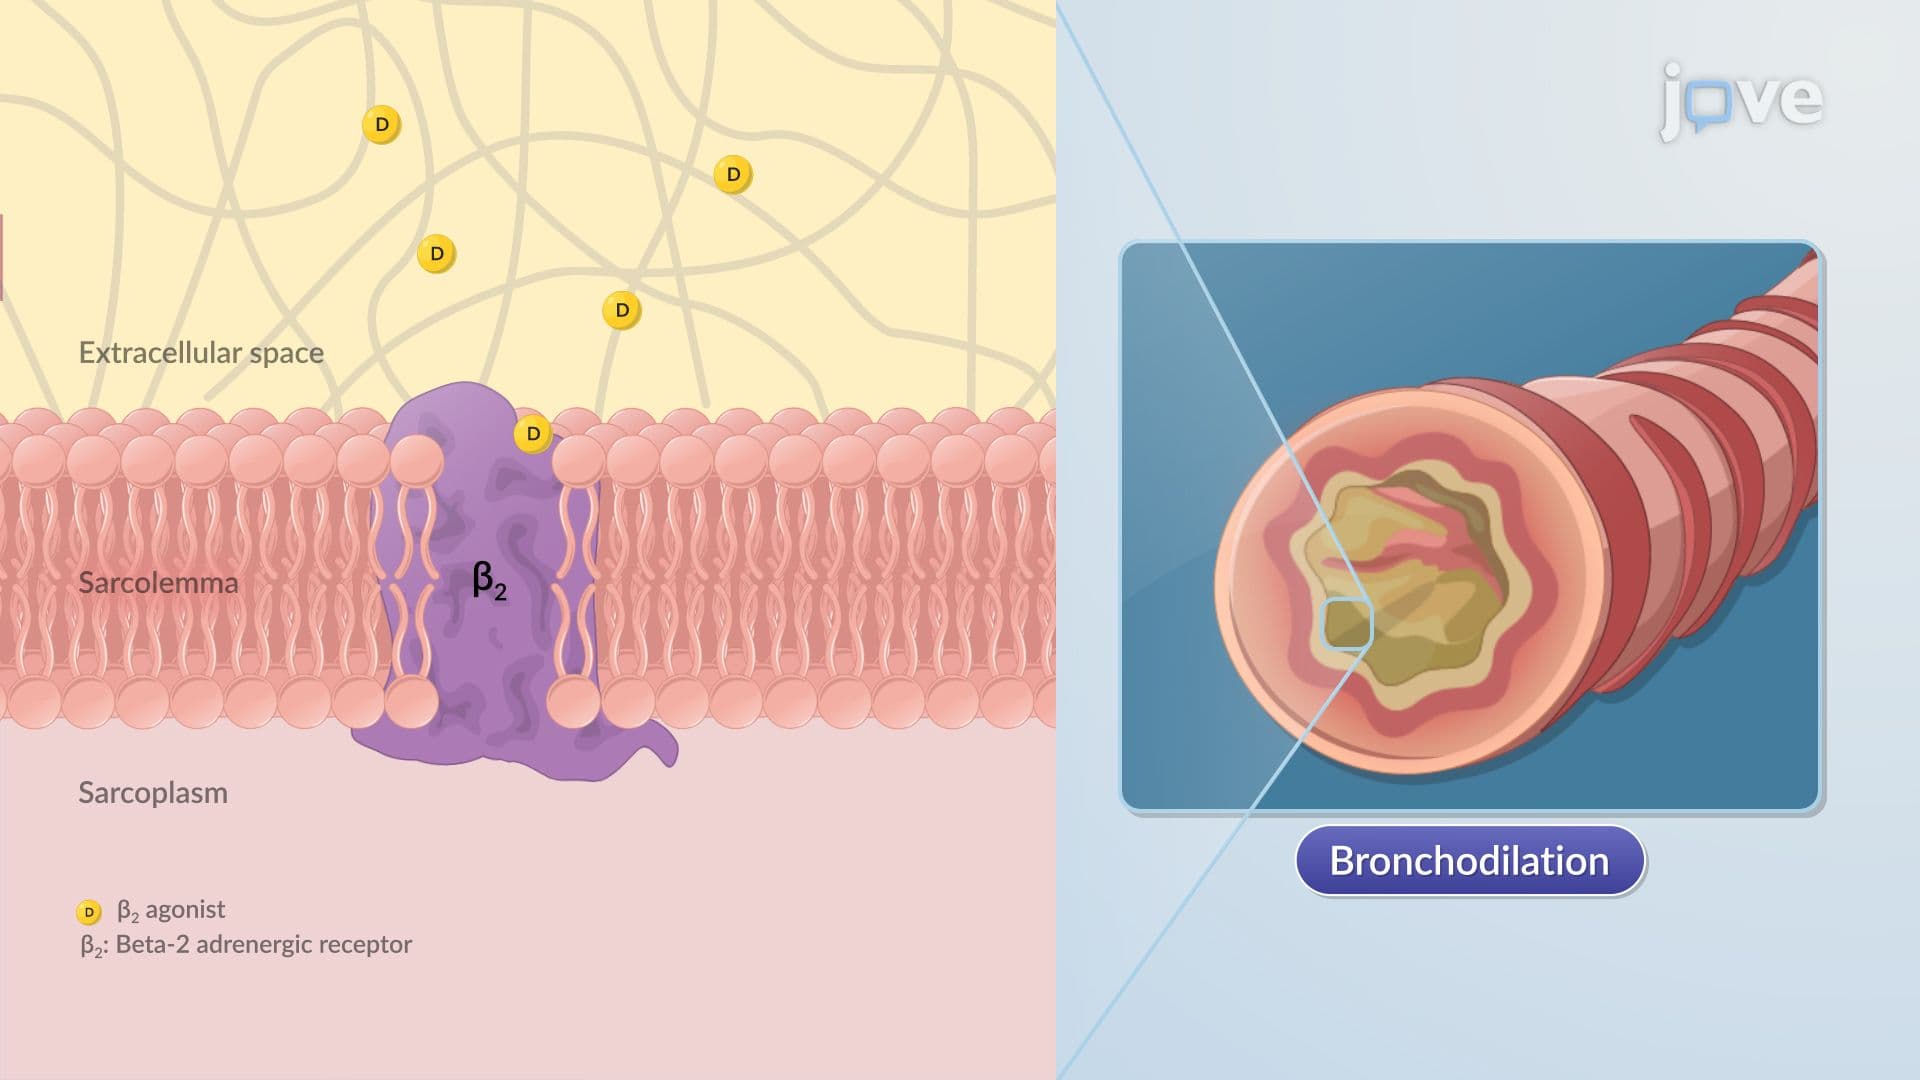
Pharmacodynamic Models: Overview
 01:12
Relative Risk
 01:20
Actuarial Approach
Consider the example of a high-risk surgical procedure with significant early-stage mortality. A two-year clinical study is conducted,...