Related Experiment Video
Updated: Apr 30, 2026

A Visual Description of the Dissection of the Cerebral Surface Vasculature and Associated Meninges and the Choroid Plexus from Rat Brain
Published on: November 14, 2012
Cocaine-Induced Midline Destructive Lesions-A Harbinger of Meningitis and Hydrocephalus
Siddharth Srinivasan1, Anna Craig-McQuaide1, Mustafa Elsheikh1
1Department of Neurosurgery, Institute of Neurological Sciences, Queen Elizabeth University Hospital, Glasgow, United Kingdom.

Abstract:
Cocaine is among the most commonly used recreational drugs in Scotland, contributing to significant socioeconomic and severe health challenges. The prevalence of cocaine-induced midline destructive lesions (CIMDL) is rising due to increased cocaine insufflation. Here, we report a case of a patient who developed acute hydrocephalus and meningitis as complications of CIMDL due to long-term cocaine abuse. A 39-year-old woman with a history of chronic nasal cocaine abuse presented with fever, malaise, and gait imbalance. On arrival at accident and emergency department, she had altered sensorium, Glasgow coma scale (GCS) of 10, and left-sided hemiparesis, requiring emergency intubation. Imaging revealed acute hydrocephalus and brain edema. She underwent an emergency external ventricular drain (EVD) to temporize her raised intracranial pressure. Her constellation of problems and biochemical parameters directed toward a diagnosis of acute bacterial meningitis. Her blood cultures grew methicillin-sensitive Staphylococcus aureus , and she was started on broad-spectrum antibiotics. Her computed tomography scans showed air in the sphenoid sinus, clival erosion, and partial erosion of the anterior arch of C1, consistent with CIMDL. She developed posterior circulation ischemic strokes, which were attributed to her endocarditis and tricuspid valve vegetations that were detected on her transthoracic echocardiogram. Eventually, she underwent a ventriculoperitoneal shunt for permanent cerebrospinal fluid diversion. Neurologically, she was E4V5M6 with residual left hemiparesis at the time of discharge. She is on aggressive rehabilitation under the care of oral maxillofacial surgery, otorhinolaryngology, and a skull base team for her CIMDL. This case highlights the importance of multidisciplinary care and support in managing such cases, especially aiming to prevent the recurrence of infection leading to significant morbidity or even mortality.

Related Concept Videos
 01:27
CNS Depressants: Alcohol and Nicotine
 01:24
Chronic Pancreatitis I: Introduction
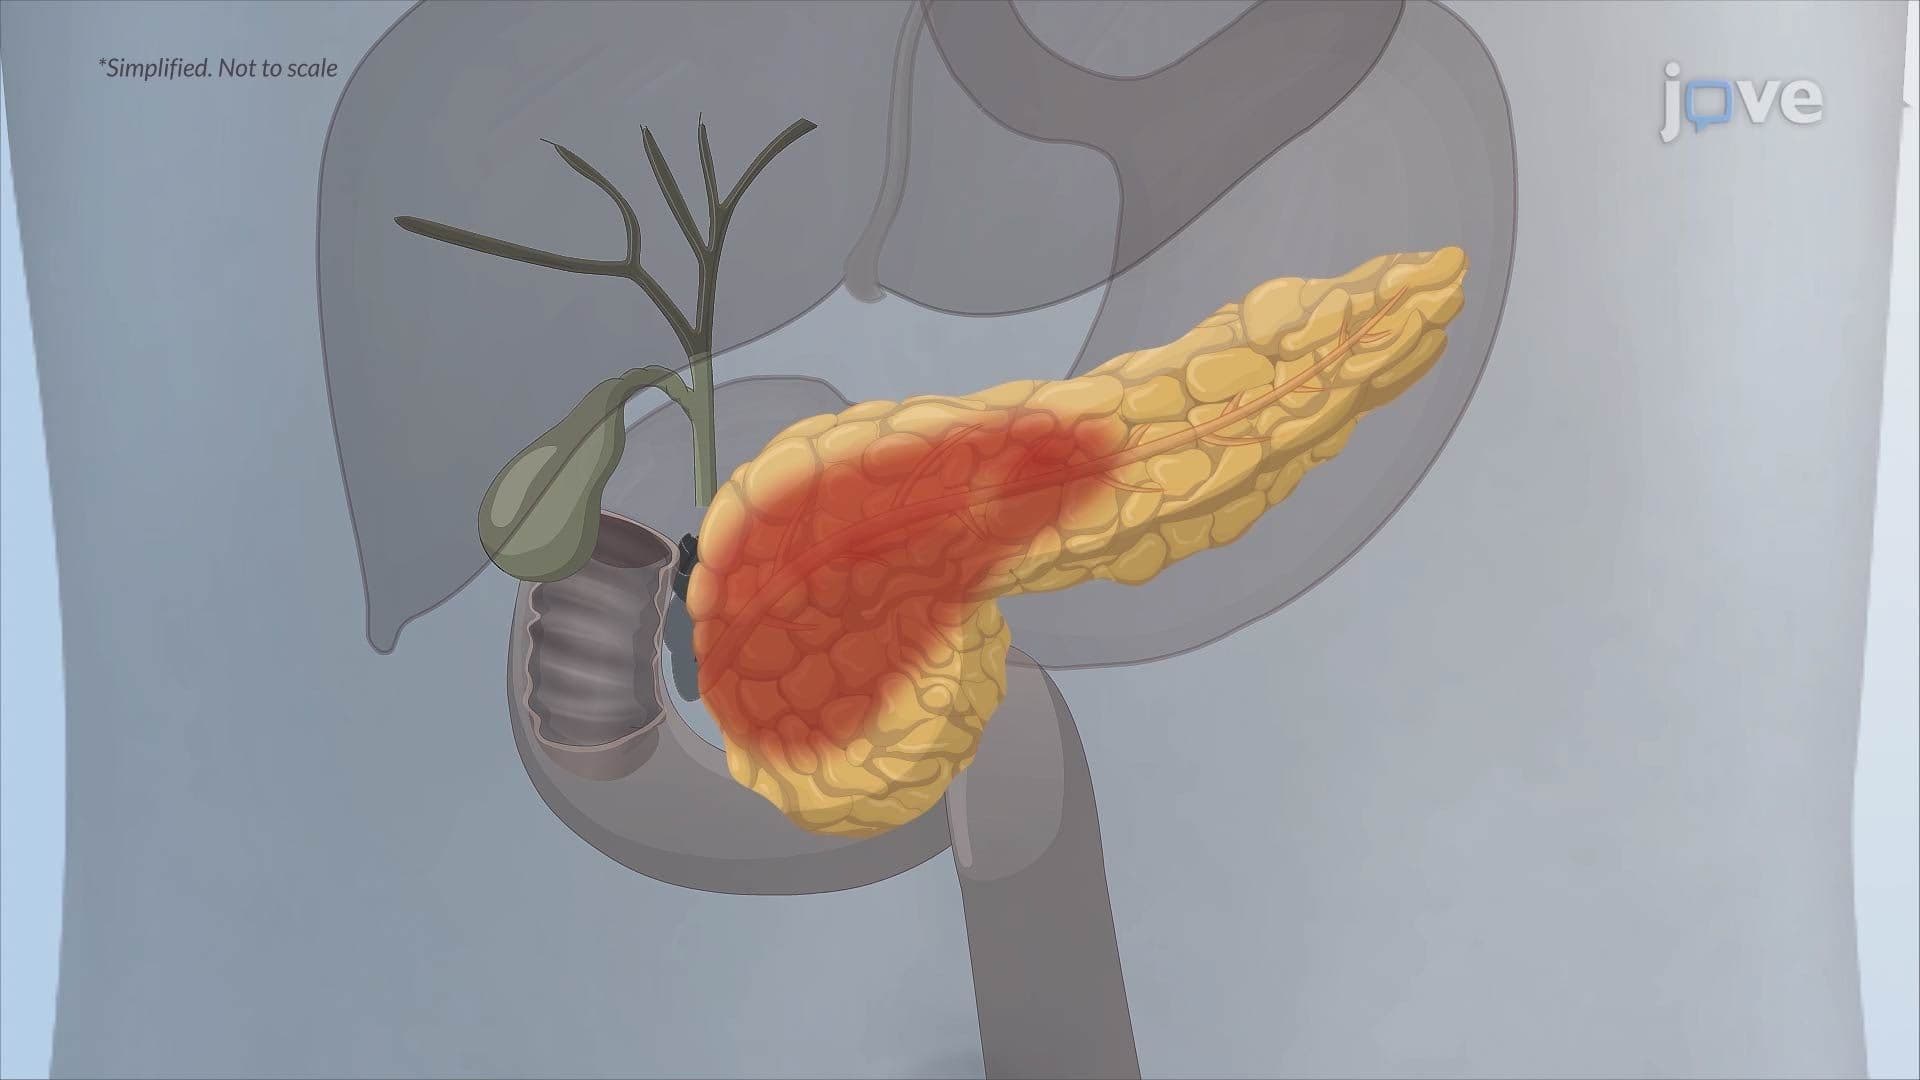
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:25
Chronic Pancreatitis I: Introduction
 01:21
Chronic Pancreatitis II: Pathophysiology