Related Experiment Video
Updated: May 8, 2026


Application of Granger Causality Analysis of the Directed Functional Connection in Alzheimer's Disease and Mild Cognitive Impairment
Published on: August 7, 2017
Greater White Matter Hyperintensities and More Severe Cognitive Dysfunction in Mild Cognitive Impairment With Motoric
Joon Hyuk Park1,2, Hyun Ju Yang1,3, Suyeon Park3
1Department of Psychiatry, Jeju National University School of Medicine, Jeju, Korea.

Background:
The motoric cognitive risk syndrome (MCRS) is characterized by slow gait and cognitive complaints. A motor-based approach to MCRS provides a clinical strategy for identifying individuals at high risk for dementia.
Methods:
This study included 81 outpatients with mild cognitive impairment (MCI). All participants underwent clinical evaluations, including volumetric brain magnetic resonance imaging (MRI) and neuropsychological testing with the Korean version of the Consortium to Establish a Registry for Alzheimer's Disease Assessment Packet. White matter hyperintensities (WMH) volume was calculated using automated segmentation analysis from three-dimensional MRI images. MCRS was defined by the presence of cognitive complaints and slow gait defined as gait speed at least one standard deviation below age- and sex-specific means.
Results:
A total of 31 subjects with MCRS and 50 subjects without slow gait participated in this study. The linear regression analysis revealed a significant negative relationship between WMH volume and gait speed in both the MCI group with MCRS (β = -1.010, P < 0.001) and the MCI group without slow gait (β = -0.427, P = 0.016). Both age (odds ratio [OR], 1.17; 95% confidence interval [CI], 1.02-1.34) and WMH volume (OR, 1.11; 95% CI, 1.01-1.22) were significantly associated with MCRS, even after adjusting for confounding factors. After applying Bonferroni correction (P < 0.0036), the MCRS group exhibited significantly worse performance on word list memory, word list recall, and MMSE-KC compared to the MCI group without slow gait.
Conclusion:
MCRS represents a distinct and more severe clinical entity within the MCI population, characterized by greater cognitive impairment and increased WMH burden.
Insights
Motoric Cognitive Risk Syndrome (MCRS) in mild cognitive impairment (MCI) patients is linked to increased white matter hyperintensities (WMH). Identifying MCRS aids in predicting dementia risk and understanding cognitive decline.
Area of Science:
- Neurology
- Geriatrics
- Neuroimaging
Background:
- Motoric Cognitive Risk Syndrome (MCRS) combines slow gait and cognitive complaints.
- A motor-based approach aids in identifying individuals at high risk for dementia.
Purpose of the Study:
- To investigate the relationship between white matter hyperintensities (WMH) and MCRS in patients with mild cognitive impairment (MCI).
- To determine if MCRS represents a distinct clinical entity within the MCI population.
Main Methods:
- 81 outpatients with MCI underwent clinical evaluations, volumetric brain MRI, and neuropsychological testing.
- White matter hyperintensities (WMH) volume was calculated using automated segmentation from 3D MRI images.
- MCRS was defined by cognitive complaints and gait speed at least one standard deviation below age- and sex-specific means.
Main Results:
- A significant negative relationship was found between WMH volume and gait speed in both MCRS and non-MCRS MCI groups.
- Age and WMH volume were significantly associated with MCRS after adjusting for confounders.
- MCRS patients showed significantly worse performance in memory and cognitive tests compared to MCI patients without slow gait.
Conclusions:
- MCRS is a distinct clinical entity within the MCI population.
- MCRS is characterized by greater cognitive impairment and increased WMH burden.
- This highlights the importance of motor function assessment in MCI for predicting cognitive decline.


Related Concept Videos
 01:30
Cognitive Enhancers: Cholinesterase Inhibitors and NMDA Receptor Antagonists
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:30
Dementia
The progression of dementia is generally gradual.
 01:29
Alzheimer Disease l: Introduction
 01:23
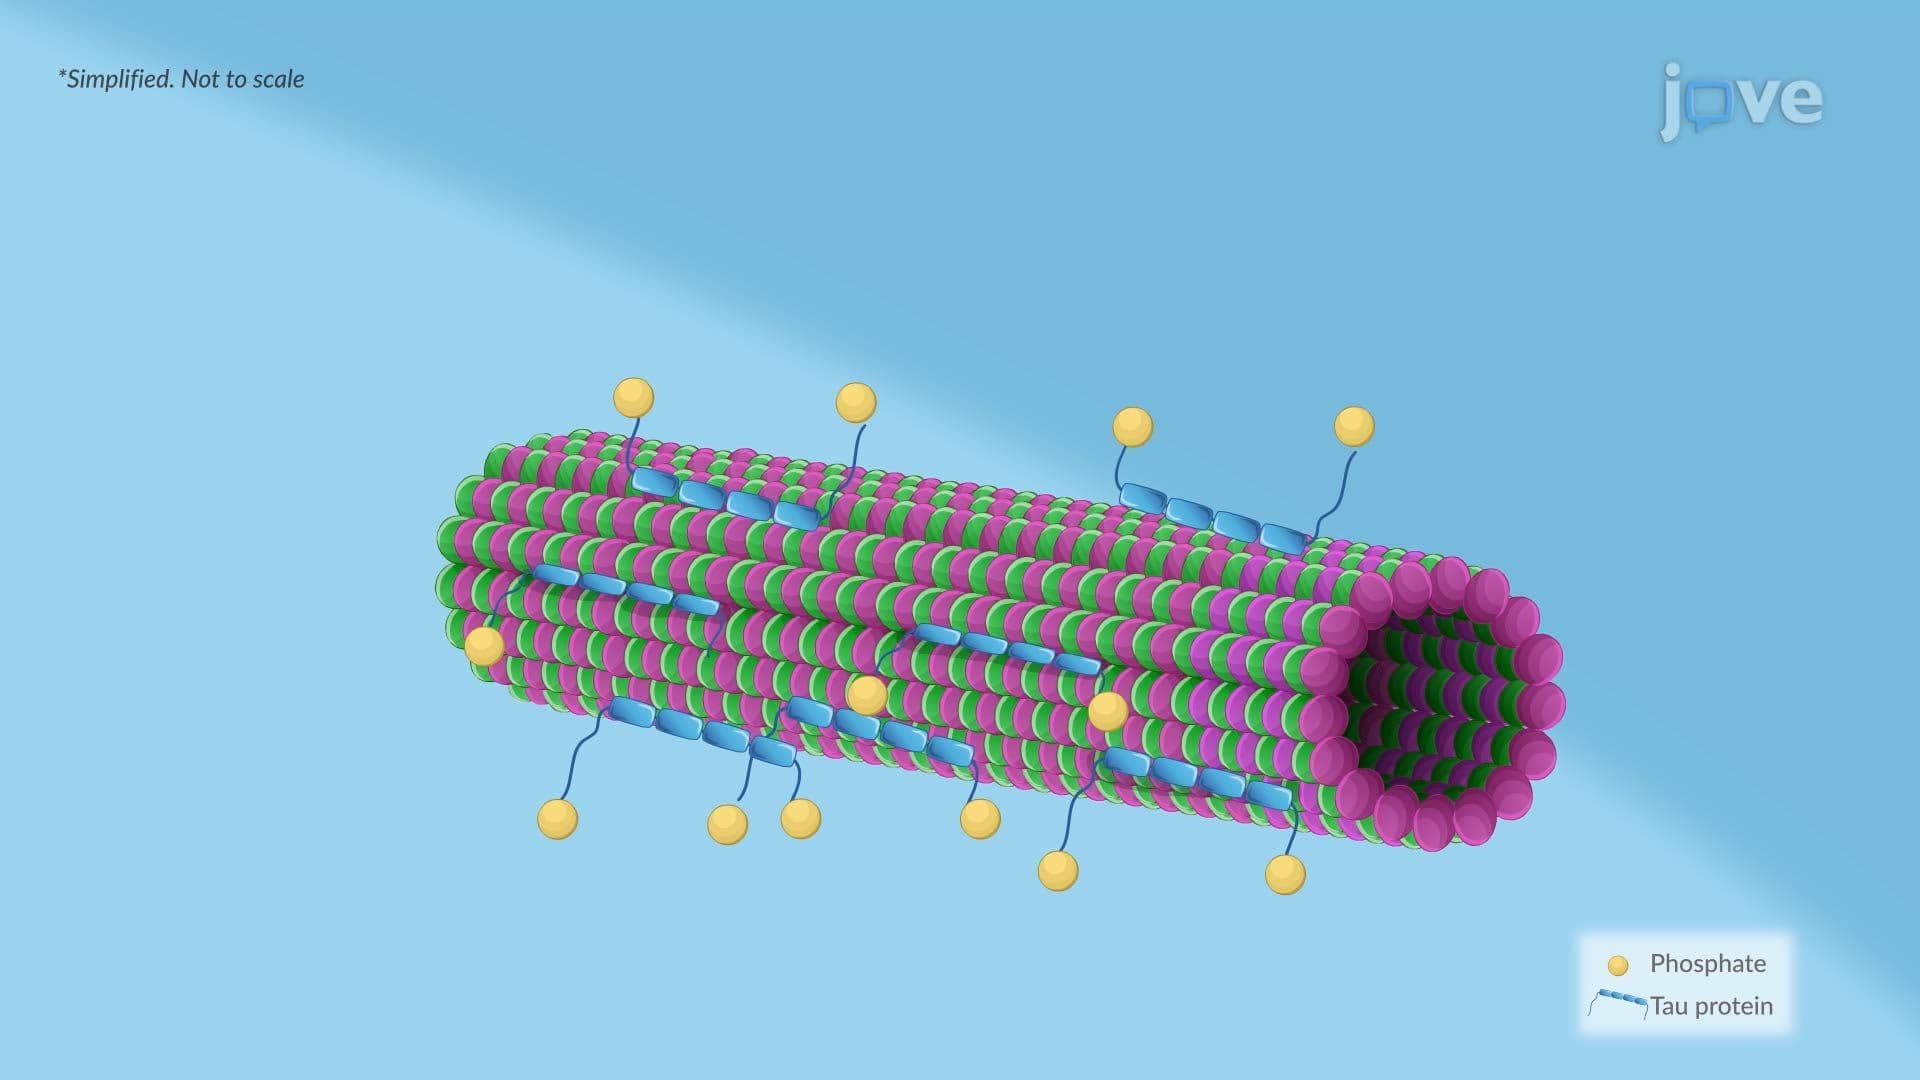
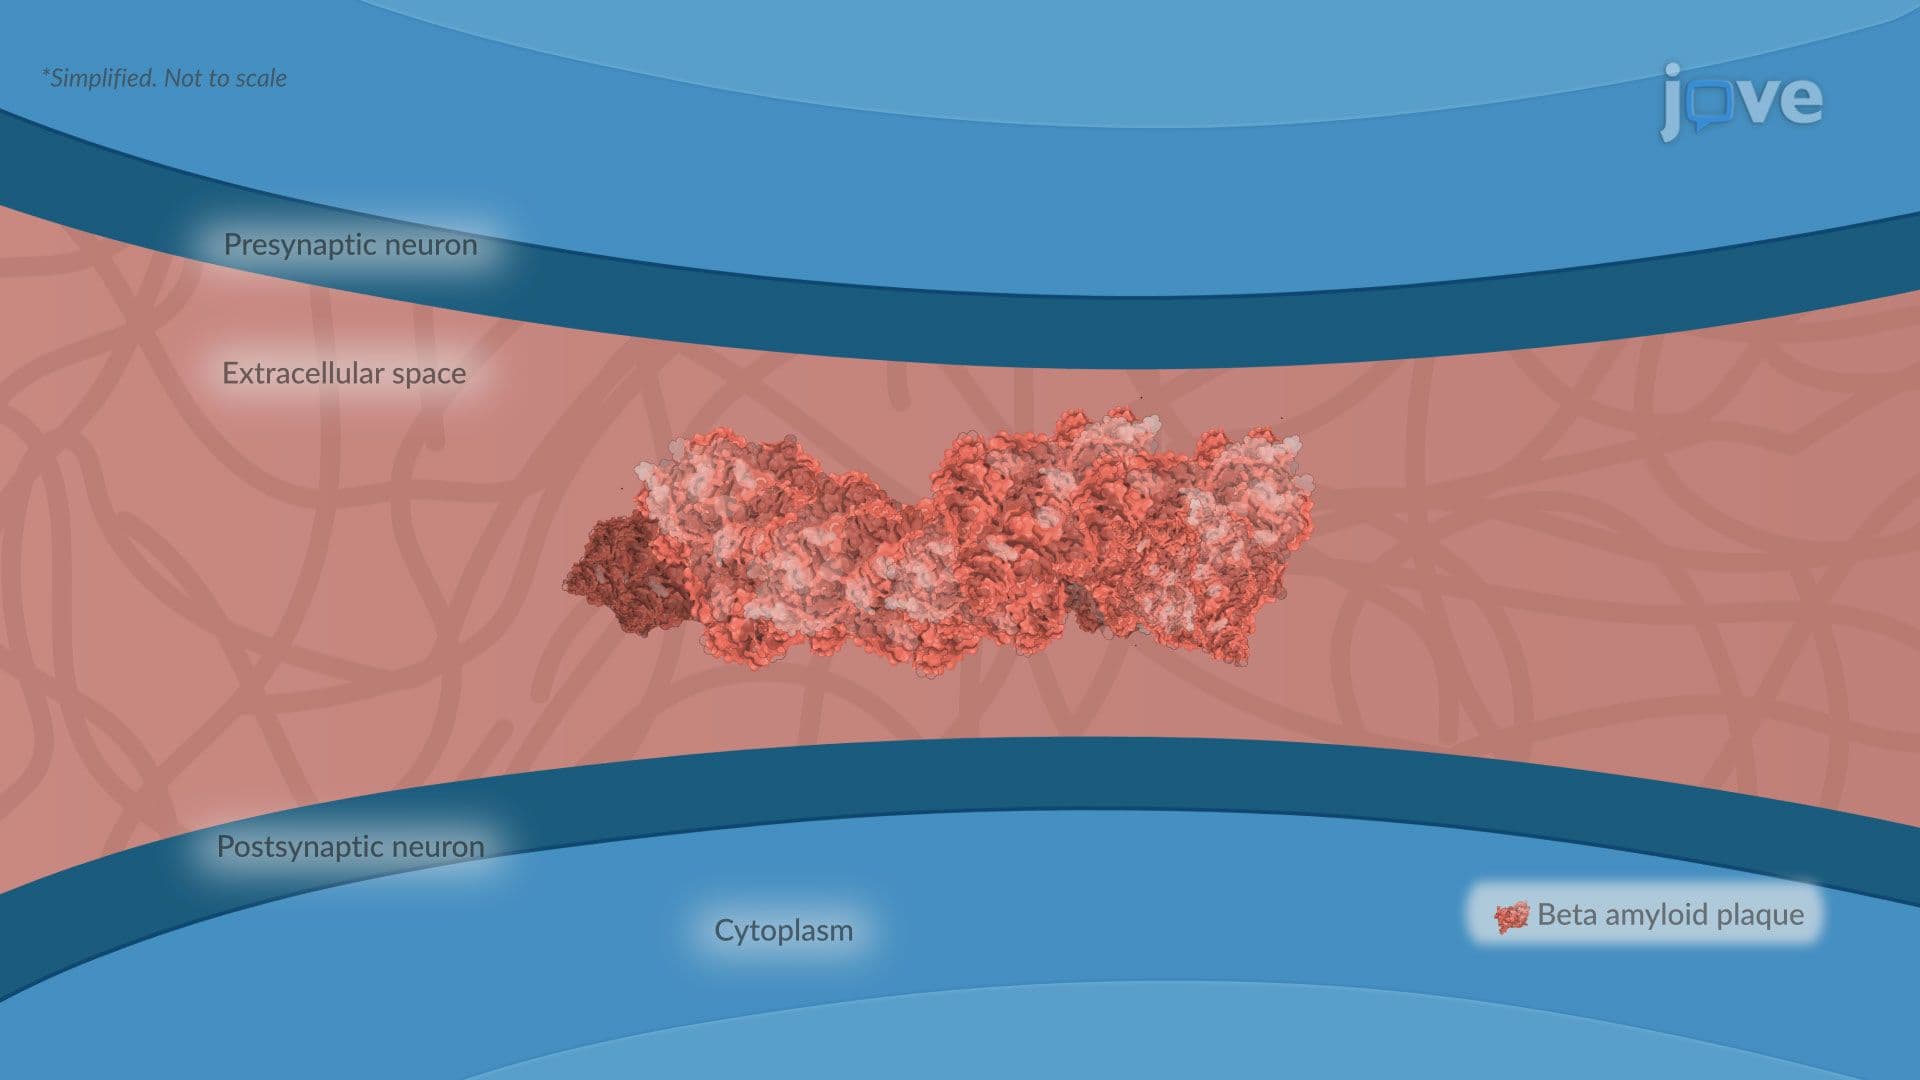
Alzheimer Disease ll: Pathophysiology
 01:22
Dementia l: Introduction