Related Experiment Video
Updated: Sep 10, 2025
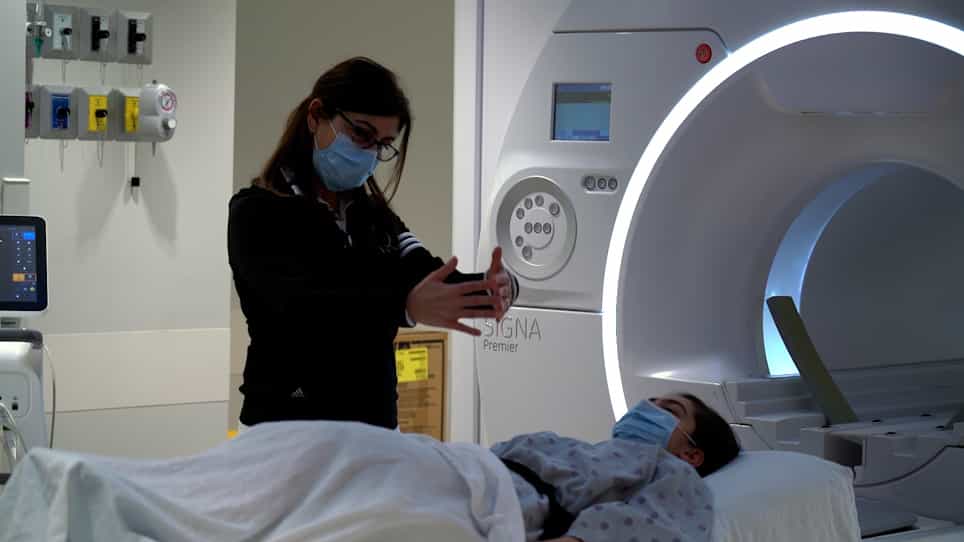

Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
Association of myocardial bridging with exercise-induced ischemia in patients without obstructive coronary artery
Takumi Toya1,2, Tsukasa Naganuma3, Yohsuke Suyama4
1Department of Cardiology, National Defense Medical College, Saitama, Japan. tyt0725@gmail.com.

Insights
Myocardial bridging (MB) is linked to positive exercise stress electrocardiograms (ECG), especially in patients with nonobstructive coronary artery disease (INOCA). Longer MB length correlates with greater ischemia severity in INOCA patients.
Area of Science:
- Cardiology
- Diagnostic Imaging
- Exercise Physiology
Background:
- Exercise stress electrocardiography (ECG) has limitations in diagnosing obstructive coronary artery disease (CAD).
- Myocardial bridging (MB), a condition causing coronary artery compression, is increasingly implicated in ischemia, particularly in patients with nonobstructive coronary arteries (INOCA).
Purpose of the Study:
- To investigate the association between myocardial bridging (MB) and positive exercise stress ECG results.
- To assess how MB's anatomical characteristics relate to the burden of myocardial ischemia.
Main Methods:
- Retrospective analysis of 197 patients undergoing exercise stress testing and coronary computed tomography angiography (CTCA).
- Identification and measurement of MB length and thickness on CTCA.
- Classification of exercise stress ECG results as positive or negative.
Main Results:
- Myocardial bridging (MB) was found in 32% of patients.
- Positive exercise stress ECG findings were significantly more common in patients with MB (66%) compared to those without (38%).
- Among INOCA patients with positive ECGs, MB prevalence was highest (62%). MB length was greater in INOCA patients with positive ECGs than in obstructive CAD patients with positive ECGs.
Conclusions:
- Myocardial bridging (MB) is independently associated with positive exercise stress ECG findings, suggesting its role in exercise-induced ischemia.
- MB may be a significant contributor to ischemia in patients with INOCA.
- MB length, not thickness, appears to correlate with ischemic burden severity in INOCA.
Abstract:
Exercise stress electrocardiography (ECG) is a commonly used noninvasive test for detecting myocardial ischemia but has limited diagnostic accuracy for obstructive coronary artery disease (CAD). Myocardial bridging (MB), characterized by systolic compression of a coronary artery, has been increasingly recognized as a potential cause of ischemia in patients with nonobstructive coronary arteries (INOCA). This study aimed to investigate the association between MB and positive exercise stress ECG results and to assess the relationship between MB anatomical characteristics and ischemic burden. We retrospectively analysed 197 patients who underwent both exercise stress testing and coronary computed tomography angiography (CTCA) for evaluation of chest pain. MB was identified on CTCA, and its anatomical features, including length and thickness, were measured. Exercise stress ECG results were classified as positive or negative based on standard criteria. MB was present in 32% of the study population. The prevalence of positive exercise stress ECG findings was significantly higher in patients with MB than in those without MB (66% vs. 38%, P < 0.0001). Among patients without obstructive CAD, those with positive ECG findings (INOCA) exhibited the highest prevalence of MB (62%). Additionally, MB length was significantly greater in INOCA patients compared with those with obstructive CAD and positive ECG findings (20.7 ± 6.0 mm vs. 17.1 ± 5.2 mm, P = 0.047), whereas MB thickness did not differ significantly. MB is independently associated with positive exercise stress ECG findings, particularly among patients without obstructive CAD, suggesting a pathophysiological role in exercise-induced ischemia. Furthermore, MB length may contribute to the severity of ischemic burden in INOCA.
More Related Videos


Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:26
Coronary Artery Disease II: Pathophysiology
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and...
 01:30
Acute Coronary Syndrome I: Introduction
 01:21
Myocarditis I: Introduction
 01:30
Coronary Artery Disease III: Clinical Manifestations